Worried adult considering help for cannabis use disorder and weed addiction

Cannabis Use Disorder: Weed Addiction Signs and Criteria

Worried that cannabis use has crossed into weed addiction? Cannabis use disorder is diagnosed when cannabis use causes real distress or impairment and at least two of eleven criteria happen in the same 12 month period. This guide explains the signs in plain language, how severity is judged, and when it makes sense to seek help before things get worse.

Cannabis Use Disorder Criteria in Plain English

Cannabis use disorder, often shortened to CUD, is not based on how often someone uses weed by itself. A person can use cannabis often and not meet criteria. Another person may use less often but still have a serious problem if use is hard to control, keeps causing harm, or starts taking over life.

Under DSM criteria, CUD means a problematic pattern of cannabis use that leads to clinically significant impairment or distress, with at least two criteria in the same 12 month period. Severity is based on how many criteria are present, not on moral judgment or legal status.

This is why the phrase weed addiction can be both useful and incomplete. It may describe how the problem feels, especially when someone cannot cut down, craves cannabis, or keeps using despite consequences. But clinicians look for specific signs, timing, impairment, and distress.

DSM 5 changed the older split between cannabis abuse and cannabis dependence into one disorder with severity levels, and DSM changes also added craving and cannabis withdrawal while removing legal problems as a criterion. That matters because a person does not need an arrest or dramatic life collapse to have a diagnosable disorder.
Infographic of cannabis use disorder criteria and weed addiction warning signs

The Eleven Signs That Matter

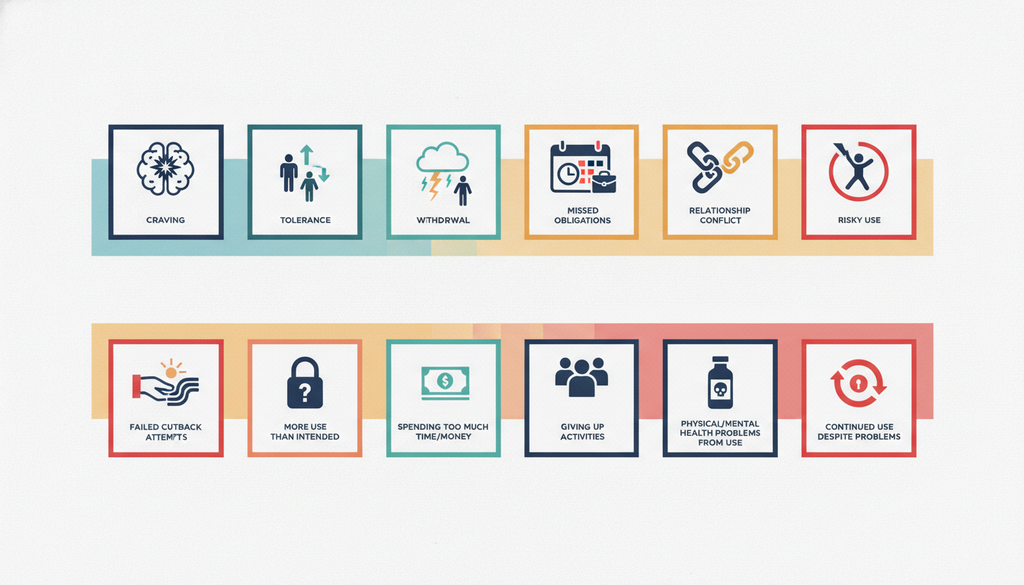
The eleven criteria fall into a few common themes: impaired control, problems at home or work, risky use, continued use despite harm, tolerance, and withdrawal. The table below puts them in everyday language.

SignWhat it can look like
Using more or longer than plannedPlanning to use a little, then staying high for hours or using through the evening
Wanting to cut down but not being able toTrying to quit, take breaks, or set limits, then repeatedly returning to the old pattern
Spending a lot of time on cannabisPlanning around buying, using, being high, or recovering from use
CravingStrong urges to use, especially with stress, boredom, sleep trouble, or reminders
Missing major obligationsMissed work, poor school performance, skipped duties, or unreliable parenting linked to cannabis
Relationship problemsOngoing conflict, secrecy, broken promises, or loss of trust tied to cannabis use
Giving up activitiesLess time for hobbies, friends, exercise, school goals, or family routines because cannabis takes priority
Hazardous useDriving, using machinery, or caring for children while impaired
Continued use despite health or mental health problemsKeeping use going despite panic, paranoia, vomiting, cough, mood problems, or clinician concern
ToleranceNeeding more cannabis, stronger products, or more frequent use to get the same effect
WithdrawalIrritability, anxiety, sleep trouble, low appetite, restlessness, depressed mood, or physical discomfort after stopping or cutting down

A formal diagnosis does not require every sign. Two signs can be enough if they occur in the same 12 month period and the pattern causes meaningful distress or impairment.

That said, one serious sign can still matter. Driving after using, repeated panic after cannabis, unsafe caregiving, or a failed attempt to quit may not prove CUD by itself, but it should raise concern.

Cannabis Use Disorder Severity Levels

Cannabis use disorder is graded by the number of criteria present in the same 12 month period. Two to three criteria is mild. Four to five is moderate. Six or more is severe.

Mild does not mean harmless. It means the person has already crossed the diagnostic line, but the problem may be earlier or less widespread. This can be a good time to act because habits may be easier to change before cannabis causes more damage.

Moderate CUD usually means the pattern has spread across more areas of life. For example, someone might be using more than planned, failing to cut down, craving cannabis, developing tolerance, and having conflict at home.

Severe CUD often includes many domains at once. A person may spend much of the day planning around cannabis, use despite health or mood problems, miss responsibilities, withdraw from activities, and feel unable to stop without withdrawal symptoms.

The point is not to scare you. It is to make the line clearer. If two or more signs are present, the right next step is not shame. It is assessment, support, and a plan.

Tolerance Is a Clue, Not the Whole Answer

Tolerance means needing much more cannabis to get the same effect, or getting much less effect from the same amount. Someone may say, “Flower barely works now,” or “I need concentrates to feel anything.”

Tolerance can be a sign of cannabis use disorder, but it is not the same as addiction by itself. A person needs at least one more criterion and the overall pattern must cause distress or impairment.

This matters for medical cannabis users too. Having a medical reason for cannabis does not rule out CUD. If the person is escalating dose, cannot cut down, keeps using despite harm, or feels unable to function without cannabis, it makes sense to talk with a clinician.

Failed Attempts to Cut Down Are Important

Repeated failed attempts to reduce or stop cannabis are one of the clearest signs that use may no longer be fully voluntary.

This can look like setting rules, then breaking them again and again. “Only on weekends” becomes every night. “No use before dinner” becomes afternoon use. “I am taking a month off” lasts two days.

This is not about weak character. It often means cannabis has become tied to sleep, anxiety, boredom, appetite, social life, pain, or withdrawal relief. If someone has tried to stop and keeps returning to the same pattern, they may need more than willpower.

Lower risk cannabis guidance says people with symptoms of CUD, especially repeated failed efforts to control or reduce use, should seek professional assessment and care through lower risk recommendations.

Time Spent Can Reveal the Real Burden

Some people say, “It only takes a few minutes to smoke,” but the real time cost may be much larger.

Time spent includes getting cannabis, planning when to use, being intoxicated, recovering from use, scrolling menus, arranging delivery, hiding use, or shaping the day around when it is possible to get high. It also includes lost time the next morning when someone feels foggy, tired, anxious, or unable to focus.

This sign matters because cannabis can shrink life quietly. Work may still happen, but hobbies fade. A person may still show up at home, but be less emotionally present. School may continue, but effort drops. The question is not only “How much do you use?” It is also “What has cannabis replaced?”

Role and Relationship Problems Are Red Flags

Cannabis use disorder often shows up first in ordinary life.

At home, that may mean missed chores, unreliable childcare, repeated conflict, money problems, or being emotionally unavailable. At work, it may mean lateness, missed shifts, lower quality work, or using before tasks that need clear thinking. At school, it may mean skipped classes, falling grades, or loss of interest in goals.

Relationship problems count when cannabis causes or worsens the conflict and the person keeps using anyway. Simple disapproval is not enough. A parent or partner may dislike cannabis for personal reasons, but the clinical concern is stronger when there are repeated broken agreements, secrecy, missed duties, or conflict linked to intoxication or recovery.

A useful question is this: “What keeps happening because of cannabis, and does the person keep using despite knowing it is causing problems?”

Withdrawal Can Keep the Cycle Going

Cannabis withdrawal can happen after stopping or sharply reducing heavy, prolonged use. A withdrawal review describes symptoms such as irritability, anxiety, sleep difficulty, appetite change, restlessness, depressed mood, and physical discomfort after reduction or cessation.

Withdrawal is not just being in a bad mood. It can be a reason people return to use even when they want to stop. Someone may restart cannabis because they cannot sleep, feel angry, feel anxious, cannot eat, or feel physically uncomfortable.

Craving and withdrawal can overlap, but they are not the same thing. Craving is the urge to use. Withdrawal is the symptom pattern that can follow stopping or cutting down. Both should be assessed.

If a person uses cannabis mainly to avoid feeling withdrawal, that can count as one of the CUD criteria.

Screening Is Not the Same as Diagnosis

Screening can help, but it is not a final answer.

The CUDIT R is an eight item screening tool that asks about cannabis use and related problems over recent months. A screening study found that lower cutoffs may catch more possible DSM 5 CUD cases than older thresholds in some samples, which is one reason screens should lead to assessment rather than replace it.

SBIRT stands for Screening, Brief Intervention, and Referral to Treatment. SAMHSA describes the SBIRT framework as a way to screen for substance use, assess positive screens more closely, offer brief help, and refer when more care is needed.

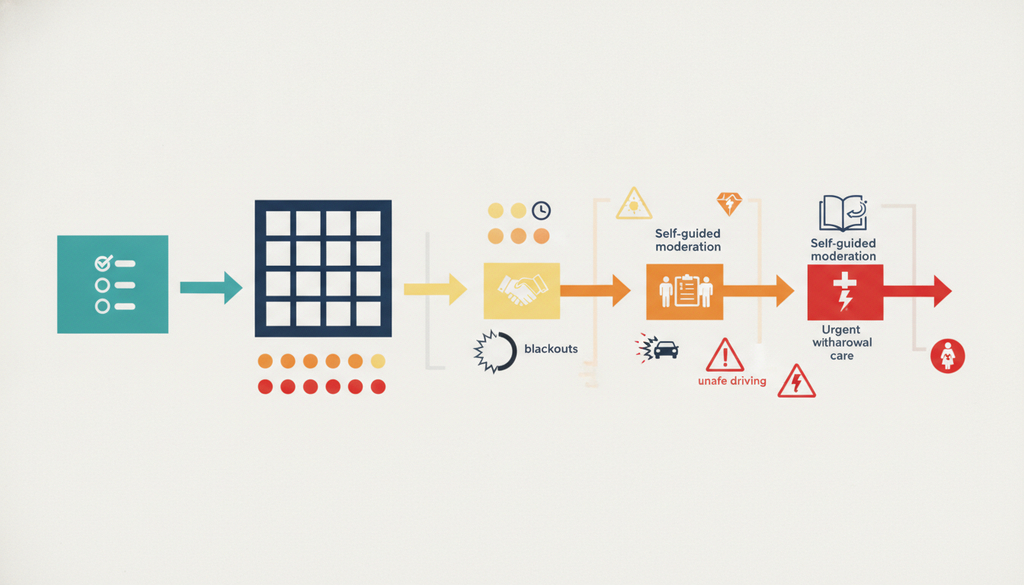
A screen can say, “This deserves a closer look.” A diagnosis needs a clinician to ask about the eleven criteria, the 12 month window, distress, impairment, safety, mental health, medical issues, and other substance use.
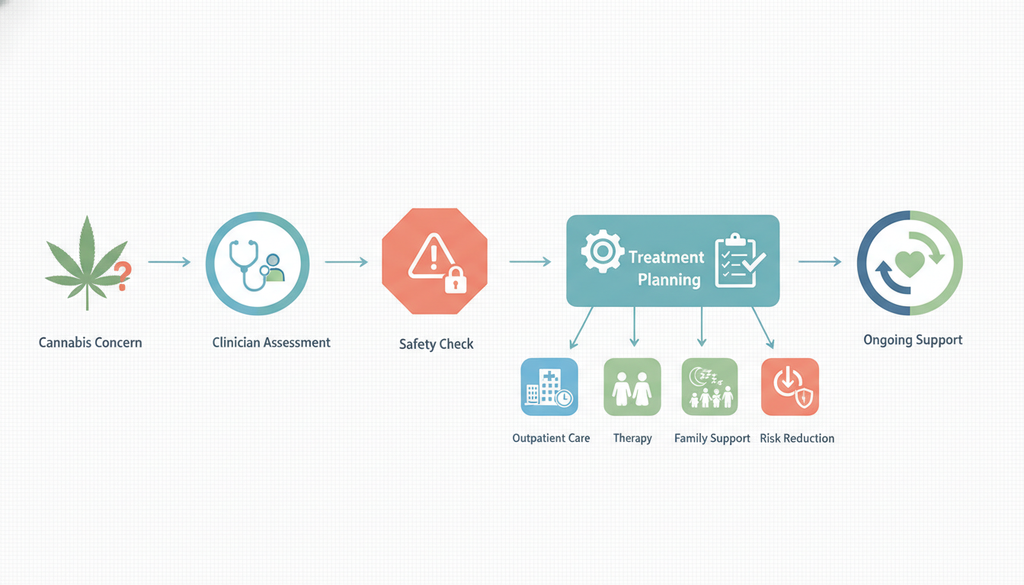
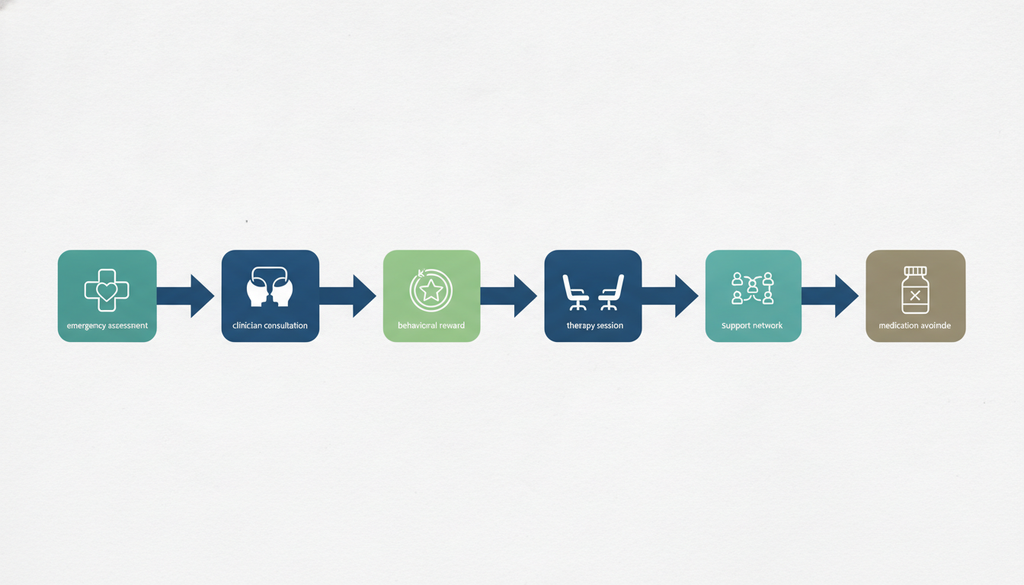
Clinical assessment pathway for cannabis use disorder screening and treatment

When to Seek Help

You do not need to wait for a severe diagnosis to ask for help.

Assessment is wise if cannabis use is hard to control, if there are repeated failed cut down attempts, if there is withdrawal, or if use is affecting work, school, parenting, relationships, driving, mood, sleep, or health.

It is also worth seeking help sooner for adolescents, pregnancy, lactation, psychosis symptoms, severe anxiety, suicidal thoughts, repeated vomiting, or any safety risk. ACOG recommends universal screening for cannabis use during prepregnancy, pregnancy, and postpartum care, and pregnancy guidance advises cessation during pregnancy and lactation with supportive, non punitive care.

If someone is driving after using cannabis, caring for children while impaired, or having paranoia, severe panic, or thoughts of self harm, treat that as a safety issue first. Diagnosis can wait. Safety cannot.

What Treatment Can Look Like

Treatment for weed addiction is not one size fits all. Some people need brief support and monitoring. Others need structured outpatient care, mental health treatment, family support, or more intensive help.

The most common approaches include motivational interviewing, cognitive behavioral therapy, motivational enhancement therapy, contingency management, mindfulness based relapse prevention, and peer support. The Canadian guideline recommends considering several psychosocial approaches for CUD, including CBT, motivational interviewing, motivational enhancement therapy, contingency management, and mindfulness based relapse prevention.

Good care should also ask why cannabis is being used. Is it for sleep, anxiety, trauma symptoms, pain, appetite, boredom, social comfort, or withdrawal relief? Those reasons matter because stopping cannabis without treating the underlying need can make change much harder.

There is no need to start with shame or labels. A practical first step might be a conversation with a clinician, a screening tool, a plan to reduce use safely, or support for sleep and anxiety during a break.

Why This Matters

Cannabis use disorder can be easy to minimize because cannabis is common, legal in many places, and often seen as safer than other substances. But the real question is not whether cannabis is legal or whether other drugs are worse. The question is whether cannabis is still a choice, or whether it has become hard to control and costly to daily life.

If you are asking that question, take it seriously. Look for the pattern. Two or more signs in a year may meet criteria for CUD, but even one serious warning sign can justify support.

You do not have to decide everything today. Start with honesty, safety, and a next step that is realistic.

If cannabis is starting to feel hard to control, reach out for outpatient treatment today at Thoroughbred Wellness and Recovery.

Clinician preparing buprenorphine naloxone sublingual treatment in exam room

Buprenorphine and Naloxone: The Two Medicines in Suboxone

If Suboxone makes you wonder which medicine treats withdrawal and which one prevents misuse, you are asking the right question. Buprenorphine and naloxone work together in Suboxone, but buprenorphine treats opioid withdrawal and cravings, while naloxone mainly discourages injection misuse when the medicine is not taken as directed. This guide explains what each medicine does, why timing matters, and what to ask before starting or changing buprenorphine/naloxone treatment.

Buprenorphine and Naloxone in Suboxone

Suboxone is a combination medicine used to treat opioid use disorder. Its two medicines are buprenorphine and naloxone.

In plain terms, buprenorphine is the treatment medicine in Suboxone, and naloxone is the safety feature added to reduce misuse.

That answer surprises many people. Naloxone is well known because it is used to reverse opioid overdose, so people often assume it is the part that causes withdrawal in Suboxone. When Suboxone is taken correctly under the tongue or in the cheek, that is usually not what happens.

The key point is this: buprenorphine can cause precipitated withdrawal if it is started too soon after fentanyl, heroin, methadone, oxycodone, or another full opioid. Naloxone usually has little effect when Suboxone is used sublingually, because product information says sublingual naloxone has poor bioavailability at the doses used in the combination product.

That does not mean naloxone does nothing. If buprenorphine / naloxone is injected, naloxone can become active in the body and may help trigger withdrawal in a person who is physically dependent on opioids. That is part of why it is included in the product.

How Buprenorphine and Naloxone Work

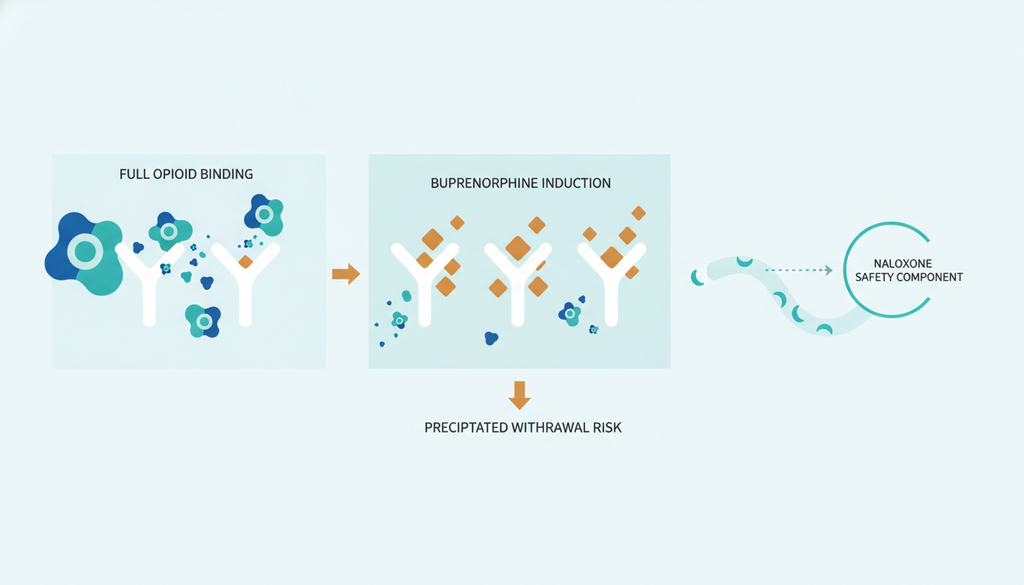
Buprenorphine is a partial opioid agonist. It attaches tightly to mu opioid receptors, the same receptor system affected by many opioids. It can reduce withdrawal, ease cravings, and help protect against overdose risk.

The word partial matters. Full opioid agonists can produce high levels of receptor activation. Buprenorphine activates the receptor less strongly, but it binds with very high affinity. That means it can push other opioids off the receptor.

This is useful after the body is ready for buprenorphine. It is risky if a person still has enough fentanyl, heroin, methadone, or another full opioid active at the receptor. The Cleveland Clinic Journal of Medicine describes this risk as tied to buprenorphine’s high receptor affinity, which can quickly change opioid signaling.

Naloxone works differently. It is an opioid antagonist. In Suboxone, its main role is not to treat cravings. It is there to make injection misuse less appealing, because naloxone can block opioid effects and trigger withdrawal when it reaches the bloodstream in a person who is opioid dependent.

So the two medicines have different jobs. Buprenorphine provides the main treatment effect. Naloxone adds a misuse deterrent when the product is not used as prescribed.

Why buprenorphine can trigger withdrawal

Precipitated withdrawal is different from regular withdrawal.

Regular withdrawal starts as opioid levels fall over time. Precipitated withdrawal can come on fast after a medicine changes receptor activity suddenly. With Suboxone, this can happen if buprenorphine replaces a full opioid but gives less receptor activation than the opioid it displaced.

A person may feel sudden worsening of symptoms such as sweating, chills, stomach cramps, diarrhea, vomiting, anxiety, body aches, restlessness, or intense discomfort. It can be frightening. It can also make someone afraid to try treatment again.

That is why starting buprenorphine naloxone at the right time matters so much.

Diagram of buprenorphine naloxone receptor effects and precipitated withdrawal risk

Why Timing Matters So Much

Older teaching often used time since last opioid use as a rough guide. For heroin or other short acting opioids, many protocols used about 12 to 24 hours of abstinence before starting standard buprenorphine. For methadone and other long acting opioids, the wait could be much longer.

Fentanyl changed this.

Fentanyl is highly lipophilic, meaning it can move into fat and muscle tissue. With frequent exposure, it may leave the body in a slower and less predictable way. A person may wait a long time and still not be ready for a standard dose of buprenorphine/naloxone.

That is why a clock alone is not enough. Guidance from New York State emphasizes treatment decisions based on opioid withdrawal signs and clinical assessment, not only hours since last use.

A study of people with opioid use disorder found that taking buprenorphine within 24 hours of fentanyl use was linked with higher odds of severe withdrawal, and the risk was also higher during the 24 to 48 hour window. The same study reported severe withdrawal in 22.19 percent of people who took buprenorphine less than 24 hours after fentanyl use, compared with 11.56 percent of people who took methadone in that same time frame, according to the fentanyl study findings.

That does not mean everyone must wait the same number of hours. It means recent fentanyl use is a real risk marker. Some people may be ready sooner if they are in clear withdrawal. Others may need more time or a different start method.

Signs clinicians look for

Before a standard start, clinicians often use the Clinical Opiate Withdrawal Scale, or COWS, plus direct observation. The goal is not to make someone suffer. The goal is to avoid starting too soon.

Objective signs matter because anxiety, pain, nausea, and fear can overlap with opioid withdrawal. Common physical signs include:

  • Dilated pupils
  • Sweating or gooseflesh
  • Yawning, runny nose, or tearing
  • Vomiting or diarrhea
  • Tremor or visible restlessness
  • Chills, body aches, or clear physical discomfort

Many standard protocols use moderate withdrawal before the first dose. Some guidance uses a COWS score above 12. Some emergency or monitored protocols use a lower threshold, such as 8 or higher, when staff can reassess the person closely.

The exact number should not be treated like a magic switch. A COWS score is useful, but the whole picture matters.

Standard Starts and Low Dose Starts

There are two broad ways to start buprenorphine/naloxone: a standard start and a low dose start.

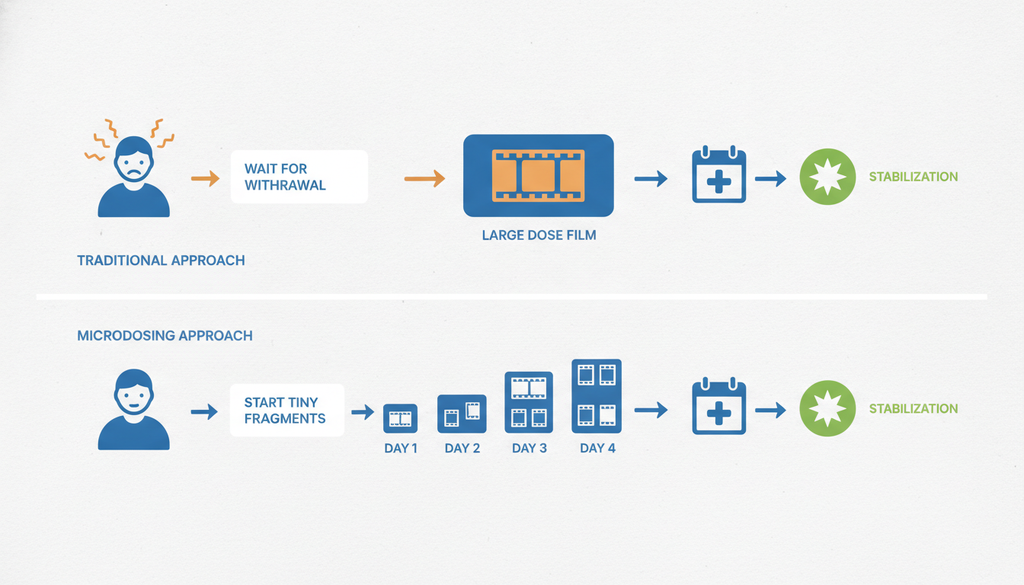
In a standard start, the person stops the full opioid and waits until withdrawal is clearly present. Then buprenorphine is started, often with a small first dose such as 2 to 4 mg. The person is reassessed, and more medicine may be given if withdrawal continues.

This can work well. It is also faster and simpler than a low dose start when the person is truly ready.

The problem is that many people using fentanyl cannot predict when that moment will come. Some have tried to wait, became very sick, took Suboxone, and felt worse. Others cannot safely tolerate a long period without opioids because of work, housing, pain, caregiving, or fear of severe withdrawal.

Low dose initiation, sometimes called microdosing or the Bernese method, takes a different path. It starts with very small doses of buprenorphine while the person continues a full opioid for a short period. The dose rises over several days until the person reaches a treatment dose and stops or tapers the full opioid.

The goal is gradual replacement at the receptor instead of a sudden shift. A recent outpatient study of low dose initiation in people using fentanyl found that completion was difficult in real life, with 34 percent of attempts completed and 22 percent retained on buprenorphine at 28 days.

That matters. Low dose initiation is a helpful option, but it is not a guarantee. It can be harder to follow because dosing is more complex. People may need to split films or tablets, take doses at set times, and stay in contact with the care team. Continued fentanyl use during the overlap period also carries overdose risk.

The best choice depends on the person, the opioid involved, withdrawal signs, prior experience, and the care setting.

Visual comparison of standard and low dose buprenorphine naloxone initiation

What Fentanyl Changed

Fentanyl did not make buprenorphine stop working. It made starts more unpredictable.

Some people using fentanyl can still start Suboxone with a standard method once they have clear withdrawal. Others may be at higher risk for precipitated withdrawal even after waiting longer than expected. Reports in the research include cases after 72 to 80 hours since last stated fentanyl use, which shows why no fixed waiting period can promise safety.

At the same time, fear can become its own barrier. If people are told to wait too long without help, they may return to fentanyl use before they ever start treatment. If they start too soon, they may get precipitated withdrawal and lose trust in treatment.

This is where good clinical care makes a difference. The plan should fit the person in front of the clinician, not a rigid rule.

Emergency settings may use other pathways. High dose starts, sometimes called macro starts, can give larger total doses in a monitored setting once withdrawal is present. A large emergency department case series reported precipitated withdrawal in 0.8 percent of encounters and no documented respiratory depression or excess sedation in that setting, according to the high dose study.

That does not mean high dose starts are right for every outpatient setting. Monitoring, staff experience, and follow up matter.

Suboxone, Generics, and Product Changes

Suboxone is a brand name, but many people receive generic buprenorphine/naloxone. Some receive films. Some receive tablets. Some receive products with different bioavailability, such as Zubsolv.

These details are not just packaging. Product labels warn that switching between tablets and films, or between different film strength combinations, may change drug exposure. FDA labeling notes that people should be monitored when changing sublingual film products because dose changes may be needed.

That is important if your pharmacy changes your product, your insurance plan stops covering a brand, or your prescriber switches you from a film to a tablet. Same active ingredients does not always mean the experience will feel identical.

A case report described one patient who had been stable on brand Suboxone film and then reported withdrawal and cravings after insurer required switches to generic films. The report does not prove generics are worse for everyone. It does show that some stable patients may need reassessment, dose adjustment, or a return to the product that worked for them after a forced switch.

If your medicine changes and you feel worse, do not assume you failed treatment. Ask what changed. The product, dose, manufacturer, route, timing, and how the film or tablet dissolves can all matter.

Questions to Ask Before Starting or Switching

You deserve clear instructions, especially if fentanyl is part of your recent opioid use or if you have had precipitated withdrawal before.

Ask your prescriber which start method they recommend and why. Ask what withdrawal signs you should wait for before a standard start. Ask what to do if you feel worse after the first dose. If a low dose start is recommended, ask for written instructions and a backup plan if you miss a dose or cannot follow the schedule.

If your pharmacy or insurance changes your medication, ask whether the new product is a film, tablet, brand, generic, or different manufacturer. Ask whether the dose is meant to be the same or converted. Ask when someone will check in with you after the switch.

If you are pregnant, breastfeeding, have liver disease, or take sedating medicines such as alcohol or benzodiazepines, tell the prescriber before starting. Those details can affect product choice, dose planning, and monitoring.

Most of all, be honest about recent fentanyl, methadone, heroin, oxycodone, or other opioid use. This is not about getting in trouble. It is about choosing the safest way to start.

Why This Matters for Recovery

Buprenorphine and naloxone can be confusing because both are opioid related medicines, but they do different jobs in Suboxone. Buprenorphine is the main medicine that treats opioid withdrawal and cravings. Naloxone is mainly there to discourage injection misuse and usually has little effect when taken under the tongue as directed.

The hard part is timing. Starting too soon can cause precipitated withdrawal. Waiting too long without support can make treatment harder to begin. Fentanyl makes this balance more complicated because withdrawal can be delayed or unpredictable.

A good plan does not rely only on a clock. It looks at your withdrawal signs, your opioid history, your past starts, your setting, and your ability to follow the instructions. Standard starts can work well when you are clearly in withdrawal. Low dose starts can help when waiting is not realistic. Monitored settings may use other pathways.

If you are ready to talk through options for opioid treatment, withdrawal support, or the next safe step, reach out for detox treatment support at Thoroughbred Wellness and Recovery.
Family member finds unknown crack cocaine lookalike and pipe at home

Crack Cocaine: What It Is, What It Looks Like, and Its Risks

Crack cocaine is a smokeable form of cocaine that can look like small, irregular rocks, but you cannot identify it safely by sight. Crack cocaine is cocaine base in solid form, and the DEA says this route can take effect in about 7 to 10 seconds after vapor is breathed in. This guide explains what it is, what it may look like, how it differs from powder cocaine, and what risks to take seriously.

Crack Cocaine Basics

If your main question is what is crack cocaine, the plain answer is this: it is a solid, smokeable form of cocaine. Cocaine itself is a stimulant. Crack and powder cocaine are related forms of the same drug, but they are often used in different ways.

The Congressional Research Service describes crack as a solid form that is generally smoked, while powder cocaine is generally snorted or dissolved and injected. That difference in route matters because smoking can produce a very fast effect.

Crack is not a different drug family from cocaine. It is cocaine in a form that can be smoked. That is why the question is crack cocaine often leads to a simple answer: yes, it is cocaine, but it is not the same product form as the white powder many people picture.

The fast onset can make use feel intense and brief. Some people may smoke again soon after the effect fades. That pattern can raise the risk of compulsive use, repeated exposure, and medical emergencies.

What Does Crack Cocaine Look Like?

People often ask what does crack cocaine look like because they found a small rock, a crumbly chunk, or residue near a pipe. Crack is commonly described as irregular white or off white rocks or chunks. The National Drug Intelligence Center describes crack as being sold in rock form after cocaine is processed into a solid.

Still, sight alone is a poor way to identify it. A pale rock or powder can be many things. It might be cocaine base, powder cocaine, methamphetamine, crushed medication, sodium bicarbonate, an adulterant, or a non drug household material.

Visual comparison of crack cocaine, powder cocaine, methamphetamine and lookalikes

Color does not solve the problem. Shape does not solve it either. A substance that “looks like crack” may not be crack, and a substance that does not look unusual may still be dangerous.

Smell, taste, burning, or home testing are not safe ways to find out. Do not put an unknown substance near your mouth or nose. Do not heat it. Do not crush it to inspect it. If children, pets, or anyone in the home might have access, the safer move is to treat it as unknown and potentially hazardous.

Is Cocaine Crack?

Is cocaine crack? Not always. Crack is cocaine, but not all cocaine is crack.

Powder cocaine is usually cocaine hydrochloride. Crack is cocaine base in a solid form that is commonly smoked. That means the difference is not just appearance. It also involves chemical form and route of use.

This is why the question is cocaine crack needs a careful answer. If someone says “cocaine,” they may mean powder cocaine. If someone says “crack,” they usually mean a smokeable rock or chunk form. Both expose the body to cocaine, and both can be addictive.

Powder cocaine can also be dangerous. It can be snorted, dissolved, or injected. It can contribute to heart problems, anxiety, paranoia, seizures, and substance use disorder. A slower route does not make it safe.

Smoking crack can carry extra risk because the effect arrives so quickly. The person may feel a rush, then a quick drop, then a strong urge to use again. That cycle can make it hard to stop once a session starts.

Why Sight Is Not Enough

A visual guess cannot tell you what is in a substance. It cannot tell you dose, purity, potency, or whether fentanyl or another contaminant is present.

Forensic systems use chemical testing for a reason. The DEA describes NFLIS as a system based on chemical identification from drug exhibits submitted to participating forensic laboratories. In 2025, NFLIS reported 666,357 cases and 1,126,178 substance identification reports, with fentanyl making up 11.74 percent of reports.

Those numbers do not mean every suspected crack sample contains fentanyl. They do show why confidence based on sight is risky. The drug supply changes, and a name given on the street does not prove what a substance contains.

Recent surveillance also found cocaine and methamphetamine samples cut with fentanyl, xylazine, and medetomidine in some places. The NDEWS report described regional samples that included cocaine alone in some cases and cocaine with active adulterants in others. That mix is the point: some samples contain what people expect, and some do not.

Paraphernalia can offer context, but it cannot prove the drug. A small pipe may suggest smoking. A straw or card may suggest powder use. Foil, lighters, small bags, and scales may raise concern. But none of these items can tell you the exact substance, who used it, how much was used, or whether the material contains fentanyl.

Crack Cocaine Risks and Overdose Signs

Crack cocaine is a stimulant, so many people expect fast speech, high energy, restlessness, anxiety, sweating, or agitation. Cocaine can also affect the heart and brain. Severe reactions can include chest pain, confusion, seizures, fainting, and dangerous changes in behavior.

The added danger today is that a suspected stimulant may not be only a stimulant. Cocaine and methamphetamine can be contaminated with opioids such as fentanyl. If that happens, the person may show opioid overdose signs rather than only stimulant signs.

Watch for slow or absent breathing, blue or gray lips, choking or gurgling sounds, limp body, pinpoint pupils, or inability to wake up. These are emergency signs. Do not wait to see whether the substance was crack, powder cocaine, fentanyl, or something else.

The CDC says naloxone can help reverse opioid overdose and will not harm someone who has not taken opioids. Its naloxone guidance says to call 911, give naloxone if available, keep the person breathing, place them on their side if appropriate, and stay until help arrives.

If someone is awake but very agitated, paranoid, having chest pain, or acting in a way that could hurt them or others, that can also be an emergency. Cocaine related medical crises are not limited to overdose with slowed breathing.

Who Invented Crack Cocaine?

If you are asking who invented crack cocaine, the evidence used for this article does not name one single inventor. The safer answer is that crack developed as a processed form of cocaine base, not as a product that can be credited to one clearly identified person in these sources.

It is worth being cautious here. Many online claims about who invented crack cocaine are political, racialized, or poorly sourced. If a source does not provide solid evidence, it is better not to repeat the claim.

What matters for health and safety is clearer. Crack is a smokeable cocaine product. It can cause rapid effects. It can support repeated use. It can be mixed with or contaminated by other substances. If an unknown rock or residue is found, the right response is safety first, not certainty by sight.

What To Do If You Find It

Finding a small rock, powder, baggie, pipe, or residue can make you want answers right away. That reaction is normal. But the first goal is not to prove what it is. The first goal is to keep people safe.

NIOSH advises treating unknown powders as potentially hazardous and warns that field testing can increase exposure risk if powder is disturbed. That is especially relevant if fentanyl or related substances are possible.

Use this simple response plan:

  • If anyone is unconscious, hard to wake, having seizures, having chest pain, or not breathing normally, call 911 now.
  • Give naloxone if opioid overdose is possible and naloxone is available.
  • Keep children, pets, and uninvolved adults away from the area.
  • Do not taste, smell closely, crush, burn, sweep, vacuum, or move the substance around.
  • Take factual notes if you can do so safely, such as location, time, visible items, symptoms, and what was said.
  • For possible exposure without life threatening symptoms, contact Poison Control or a medical professional for guidance.

Try to use neutral language. Instead of saying, “This is definitely crack,” say, “I found an unknown off white rock like substance near a pipe.” That keeps the focus on facts and safety.

If the person is a loved one, avoid a confrontation while they are intoxicated, frightened, paranoid, or withdrawing. You can set firm safety boundaries without shaming them. For example, you can say that substances cannot be used in the home, that you will call 911 if breathing changes, and that you want them to get a clinical assessment.

Family safety steps after finding suspected crack cocaine or unknown drugs

Getting Help Without Shame

Crack cocaine use can become serious quickly, but people do recover. Help is not only for daily use or for the most severe cases. It is also appropriate when someone is using more than planned, cannot stop once they start, has intense cravings, keeps using despite panic or chest pain, or keeps returning to use after promising not to.

A professional assessment can look at the full pattern: route of use, frequency, cravings, mental health symptoms, medical risk, overdose history, other substances, and safety at home. That matters because the item found in a room is only one piece of the story.

Families often want certainty, but certainty may not be possible without lab testing and a clinical evaluation. What you can do is act on risk. Treat unknown substances as unknown. Respond fast to overdose signs. Keep children safe. Speak in facts. Encourage care.

If crack cocaine or another substance is affecting your life or someone you love, you do not have to handle it alone. Reach out for drug addiction treatment at Thoroughbred Wellness and Recovery when you are ready.

Clinician discussing cocaine high duration and health risks with patient

How Long Does a Cocaine High Last? Timeline and Effects

If you are wondering how long does a cocaine high last, the answer depends mostly on how cocaine is used. Smoked cocaine often feels intense for about 5 to 10 minutes, injected cocaine for about 10 to 20 minutes, and intranasal effects can last about 60 to 90 minutes. This guide explains the timeline, why redosing happens, and when symptoms call for medical or clinical support.

How Long Does a Cocaine High Last by Route?

The direct answer is that a cocaine high can last from a few minutes to more than an hour, depending on the route, dose, purity, tolerance, and whether more is used during the same session.

Route matters because it changes how fast cocaine reaches the bloodstream and brain. Smoking and injection create a much faster rush than snorting. Snorting usually comes on more slowly, but the felt effects may last longer.

A plain way to think about it is this:

  • Snorting cocaine often starts after several minutes and may last about 60 to 90 minutes, smoking can start within seconds and may feel intense for about 5 to 10 minutes, and injection can create a rush within about 30 to 45 seconds that often lasts about 10 to 20 minutes.

These ranges are not safety rules. They are broad patterns. A person may feel the euphoria fade while cocaine is still affecting the heart, brain, mood, sleep, and judgment.

How long does cocaine high last by route comparison graphic

What Changes the Timeline?

Cocaine does not have one simple timeline. The same person may have a different experience on different days. Dose, purity, sleep, hydration, tolerance, physical health, alcohol use, opioid use, and recent abstinence can all change the way the high feels.

Controlled research comparing routes found that smoked cocaine produced stronger ratings of good effects and liking than intravenous cocaine, even when some body responses were similar at comparable blood levels. That finding from a route comparison study helps explain why the felt reward can differ from what blood concentration alone would predict.

This matters because people often judge risk by how they feel. If the high is gone, they may assume the drug is gone too. That is not a safe assumption.

Snorting Cocaine

Intranasal cocaine, often called snorting, has a slower onset because it must pass through the nasal tissue. The desired effects may begin after several minutes and can last much longer than smoked or injected cocaine.

The Centre for Addiction and Mental Health describes intranasal effects as slower and longer lasting, with a snorted high that may last about 60 to 90 minutes. That longer window can make snorting seem less risky, but it can still strain the heart, raise blood pressure, affect judgment, and lead to repeated use.

Snorting can also harm the nose and sinuses over time. Cocaine narrows blood vessels, including in nasal tissue. With repeated use, this can lead to irritation, bleeding, infection, reduced smell, and more serious tissue damage.

Smoking Cocaine

Smoked cocaine has a very fast onset. The high can begin within seconds, peak quickly, and fade fast. Many people describe this as a sharp rush followed by a strong urge to repeat the dose.

In a controlled study of smoked cocaine, peak blood levels occurred within minutes, and several subjective effects were highest right after use. The study on smoked cocaine also showed that felt effects do not always move in step with cocaine levels in the body.

That mismatch is a key point. A person may feel like the high has ended, yet the body may still be under stress. If they smoke more to bring back the rush, each dose can add to a nervous system and cardiovascular system that have not fully settled.

Injecting Cocaine

Injected cocaine reaches the bloodstream directly. The rush can happen very quickly, often within less than a minute. It is also short lived, which can lead to repeated dosing in a short window.

Injection brings more risks beyond cocaine itself. These include infection, vein injury, and transmission of HIV or hepatitis if equipment is shared. It also carries high acute risk because the dose enters the body so quickly.

Even when the rush fades, heart rate, blood pressure, agitation, anxiety, and other effects may continue. That is why the end of the rush should never be used as proof that it is safe to use more.

Why the High Fades Before the Risk Does

Cocaine’s rewarding effects can fade faster than its strain on the body. That gap is one reason cocaine use can become dangerous quickly.

Smoked and injected cocaine can create a cycle of rush, fade, craving, and redosing. The person may not be chasing a long high. They may be trying to bring back a feeling that disappeared within minutes.

Brain imaging research found that smoked cocaine had an absorption half time of about 1.1 minutes, while intranasal cocaine had an absorption half time of about 11.7 minutes. Those absorption times show why smoking can feel so abrupt compared with snorting.

The crash can also begin soon after the high fades. That crash may include fatigue, low mood, irritability, anxiety, hunger, sleepiness, and strong craving. UF Health describes cocaine withdrawal as including strong craving, fatigue, depressed mood, sleep change, and irritability.

This is where confusion can happen. The person may think, “I just need a little more to feel normal.” But redosing can raise risk, especially if the body is already stressed.

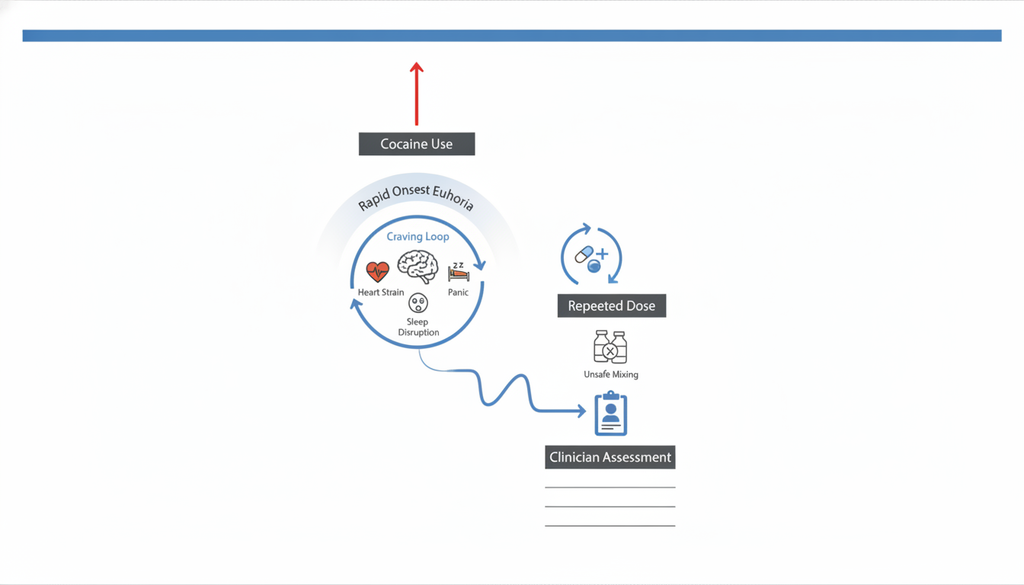
Redosing Is a Risk Signal

Redosing means using more during the same session. It is common with short acting routes, especially smoking and injection. It is also one of the clearest signs that the situation needs attention.

Redosing does not automatically mean someone has cocaine use disorder. It does mean the person may be in a higher risk pattern.

The main danger is cumulative exposure. Each dose may feel like a separate event, but the body does not reset after every hit, line, or injection. Cocaine can keep raising strain on the heart and brain while judgment gets worse.

Risk rises further when cocaine is mixed with alcohol, opioids, sedatives, or other stimulants. It also rises after a period of abstinence because tolerance may be lower than the person expects.

If someone keeps using after chest pain, panic, severe paranoia, breathing trouble, or a frightening physical reaction, that is more concerning than duration alone. The timeline matters, but the pattern matters more.

When Redosing Points to a Disorder

Cocaine use disorder is not diagnosed by the number of doses in one night. It is diagnosed by a pattern over time.

DSM 5 TR aligned guidance says stimulant use disorder requires at least two criteria within the same 12 month period, along with clinically significant distress or problems in life. Cocaine is included under stimulant use disorder.

One key criterion is using more or for longer than intended. That means redosing may matter if someone planned to use once but kept going for hours, planned to spend a small amount but spent far more, or repeatedly promised themselves they would stop and could not.

Redosing may also connect to craving, failed efforts to cut down, hazardous use, tolerance, withdrawal, or continued use despite harm. But each point needs to be assessed. A single night of repeated use is not enough by itself to make a diagnosis.

This distinction matters because shame can stop people from getting help. You do not need to label yourself to take the pattern seriously. If cocaine use is becoming harder to control, support can start before a diagnosis is certain.

Cocaine redosing warning signs and clinical assessment infographic

How Long Does a Cocaine High Last Compared With a Crash?

The high is usually much shorter than the crash. A smoked high may last minutes, but the comedown can last many hours. After a binge, low mood, fatigue, sleep changes, irritability, and cravings can continue into the next day or longer.

This is one reason the question “how long does cocaine high last” can be misleading. The euphoria may be brief, but the fallout may last much longer.

A crash may feel like depression, anxiety, or deep exhaustion. Some people sleep for long periods. Others cannot sleep at all, even when they feel drained. Some feel numb or hopeless. Others feel agitated and restless.

A crash is not always an emergency, but it deserves respect. Suicidal thoughts, severe paranoia, hallucinations, dangerous agitation, or inability to stay safe should lead to same day help or emergency care.

The end of the high is not the end of the risk.

When to Get Medical Help Now

Cocaine can cause serious problems quickly. The most urgent signs include chest pain, irregular heartbeat, fainting, severe shortness of breath, seizure, severe headache, weakness on one side, confusion, overheating, collapse, or loss of consciousness.

The CDC says suspected stimulant overdose can become a medical emergency and calls for emergency care rather than waiting for symptoms to pass.

Call emergency services if any of those symptoms appear after cocaine use. Do not wait to see whether the high wears off. Heart attack, stroke, seizure, dangerous overheating, and severe agitation can happen with cocaine.

There is another risk too. Cocaine may be mixed with opioids such as fentanyl, even when the person did not intend to take an opioid. Naloxone reverses opioid overdose, not cocaine toxicity, but SAMHSA notes that naloxone reverses opioid overdose and should be used when opioid exposure is possible.

Possible opioid overdose signs include unresponsiveness, slow or stopped breathing, blue or gray lips, and pinpoint pupils. If these happen, call emergency services, give naloxone if available, and stay with the person.

Screening Can Help Before Things Get Worse

You do not have to wait for a crisis to ask for help. If cocaine use is becoming more frequent, harder to stop, or tied to anxiety, depression, money problems, work problems, relationship strain, or health scares, screening is a reasonable next step.

The World Health Organization developed the ASSIST to identify substance related health risk and guide brief intervention or referral. The WHO ASSIST is a screening tool, not a diagnosis, but it can help sort low, moderate, and high risk use.

A good assessment should look at route of use, frequency, redosing, cravings, crash symptoms, other substances, medical history, mental health, and safety. It should also ask what the person wants. Some people want to stop. Some want to reduce harm first. Some are not sure yet.

That uncertainty is normal. A respectful clinician can meet the person where they are while still being honest about risk.

Treatment and Support

Stimulant use disorder can be treated. The right level of care depends on safety, medical risk, mental health needs, and how much support the person has at home.

The ASAM and AAAP guideline identifies contingency management as the current standard of care for stimulant use disorder. The stimulant guideline also stresses assessment for medical and psychiatric concerns, including agitation, psychosis, suicidality, and cardiovascular symptoms.

Treatment may include individual counseling, group therapy, family support, relapse prevention planning, mental health care, and help with sleep, mood, anxiety, trauma, or other co occurring concerns. If someone is using cocaine with alcohol, opioids, benzodiazepines, or other drugs, care should account for those risks too.

There is no single path that fits everyone. The best plan is practical, honest, and safe. It should reduce immediate risk while helping the person build enough support to change the pattern.

Why This Matters

A cocaine high may be brief, especially when smoked or injected. That short duration can make redosing feel urgent. But the body may still be under strain after the euphoria fades, and the crash can bring intense craving, low mood, and poor judgment.

So the better question is not only “how long does a cocaine high last?” It is also, “What happens after it fades, and is the pattern getting harder to control?”

If use is rare, the answer may be education, safer choices, and support. If use keeps going longer than planned, leads to redosing, causes health scares, or brings a painful crash, it is time to take it seriously.

You do not need to hit a dramatic bottom to deserve help. Cocaine related risk often shows up first as small warning signs: using more than intended, hiding use, feeling scared by symptoms, or promising to stop and then going back.

If cocaine use feels hard to stop, compassionate detox support at Thoroughbred Wellness and Recovery can help you take the next safe step.

Clinician comparing crack vs cocaine forms during addiction assessment

Crack vs. Cocaine: How They Differ and Why It Matters

If you are asking about crack vs cocaine, you are probably trying to understand whether one is more dangerous or more addictive. Both deliver cocaine, but smoking crack usually acts within seconds and fades faster, while snorted powder cocaine usually starts over minutes and lasts longer. This guide explains the real difference, why it changes risk, and what treatment should focus on.

Crack vs Cocaine: The Plain Answer

Crack and cocaine are not totally separate drugs; crack is a smokable form of cocaine, and the main clinical difference is how fast and intensely it reaches the brain.

That answer can feel surprising because people often talk about cocaine vs crack as if they are two different substances. In plain terms, powder cocaine and crack cocaine both involve the same active stimulant. A U.S. Sentencing Commission review describes both forms as delivering the same active drug, but the common route of use changes the experience.

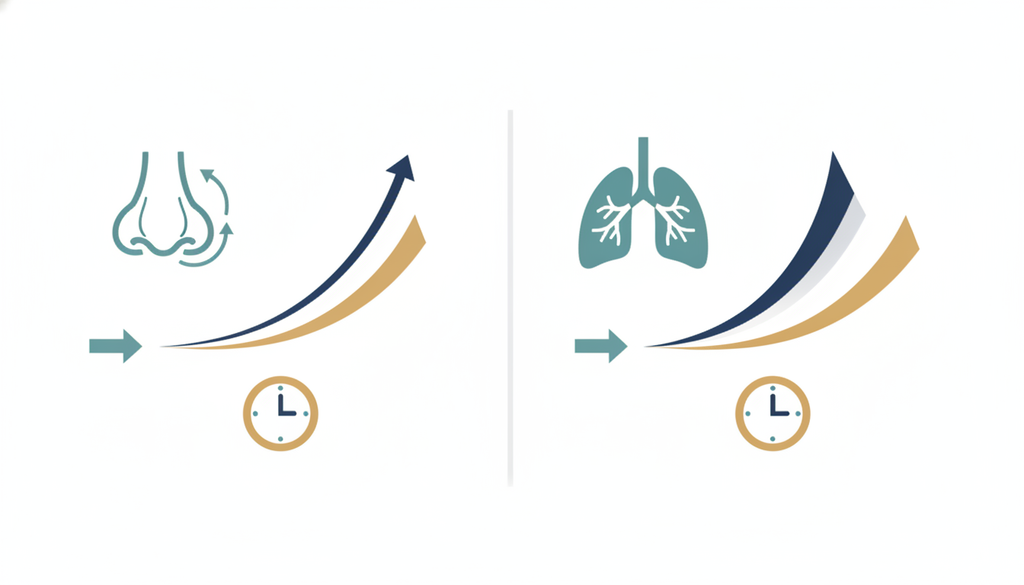
Powder cocaine is often snorted. Crack cocaine is often smoked. Smoking sends cocaine through the lungs and into the bloodstream very quickly. Snorting sends cocaine through the nasal tissue first, so the rise is slower.

That speed matters. A fast rise can create a stronger rush. A shorter high can also push someone to use again sooner. So, when someone asks, “is crack and cocaine the same thing,” the honest answer is yes and no. The active stimulant is the same, but the route and pattern of use can make the risk feel very different.

The Difference Between Crack and Cocaine

The biggest difference between crack and cocaine is not the name. It is the delivery.

In a controlled human study, researchers compared intravenous, intranasal, and smoked cocaine in experienced cocaine users. Intranasal use produced slower onset and weaker effects than smoked cocaine, while smoked cocaine produced high ratings of drug liking in the study.

That does not mean every person who smokes crack has a more severe addiction than every person who snorts cocaine. It means smoking can create a more intense and compressed reward cycle. Use, feel the effect, feel it fade, use again. That loop can happen quickly.

Here is a simple way to compare crack cocaine vs cocaine in the forms people usually mean:

QuestionPowder cocaine, often snortedCrack cocaine, often smoked
Is the active stimulant cocaineYesYes
How fast does it usually actOver minutesWithin seconds
How long does the high often feelLonger than smoked useShorter and sharper
What pattern can it encourageRepeated use over a sessionRapid redosing in a shorter window
What body area may be harmed by the routeNose and sinusesLungs and airways
Does it have separate DSM 5 TR criteriaNoNo
Can it cause cocaine use disorderYesYes

The table gives the broad pattern, not a promise about every person. Dose, purity, other substances, sleep, health, mental state, and frequency all change risk.

Infographic showing cocaine vs crack onset and duration by route

Why Smoking Can Feel More Compulsive

Cocaine affects reward and alertness systems in the brain. The faster the effect arrives after use, the stronger the brain may link the act of using with the reward.

That is one reason smoked crack can feel especially hard to interrupt. The effect can arrive within seconds. Then it can fade quickly. A person may feel driven to repeat the dose, sometimes trying to get back to the first rush.

Research on smoked cocaine also shows why this can become frustrating and risky. In a human binge study, participants could self administer repeated smoked cocaine doses. The first one or two doses produced stronger effects, while later doses did not create the same increase, suggesting acute tolerance during the session.

That pattern helps explain the phrase “chasing the high.” A person may keep using because the desired effect is fading, but each later dose may give less of what they are seeking. The body still carries the stress. The heart, blood pressure, sleep, mood, and judgment can still be affected.

This is where crack vs cocaine gets misunderstood. Crack is not a magic category of addiction. It is cocaine used in a way that often produces faster reinforcement. Powder cocaine is not safe just because the onset is slower. A person can snort cocaine often, use large amounts, mix it with alcohol, miss work, damage relationships, and develop severe cocaine use disorder.

Is Crack the Same as Cocaine Clinically

If the question is “is crack the same as cocaine,” the clinical answer is that crack is a form of cocaine, not a separate diagnosis.

DSM 5 TR stimulant use disorder is based on behavior and harm. It looks at a pattern of stimulant use that causes impairment or distress across a 12 month period. Severity depends on the number of criteria met, with mild, moderate, and severe levels based on criterion count, not whether the person smoked or snorted.

That matters because route can bias how people judge someone. Crack has long carried more stigma than powder cocaine. But a fair clinical assessment asks better questions.

Is the person using more than planned? Have they tried to stop and been unable to? Do they crave cocaine? Are they missing duties at home, work, or school? Are they using in dangerous situations? Are they continuing despite panic, paranoia, chest pain, depression, relationship conflict, or money problems?

Those questions apply to both forms.

A person who smokes crack once a month may face serious acute risks during use, yet may not meet criteria for stimulant use disorder. Another person who snorts powder cocaine several days a week may meet many criteria and need a higher level of care. The route helps shape the risk picture. It should not replace the assessment.

What Cocaine Can Do to the Body

Both crack and powder cocaine can raise heart strain and mental health risk. The research material notes shared risks such as fast heart rate, high blood pressure, irregular heartbeat, heart attack, stroke, seizures, agitation, panic, paranoia, and stimulant related psychosis.

Route adds its own problems. Snorting can irritate and damage the nose and sinuses. Long term intranasal use can be linked with nosebleeds, smell changes, and damage to the nasal septum. Smoking can irritate the airways and lungs. It can also lead to cough, burns, and breathing problems.

None of this means every person will have the same symptoms. Cocaine risk changes with dose, frequency, health history, sleep loss, heat, stress, and other substances. Alcohol can worsen risk. Opioids, sedatives, and fentanyl exposure can change an already risky situation into a medical emergency.

The Fentanyl Era Changed the Risk

The old question, “what is the difference between crack and cocaine,” is still useful. But it is not enough in today’s drug supply.

Cocaine related emergencies may involve more than cocaine. CDC materials warn that people who use stimulants may be unknowingly exposed to opioids, and that fatal overdoses involving both opioids and stimulants have grown. CDC reported that in 2017, nearly three fourths of cocaine involved fatal overdoses involved at least one opioid, according to its stimulant guide.

That statistic does not prove that every cocaine product contains fentanyl. It does mean a person cannot judge safety by sight, route, price, or the label someone gives the drug.

More recent surveillance also shows meaningful overlap. In SUDORS data from 31 states and the District of Columbia, cocaine was co involved in 30.9 percent of illicitly manufactured fentanyl involved overdose deaths from January 2021 through June 2022, based on CDC findings with coroner or medical examiner data.

So, powder cocaine is not a guarantee of safety. Crack is not the only concern. Any illicit stimulant can carry unexpected risk, especially when the person is using alone or mixing substances.

If someone is hard to wake, breathing slowly, breathing irregularly, turning blue or gray, or making gurgling sounds, treat it as a possible opioid overdose. Call emergency help and give naloxone if available. If the person has chest pain, severe agitation, overheating, seizure, severe headache, confusion, or psychosis, that is also an emergency, even if they are awake.

Why Treatment Is the Same Pathway

The treatment pathway for cocaine use disorder does not split into one system for crack and another for powder cocaine. Good care starts with safety, then a full assessment of use, health, mental health, and social needs.

The ASAM and AAAP guideline says the first priority is identifying urgent medical or psychiatric symptoms in stimulant use disorder, including intoxication or overdose, and getting the right level of care. The same guideline identifies contingency management as the current standard of care for stimulant use disorders.

Stimulant use disorder treatment pathway for crack and cocaine use

Contingency management uses clear, immediate rewards for recovery behaviors, such as attending care or having stimulant negative tests. That may sound simple, but it fits stimulant use well. Cocaine gives fast reinforcement. Treatment can help by making recovery behaviors more immediate, concrete, and supported.

Other therapies can also help. Cognitive behavioral therapy can help someone understand triggers, cravings, thoughts, and relapse patterns. Community support, recovery planning, family work, housing support, and care for trauma or mood symptoms can all matter. Many people need treatment for anxiety, depression, PTSD, bipolar symptoms, sleep problems, or other substance use at the same time.

There is no FDA approved medication specifically for cocaine use disorder. The ASAM and AAAP guideline allows selected off label medication options in some cases, but those decisions need careful medical judgment. Medication should not be described as a cure for cocaine addiction.

What Assessment Should Ask

A strong assessment should not stop at “crack or powder.” It should ask about form, route, frequency, amount, binge pattern, last use, cravings, attempts to stop, medical symptoms, mental health symptoms, and other substances.

For crack, it helps to ask how quickly the person uses again after a dose, whether they have cough or chest symptoms, and whether the crash leads to more use. For powder cocaine, it helps to ask about nose symptoms, alcohol mixing, long sessions, and whether use has grown over time.

The clinician should also ask about fentanyl exposure, opioid use, naloxone access, alcohol, benzodiazepines, other stimulants, housing, safety, trauma, legal stress, work, family, and support. These details matter because cocaine use disorder is not only about the drug. It is also about the life around the drug.

A person who uses both crack and powder may have extra risk. Research among people with HIV found daily cocaine use was reported by 6 percent of powder only users, 12.1 percent of crack only users, and 20 percent of people using both forms, with dual users also showing more polysubstance use in that study. That kind of finding supports asking about both forms instead of forcing someone into one label.

Why Labels Can Get in the Way

Words like “crack addict” or “cokehead” do not help anyone get better. They make it harder to speak honestly. They also hide the actual clinical questions.

The better question is not, “which form did you use?” It is, “what is happening to your health, choices, safety, and life?”

Cocaine can become a problem through a fast, intense smoked pattern. It can also become a problem through frequent snorted use that slowly takes over work, sleep, money, and relationships. Both deserve care without shame.

Stigma can also make families underestimate risk. Someone may think, “at least it is powder,” and miss warning signs. Or they may think crack use means recovery is hopeless. Neither belief is true. The route matters, but people are more than a route.

Why Crack vs Cocaine Matters in Treatment

Crack vs cocaine matters because route can change onset, intensity, redosing, and physical harms. It does not matter because it creates two separate kinds of people.

In treatment planning, smoked crack may point to rapid redosing, intense cues, short cycles of craving, and airway concerns. Snorted powder may point to longer sessions, nasal injury, alcohol mixing, and social use patterns. Both can involve craving, withdrawal symptoms, depression, anxiety, paranoia, chest pain, overdose risk, and relapse.

The best care is route informed and person centered. It asks what the drug is doing in the person’s life, what risks are present today, what support is missing, and what kind of plan the person can actually use.

If cocaine use feels hard to control, or you are worried about someone you love, compassionate drug addiction treatment can help you take the next step at Thoroughbred Wellness and Recovery.

ENT exam for cocaine nose septum and sinus damage

Cocaine Nose: How Snorting Damages the Septum and Sinuses

Snorting cocaine can damage the nasal septum and sinuses by cutting off blood flow to tissue that needs oxygen to stay alive. Stopping cocaine can let inflamed nasal lining improve over weeks to months, but a septal hole, collapsed bridge, or palate defect usually needs a device or surgical repair rather than waiting. This guide explains what cocaine nose means, which symptoms are warning signs, what may heal, and when to seek medical or recovery support.

Cocaine Nose Starts With Blood Flow Loss

Cocaine nose is a plain phrase for nasal and sinus damage linked to snorting cocaine. It can mean mild irritation, crusting, nosebleeds, a septal perforation, sinus disease, a collapsed bridge, or wider tissue loss in the midface.

The core problem is blood flow. Cocaine strongly narrows blood vessels in the nose. When this happens again and again, the nasal lining, septal cartilage, bone, and nearby sinus structures may not get enough oxygen.

Peer reviewed CIMDL literature describes this process as a mix of ischemia, inflammation, infection, immune effects, and repeated injury from snorting. Ischemia means poor blood supply. When tissue is starved of blood long enough, it can ulcerate, die, and break down.

The septum is especially vulnerable. The septum is the wall between your nostrils. Its cartilage depends on the thin lining around it for nutrition. If that lining is repeatedly damaged, the cartilage can weaken or die. That is how a small raw area can become a hole through the septum.

This is why switching nostrils or using a different straw does not make snorting safe. Less scraping does not remove the blood flow problem.

Why Snorting Cocaine Damages the Septum

A healthy nose warms, filters, and moistens air. The lining has tiny moving hairs and mucus that help clear dust, germs, and irritants. Snorting cocaine disrupts that system in several ways.

First, cocaine dries and irritates the lining. Dry tissue cracks more easily. Cracks lead to crusting and bleeding. Crusts can feel blocked, so people may pick or blow harder, which causes more trauma.

Second, cocaine narrows blood vessels. The same effect that numbs tissue can also starve it. Over time, repeated blood flow loss can move from surface irritation to deeper damage.

Third, infection can set in. Crusted, ulcerated, poorly perfused tissue does not defend itself well. Infection can add swelling, foul discharge, pain, and more tissue injury.

Fourth, destructive disease can extend beyond the septum. Severe cocaine related injury can involve the turbinates, nasal floor, sinuses, hard palate, orbit, and, rarely, the skull base. A systematic review found 99.2 percent of reported cocaine induced midline destructive lesion cases had septal perforation, which shows how central the septum is in severe disease.

That figure does not mean nearly everyone who uses cocaine gets a perforation. It describes people already identified with severe destructive lesions. Still, it shows why a hole in the septum is one of the classic findings in advanced cocaine nose.

Symptoms You Might Notice

Early symptoms can look like ordinary rhinitis or sinus trouble. That makes this hard. Congestion, sniffing, throat clearing, mild nosebleeds, and a runny nose can come from allergies, dry air, viral illness, sinus inflammation, medication effects, or nasal picking.

Cocaine injury becomes more concerning when symptoms are persistent, progressive, bloody, crusted, foul smelling, painful, or linked with changes in airflow or shape.

A small septal hole may cause a whistle when you breathe in. Larger holes may cause less whistling but more dryness, crusting, bleeding, and a blocked feeling. ISSUP explains that septal perforation can cause whistling, crusting, bleeding, and nasal obstruction even when the outside of the nose still looks normal.

People sometimes search for a cocaine nose sample because they want to compare photos. Be careful with that. A cocaine nose sample or photo can show what damage may look like, but it cannot diagnose your nose. Different causes can look alike, including autoimmune disease, infection, prior surgery, trauma, tumors, and overuse of some nasal sprays.

Seek medical care soon if you notice any of these warning signs:

  • A new whistle when breathing through the nose
  • Repeated nosebleeds with heavy crusting
  • Foul, bloody, or thick discharge
  • A visible hole, raw area, or black tissue inside the nose
  • New flattening or collapse of the nasal bridge
  • Loss of smell with worsening congestion or crusting
  • Food or liquid coming through the nose while eating or drinking
  • Eye pain, swelling, double vision, vision change, severe facial pain, fever, or confusion

Those last eye, fever, confusion, or severe pain symptoms can be urgent. They may point to infection or spread beyond the nose.

What Can Heal and What Usually Cannot

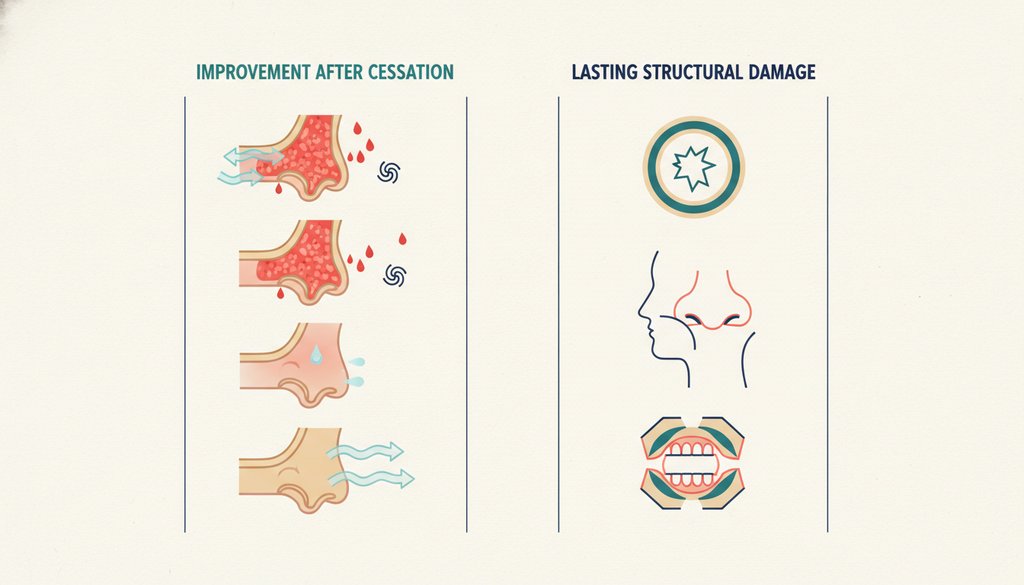
The short answer is simple: inflamed lining may improve, but missing structure usually does not grow back.

If cocaine use stops completely and enough living tissue remains, dryness, congestion, crusting, superficial ulcers, minor bleeding, runny nose, and some smell problems may improve. This often takes weeks to months, and care from an ear, nose, and throat clinician can help.

The 2025 Young IfOS consensus on cocaine induced midline destructive lesions stresses that time since last use is not enough on its own. Doctors also look at whether the lining is still inflamed, crusted, infected, necrotic, or getting worse.

That matters because symptoms and anatomy are not the same thing. A person can feel better but still have a permanent septal hole. Another person can stop cocaine but keep having crusting because airflow through the hole dries the edges.

Cartilage and bone are different from irritated lining. Once septal cartilage is destroyed, it is not expected to rebuild itself. An established septal perforation rarely closes by itself. A saddle nose deformity, where the bridge collapses because support is lost, usually does not reverse without reconstruction. A palate hole generally needs a prosthetic device or surgery.

Recoverable cocaine nose symptoms versus permanent septal damage

Smell is unpredictable. If smell is reduced because swelling, mucus, or crusting blocks airflow, it may improve. If smell loss comes from deeper injury, scarring, long lasting sinus disease, or severe tissue loss, it may persist.

Cocaine Nose Is Not Always Easy to Diagnose

A cocaine history helps guide care, but clinicians still need to rule out other causes. Cocaine related midline destructive disease can resemble granulomatosis with polyangiitis, other autoimmune conditions, fungal infection, bacterial infection, syphilis, tuberculosis, malignancy, trauma, and postsurgical problems.

This is why a careful exam matters. An ear, nose, and throat clinician may use anterior rhinoscopy, nasal endoscopy, imaging, cultures, blood tests, or biopsy depending on what they see.

Blood tests can be tricky. Some cocaine related or adulterant related disease can cause immune markers that look like autoimmune vasculitis. So a positive test does not always give a clean answer. Doctors have to combine the history, exam, imaging, labs, and tissue findings.

There is another reason to be honest with clinicians. If cocaine use is hidden, a person may be treated for the wrong illness. If cocaine use is assumed without checking, another serious disease may be missed. A respectful medical conversation protects you either way.

Treatment, Septal Buttons, and Surgery

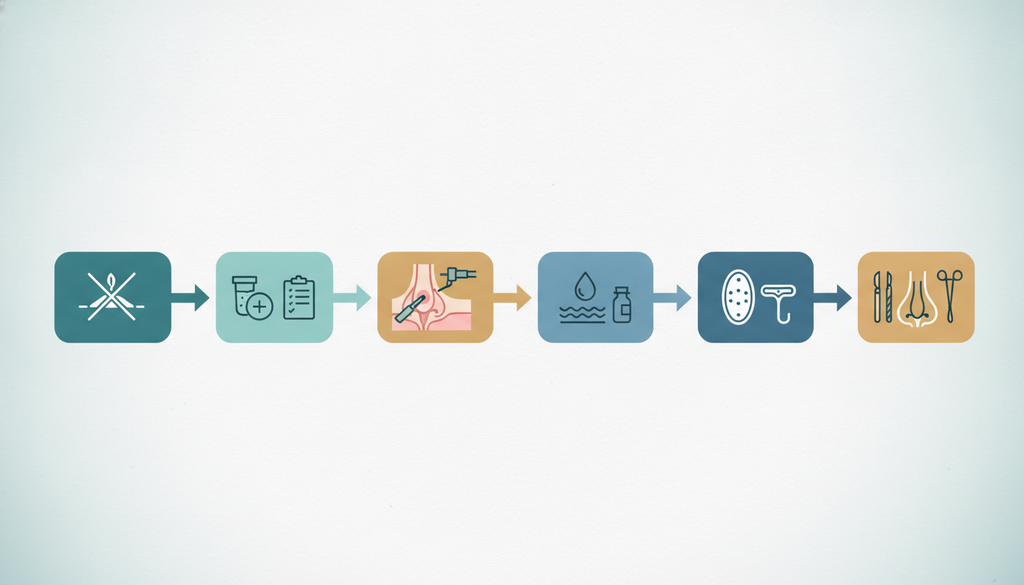
The first treatment is complete cocaine cessation. No rinse, ointment, antibiotic, septal button, or operation can overcome repeated cocaine induced blood flow loss. If use continues, ulcers may not heal, holes can enlarge, and future repair can fail.

Conservative nasal care may include saline irrigation, humidification, careful removal of crusts by a clinician, treatment of infection when present, and avoiding nose picking or forceful blowing. These steps do not rebuild cartilage, but they can reduce bleeding, crusting, odor, and blockage.

A septal button is a prosthetic device placed through a septal perforation. It can reduce whistling, turbulence, dryness, bleeding, and crusting for some people. It does not restore tissue. Some people do not tolerate it because of discomfort, crusting, odor, infection, or irritation.

A palate hole is different. It can cause liquids or food to pass into the nose, nasal speech, and swallowing problems. The palatal repair literature describes an obturator for palatal perforation as a common bridge or longer term option while abstinence and defect stability are established.

Surgery can help selected people, but timing is strict for a reason. Repair needs healthy, moist, well vascularized lining. Cocaine damaged tissue may be scarred, thin, infected, inflamed, or short on usable lining. Active cocaine use is a major reason to delay elective repair.

Some published palatal reconstruction practice describes 6 to 12 months cocaine free before repair. Some nasal reconstructive surgeons require at least 12 months and prefer longer. The safest standard is not the calendar alone. The defect should be stable, the lining should look healed, infection should be treated, and abstinence should be documented.

Cocaine nose surgery pathway with abstinence verification and septal button care

Nicotine matters too. Smoking and vaping can reduce healing reserve. In septoplasty research, worse septal healing in smokers supports the concern that nicotine exposure can add risk when septal tissue is already vulnerable.

When Sinuses and Palate Are Involved

Sinus involvement can bring facial pressure, foul drainage, blocked airflow, reduced smell, and recurrent infections. But sinus symptoms alone do not prove cocaine injury. Chronic rhinosinusitis, allergies, polyps, dental problems, migraine, and ordinary infections can overlap.

What raises concern is the pattern. Severe crusting, foul odor, bloody discharge, exposed tissue, repeated bleeding, worsening facial pain, loss of smell, or a whistling septum deserves prompt care.

Palate symptoms are more specific for a structural problem. If liquids enter the nose when drinking, if speech suddenly sounds very nasal, or if there is a visible hole in the roof of the mouth, that is not ordinary congestion. It can happen when destructive disease creates a passage between the mouth and nose.

Eye symptoms are even more urgent. Eye swelling, pain with eye movement, double vision, reduced vision, fever, or severe headache can mean infection or destructive disease has reached areas where delay can threaten sight or safety.

Why Stopping Cocaine Changes the Outcome

Stopping cocaine is not a guarantee that everything returns to normal. It is still the step that gives the nose the best chance to stabilize.

If injury is early, the lining may calm down. Crusting may lessen. Bleeding may slow. Congestion may improve. Superficial ulcers may heal. Smell may return if blockage and inflammation were the main causes.

If injury is structural, stopping still matters. It can help keep a small hole from becoming a large one. It can reduce infection risk. It can make a septal button easier to tolerate. It can create the conditions needed before a surgeon will even consider repair.

The hardest truth is that waiting can change the options. Early irritation is often treated with cessation and supportive care. A septal perforation may need a button or complex closure. A collapsed bridge may need reconstruction. A palate hole may need an obturator or surgery. Severe midface destruction may need more than one specialist and more than one stage of care.

If you are worried about your nose, try not to let shame decide the timeline. An ENT exam can show whether the lining is inflamed, whether the septum is intact, whether sinuses are involved, and whether the defect is stable. Addiction care can help make stopping possible before more tissue is lost.

If stopping cocaine feels hard, our team at Thoroughbred Wellness and Recovery can help you make a confidential detox program today.

Doctor discussing naltrexone for alcohol use disorder with patient

Naltrexone for Alcohol Use Disorder: How Treatment Works

If you are wondering whether medication can help you drink less, naltrexone for alcohol use disorder is one of the best studied options. Naltrexone 50 mg daily has been linked with fewer returns to heavy drinking, with one 2023 review estimating benefit for about 1 in 11 people treated. This article explains what it does, what it cannot do, and when to talk with a prescriber.

Naltrexone for Alcohol Use Disorder Basics

Naltrexone is a medication used to treat alcohol use disorder, often called AUD. It does not make you sick if you drink. It also does not sedate you, detox you, or remove all cravings.

In plain terms, naltrexone for alcohol helps lower the reward some people feel from alcohol, which can make it easier to stop after one drink, avoid binge drinking, or return to a goal after a slip.

The usual oral dose studied for AUD is 50 mg once daily. That daily 50 mg plan is the standard oral approach and is the best supported schedule in the research provided. A large JAMA review found that oral naltrexone reduced return to heavy drinking more clearly than it reduced any drinking at all.

That last point matters. Naltrexone alcohol treatment is often about lowering risk, not flipping a switch from heavy drinking to instant abstinence. Some people use it while working toward no alcohol. Others use it to reduce heavy drinking days, cut the number of drinks per drinking day, or stop a lapse from turning into a long binge.

How Naltrexone Changes Drinking Patterns

Naltrexone blocks opioid receptors involved in alcohol reward. Alcohol can trigger the brain’s own opioid system, which is one reason drinking may feel reinforcing. By blocking that pathway, naltrexone can make alcohol feel less rewarding for some people.

That does not mean every drink will feel like water. It also does not mean the medication removes habit, stress, trauma cues, social pressure, or withdrawal risk. Alcohol use disorder is not only about reward. Still, lowering reward can give you more room to pause and choose.

Research suggests the clearest benefit is fewer heavy drinking episodes. In the 2023 review, oral naltrexone had a stronger effect on return to heavy drinking than on return to any drinking. A Boston University summary of the same evidence reported a number needed to treat of about 11 to prevent one return to heavy drinking, compared with about 18 to prevent one return to any drinking through oral naltrexone treatment.

So if you start naltrexone and still drink, that alone does not prove it failed. A better question is whether your drinking is less intense, less frequent, or less likely to become heavy.

A meaningful response might look like going from several heavy drinking days each week to one. It might mean drinking four drinks instead of eight on a drinking day. It might mean cravings feel less urgent, even if they are still present.

Daily Dosing Versus Targeted Dosing

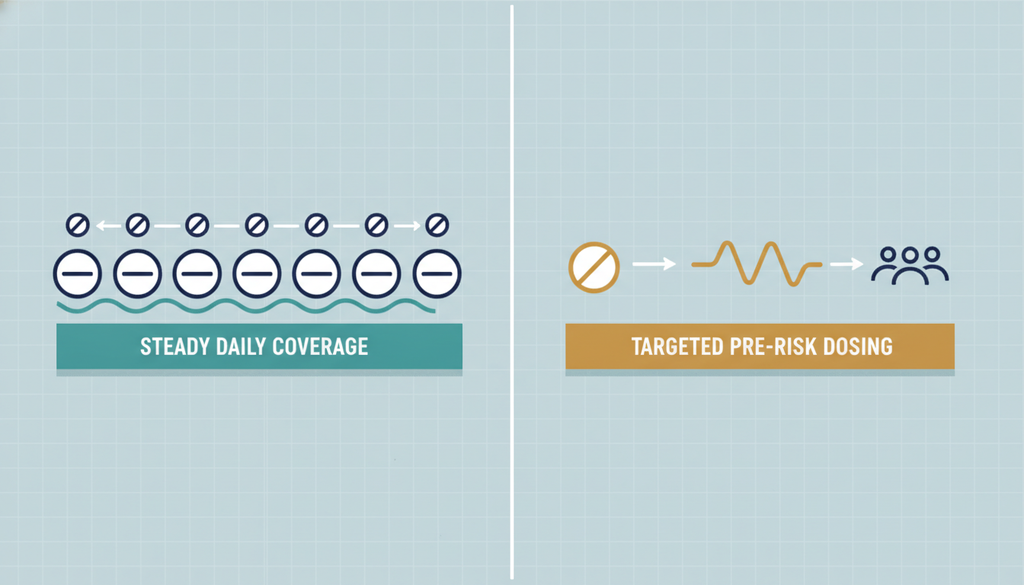
Most people hear about daily naltrexone first. Daily dosing means taking 50 mg every day, whether or not you expect to drink. This can make sense when cravings are frequent, drinking is not predictable, or heavy drinking happens after stress, poor sleep, conflict, loneliness, or impulse.

Targeted dosing means taking 50 mg before a likely drinking event or when craving starts. You may also hear it called as needed dosing or pre drinking dosing. This approach has some controlled trial support, but the evidence base is narrower than the evidence for daily use.

Daily versus targeted naltrexone alcohol dosing concept infographic

In one modern randomized trial, 120 sexual and gender minority men with binge drinking and mild to moderate AUD took targeted naltrexone or placebo. At 12 weeks, targeted naltrexone reduced binge drinking days by 26 percent, weeks with any binge drinking by 17 percent, and drinks per month by 31 percent versus placebo in the targeted trial population.

That is encouraging. But the same study did not compare targeted dosing with daily dosing. So it does not prove targeted use works as well as daily use for most adults with AUD.

The practical difference is coverage. Daily naltrexone gives steady coverage. Targeted naltrexone depends on noticing risk before drinking starts, having the tablet available, and taking it in time. If your drinking is planned and limited to predictable events, targeted dosing may be worth discussing. If your drinking tends to start suddenly, daily treatment is often the more realistic plan.

What Progress Should Look Like

Naltrexone works best when progress is measured, not guessed. Many people judge themselves only by whether they drank at all. That can miss real gains.

Track heavy drinking days, drinking days, drinks per drinking day, total drinks, cravings, and missed doses. If you use targeted dosing, also track whether you took it before the risk moment or after drinking had already started.

Here is a simple way to think about follow up:

Time PointWhat To Look ForWhat To Discuss
Week 4Early movement, such as fewer heavy drinking days, fewer drinks per drinking day, or lower cravingDo not call it failure too soon. Review side effects, missed doses, and whether the plan fits your drinking pattern
Week 8A clearer pattern, such as about 30 percent fewer heavy drinking days or a steady drop in drinking intensityIf progress is small, talk about daily dosing, targeted dosing, adherence support, or another care plan
Week 12A full trial review, with focus on heavy drinking, craving, safety, and whether you value the changeIf there is partial benefit, consider improving the plan before stopping medication

These are practical check points, not strict rules from a trial. The research provided does not give a validated switch point at week 4, 8, or 12.

Still, the timing is useful. Many studies used about 12 weeks of active treatment, and by then you and your prescriber should have enough information to decide whether the current plan is helping.

When Drinking Continues During Treatment

Continued drinking can feel discouraging. But naltrexone is not meant to punish lapses or prove willpower. It is meant to reduce the chance that drinking becomes heavy or keeps escalating.

Guidance from the New York State Department of Health says active alcohol use is not a contraindication to starting or continuing naltrexone, and it recommends continuing treatment when drinking continues or resumes while revisiting goals through NYSDOH guidance for AUD care.

That means a slip does not automatically mean you should stop. It means you should look at what happened.

Did you miss doses before the drinking episode? Did you drink in a setting you did not plan for? Was the craving stronger than usual? Did side effects make you avoid the medication? Did stress, grief, anxiety, or trauma symptoms drive the drinking?

If naltrexone reduces heavy drinking but does not stop all drinking, that may still be a real benefit. If it lowers craving but you keep drinking in the same environment, you may need more behavioral support, a safer plan for high risk settings, or a different level of care.

If there is no change at all after a well followed trial, the conclusion is not that you failed. It may mean that this dose, schedule, or medication is not the right fit.

Naltrexone for Alcohol Use Disorder Safety

Naltrexone is not right for everyone. A prescriber needs to check opioid use, liver concerns, withdrawal risk, current medications, and treatment goals.

The opioid issue is especially important. Naltrexone blocks opioid receptors. If a person is physically dependent on opioids, naltrexone can trigger sudden opioid withdrawal. It is not used with opioid pain medication, methadone, buprenorphine, current opioid dependence, or acute opioid withdrawal. Prescribing information describes the need for an opioid free interval, often at least 7 to 10 days after short acting opioids, through naltrexone labeling on safety and dosing.

Liver safety also matters. Naltrexone should be used with care when liver tests are abnormal, and it is not used in acute hepatitis or liver failure. That does not mean every mild liver enzyme change rules it out. Alcohol itself can harm the liver, and reducing heavy drinking can be part of the solution. The key is medical review and follow up.

Alcohol withdrawal is a separate safety issue. Naltrexone does not treat withdrawal. It does not prevent withdrawal seizures or delirium tremens. If you drink heavily every day, have morning shakes, have needed alcohol to feel normal, or have had withdrawal seizures or delirium in the past, you need a withdrawal risk assessment before cutting down quickly.

The ASAM alcohol withdrawal guideline separates risk prediction from current symptom scoring and notes that tools such as PAWSS and CIWA Ar answer different questions in withdrawal management care.

Seek urgent in person help if you have a seizure, confusion, hallucinations, severe shaking, fever, chest pain, severe vomiting, dehydration, severe agitation, or a very fast heart rate after reducing alcohol. Naltrexone may become useful later, but withdrawal safety comes first.

Oral Tablets And Monthly Injections

Naltrexone comes as oral tablets and as an extended release monthly injection. Oral tablets are often started first because they are easy to stop if side effects happen. They also help show whether you tolerate the medication.

Monthly extended release naltrexone may help when taking a pill every day is the problem. If you do better when you take the tablet but keep missing doses, an injection may create steadier coverage.

The New York guideline recommends extended release naltrexone when oral adherence is a concern and suggests a short oral trial first to establish tolerability through AUD treatment guidance.

Naltrexone AUD follow-up timeline for drinking and craving changes

Research comparing oral and injectable forms does not mean injections are always better. A later trial summary in hospitalized adults found large reductions in heavy drinking days in both groups, without a statistically clear difference between oral and injectable treatment. The practical choice often comes down to access, cost, preference, adherence, side effects, and medical fit.

Side Effects And Dose Questions

Common side effects can include nausea, headache, dizziness, fatigue, and reduced appetite. Some people do better when starting at a lower dose and then increasing, but that is a prescriber decision.

The standard oral AUD dose is 50 mg daily. Some clinicians may consider 100 mg in select cases, usually when 50 mg helps somewhat, is well tolerated, and safety checks look acceptable. But this should not be treated as automatic. The strongest evidence is for 50 mg daily, and labeling warns that single doses above 50 mg may raise liver injury risk.

It is also worth saying this plainly: do not change your dose on your own. More medication is not always better, and missed doses are often a bigger issue than dose strength.

If side effects make you skip pills, tell your prescriber. If cravings remain high but drinking is down, that may still support continuing. If drinking is unchanged and adherence is strong, it may be time to rethink the plan.

Who May Benefit Most

Naltrexone may be a good fit if your main problem is heavy drinking, binge drinking, drinking more than planned, or craving that leads to escalation. It may also help if your goal is harm reduction rather than immediate abstinence.

Daily dosing may fit better when drinking is frequent or unpredictable. Targeted dosing may fit better when drinking happens in clear, planned situations and you can take the medication before the risk starts.

Medication works best when paired with support. That may include counseling, group treatment, family support, skills for cravings, sleep care, trauma treatment, or a higher level of care if drinking is medically risky.

AUD often overlaps with anxiety, depression, trauma, sleep problems, and stress. Naltrexone can help with alcohol reward, but it does not solve every driver of drinking. A good treatment plan looks at the whole pattern.

Why This Matters For Real Recovery

The most useful way to think about naltrexone is as a tool, not a cure and not a test of character. It can lower the pull of alcohol enough for other parts of recovery to start working.

For some people, that means fewer binges. For others, it means less shame after a lapse because the lapse does not take over the week. For others, it creates enough stability to engage in therapy, repair sleep, rebuild trust, or step into a more structured program.

Naltrexone for alcohol use disorder is best judged by real outcomes: fewer heavy drinking days, fewer drinks per drinking day, lower craving, better safety, and a plan you can actually follow.

If alcohol use feels hard to control or you are worried about withdrawal, get support before trying to handle it alone. To talk through medication, detox safety, and treatment options, reach out to Thoroughbred Wellness and Recovery for detox and outpatient care.

Binge drinking definition shown through drinks and stopwatch at bar

What Is Binge Drinking? The Definition and the Risks

Binge drinking means drinking enough alcohol in one sitting to raise short term harm, usually four drinks for women or five for men within about two hours. The practical binge drinking definition is this: that amount often brings blood alcohol concentration near 0.08 percent. This article explains what counts, what does not, and when a drinking pattern may call for real support.

Binge Drinking Definition: What Counts?

If you are asking what is binge drinking, the simplest answer is that it is a pattern of drinking, not a diagnosis.

The National Institute on Alcohol Abuse and Alcoholism describes binge drinking as drinking that brings blood alcohol concentration to about 0.08 percent. For many adults, that means four or more standard drinks for women or five or more standard drinks for men in about two hours.

A standard drink in the United States contains about 14 grams of pure alcohol. That can look like 12 ounces of regular beer, 5 ounces of wine, or 1.5 ounces of distilled spirits, according to the same drinking patterns guidance from NIAAA.

That last part matters. Many real drinks are larger than one standard drink. A tall craft beer, a mixed drink with more than one shot, or a heavy wine pour may count as more than one drink, even if you only call it “one.”

So, what is considered binge drinking in real life? It depends on the amount of alcohol, how fast you drink it, and the size of each pour. A person may reach the binge drinking threshold sooner than they think.

Binge Drinking Meaning Versus Alcohol Use Disorder

The binge drinking meaning is often confused with alcohol use disorder, but they are not the same thing.

Binge drinking is about exposure. It describes a high risk drinking episode. Alcohol use disorder is about symptoms, loss of control, and harm over time. A person can binge drink once and not have alcohol use disorder. A person can also have alcohol use disorder without drinking in the classic binge pattern every time.

DSM 5 alcohol use disorder is based on at least two symptoms in a 12 month period. Those symptoms can include drinking more than intended, craving, trouble cutting down, role problems, hazardous use, tolerance, or withdrawal. In one study, rising binge frequency was tied to higher odds of mild, moderate, and severe alcohol use disorder, but quantity alone still did not equal diagnosis through AUD severity findings.

This distinction can reduce shame and improve decisions. The question is not “Am I a bad person because I binge drank?” The better question is “Is this happening often, getting more intense, or causing harm?”

What Counts as One Drink?

Here is a simple way to estimate standard drinks. It is not perfect, but it can help you see why drink size can be misleading.

Drink type Usual standard drink amount Why it can be confusing
Regular beer 12 ounces Strong beer or large cans may count as more
Wine 5 ounces Home pours are often larger
Distilled spirits 1.5 ounces Cocktails may contain more than one shot

A key point is that the body responds to alcohol content, not the glass, can, or cup. If a cocktail has two shots, it is closer to two standard drinks. If a beer has a high alcohol level, one can may be more than one standard drink.

This is why someone may say, “I only had three drinks,” while their body processed far more alcohol than they realized.

Visual guide to binge drinking threshold with drink icons and stopwatch

How Common Is Binge Drinking?

Binge drinking is common in the United States, especially among young adults, but it affects many age groups.

The 2024 National Survey on Drug Use and Health found that 20.1 percent of people aged 12 or older reported past month binge drinking, which equals 57.9 million people in SAMHSA data from 2024.

The same report found the rate was 26.7 percent for people ages 18 to 25, 21.0 percent for adults age 26 or older, and 3.5 percent for adolescents ages 12 to 17. That does not mean binge drinking is only a college issue. It is a broad public health issue.

These numbers also do not mean every person who binge drinks has alcohol use disorder. They do show that many people drink in ways that can raise the chance of injury, poor decisions, poisoning, blackouts, and longer term problems.

What Are the Risks of Binge Drinking?

What are the risks of binge drinking? The risks can be immediate, delayed, or part of a longer pattern.

Short term risks include injury, falls, crashes, unsafe sex, violence, alcohol poisoning, blackouts, and poor judgment. A person does not need to drink daily to face these risks. One high intensity night can be enough.

Blackouts are a major warning sign. An alcohol blackout is not the same as passing out. During a blackout, a person may walk, talk, text, or seem awake, but the brain is not storing new memories well. Research on alcohol blackouts describes this as a memory formation problem, not simple sleep or unconsciousness.

Alcohol poisoning is different and can be life threatening. Warning signs can include inability to wake, repeated vomiting, seizures, slow or irregular breathing, pale or blue skin, low body temperature, or loss of consciousness. NHS guidance says to seek emergency help for suspected alcohol poisoning rather than waiting for every sign to appear.

There are also longer term risks. Repeated binge drinking can raise concern for alcohol use disorder, especially when drinking becomes hard to control or keeps causing problems. Frequent binge episodes also create more chances for injuries, conflict, missed duties, and risky situations.

High intensity drinking raises the concern even more. NIAAA uses that term for drinking at least twice the binge threshold, meaning eight or more drinks for women or ten or more for men. This does not automatically define alcohol use disorder, but it is a clear reason to pause and ask what is happening.

When Binge Drinking May Signal a Bigger Problem

A single episode may be risky without meaning someone has alcohol use disorder. Still, certain patterns deserve attention.

One of the clearest warning signs is impaired control. That might sound like, “I planned to have two drinks, then had eight,” or “I keep saying I will stop earlier, but I do not.” If that happens often, it may be more than a one time poor choice.

Another sign is drinking despite consequences. Maybe you missed work, fought with a partner, drove after drinking, got hurt, blacked out, or felt intense anxiety the next day. If those outcomes keep happening and drinking continues anyway, that is worth taking seriously.

Tolerance and withdrawal also matter. Tolerance means needing more alcohol to feel the same effect. Withdrawal can include symptoms after cutting down or stopping, such as shaking, sweating, nausea, anxiety, or feeling like alcohol is needed to feel normal. Not everyone with alcohol use disorder has withdrawal, but when it appears, it is a strong reason to get medical guidance.

Frequency matters too. Someone who binge drinks once at a wedding is in a different situation than someone who binge drinks every weekend. Research found that each step up in binge drinking frequency was tied to higher odds of alcohol use disorder severity in adults with problem substance use, based on binge frequency results.

How to Check Your Own Pattern

You do not need to label yourself to ask better questions.

Start with the facts. How many standard drinks do you have on your heaviest drinking day? How long does it take to drink that amount? How often does it happen? Do you ever drink more than planned? Have you had blackouts? Has anyone expressed concern?

Clinicians often use brief screening tools for this. The NIAAA single alcohol screening question asks how many times in the past year a person has had four or more drinks in a day for women or five or more for men. NIAAA describes this kind of quick screening as a way to identify unhealthy alcohol use and decide whether more assessment is needed.

Another tool is the AUDIT C, a three question screen that asks about drinking frequency, typical amount, and heavy drinking occasions. It is not a diagnosis, but it can help start a clearer conversation.

Clinician screening patient for binge drinking and alcohol use risks

If you are worried, it can help to track honestly for a few weeks. Write down what you drank, how fast, what happened after, and how you felt the next day. Patterns can be easier to see on paper than in memory.

What to Do If a Binge Episode Turns Dangerous

If someone has been drinking heavily and seems severely impaired, do not leave them alone to “sleep it off.” Alcohol can keep absorbing after drinking stops, so a person can get worse later.

Call emergency services if the person cannot wake up, has slow or irregular breathing, vomits repeatedly, has a seizure, has blue or pale skin, feels very cold, or loses consciousness. If you are unsure, calling is safer than waiting.

If the person is awake but impaired, focus on safety. Stop more alcohol. Do not let them drive. Keep them away from water, heights, roads, and unsafe situations. Stay with them or make sure a sober person does.

If the person is unconscious but breathing normally, place them on their side and monitor breathing while waiting for help. If they are not breathing normally or are only gasping, start CPR and follow dispatcher instructions.

These steps are not about judgment. They are about keeping someone alive.

Why This Matters

The definition of binge drinking is simple, but the real world can get messy fast.

Four or five drinks may not sound extreme in some social settings. Yet that amount, especially in about two hours, can raise blood alcohol to a level linked with major impairment. Stronger drinks, fast drinking, low food intake, or mixing alcohol with other substances can raise the risk further.

The bigger picture is also personal. If binge drinking is rare and you can stop before harm occurs, the next step may be safer planning. If binge drinking keeps happening, grows more intense, leads to blackouts, or feels hard to control, it may be time to talk with someone trained to help.

You do not need to wait for daily drinking, withdrawal, or a crisis to take your drinking seriously. Early support can make change easier and safer.

If your drinking has started to feel unsafe or hard to control, our detox program at Thoroughbred Wellness and Recovery can help you talk through the next step.

Successful professional privately struggling with high-functioning alcohol use

High-Functioning Alcoholic: The Signs People Often Miss

You can look successful and still have alcohol use that is getting harder to control. A high functioning alcoholic may keep work, bills, and relationships mostly intact while still meeting DSM 5 alcohol use disorder criteria, which can start at two symptoms in a 12 month period. This guide explains the quiet signs, what screening scores can and cannot tell you, and when to ask for help.

High Functioning Alcoholic Signs Can Be Quiet

The phrase high functioning alcoholic is not a formal diagnosis. Clinicians usually use alcohol use disorder, or AUD, because it focuses on symptoms instead of stereotypes.

Still, the phrase describes something many people recognize. Someone may show up to work, pay rent, take care of family duties, and avoid arrests or public crises. From the outside, life may look fine.

Inside, alcohol may be taking more space.

That gap is why people miss the signs. They expect alcohol problems to look dramatic. Job loss. Divorce. Legal trouble. Empty bank accounts. But DSM 5 does not require those events for alcohol use disorder. It looks at patterns like loss of control, craving, tolerance, withdrawal, risky use, and repeated failed efforts to cut down.

A functional alcoholic may not be visibly falling apart. They may be spending more private energy hiding, recovering, bargaining with themselves, or proving they are still in control.

A direct answer: if drinking keeps breaking your own rules, takes more effort to manage, or causes withdrawal symptoms, it deserves a clinical conversation even if life still looks stable.

Why Functioning Does Not Rule Out AUD

Functioning is not the same as being well. It can mean someone has enough income, support, job flexibility, tolerance, or privacy to keep consequences hidden for a while.

That matters because AUD can begin before outside consequences are obvious. DSM 5 mild AUD is based on two or three symptoms in the same year. Moderate AUD is four or five symptoms, and severe AUD is six or more.

Research also shows why symptom count alone does not tell the whole story. In one NESARC analysis, people with exactly two symptoms had a mean of 3.79 drinks per drinking day, and 28.33 percent reported weekly occasions with at least five drinks, which shows the two symptom group can include very different levels of risk.

That does not mean mild AUD is harmless. It means the details matter.

Two symptoms can look like drinking more than planned plus craving. They can also look like tolerance plus withdrawal. Those are very different safety situations, even if the symptom count is the same.

This is why the term functional alcoholic can be misleading. It focuses on what has not happened yet. No job loss. No arrest. No debt. But alcohol use disorder is not measured only by public damage. It is also measured by control, compulsion, health risk, and what happens when a person tries to stop.

Signs People Often Miss

The clearest early signs are often private. They show up in intentions, routines, and body signals before they show up in job reviews or bank statements.

Sign people missWhat it may look likeWhy it matters
Drinking more than plannedYou plan on two drinks and end up having sixIt points to loss of control, not just quantity
Failed rulesYou set limits, then keep breaking themRepeated failed cut down efforts are a DSM 5 symptom
CravingYou keep thinking about drinking or feel pulled toward itCraving can happen before public consequences
ToleranceThe same amount does less than it used toNeeding more alcohol can signal body adaptation
WithdrawalShakes, sweating, nausea, anxiety, or insomnia after cutting backWithdrawal can make stopping suddenly unsafe
Recovery timeMornings, weekends, or evenings revolve around feeling normal againLife may shrink around drinking and recovery
Quiet avoidanceYou skip hobbies, exercise, friends, or family timeAlcohol can crowd out valued parts of life
Risky useDriving after drinking or mixing alcohol with sedativesHarm can occur before an arrest or injury

The private bargain

A common sign is the private bargain: only on weekends, only beer, never before dinner, no drinking alone, no liquor in the house, no more than two.

There is nothing wrong with setting a limit. The concern is what happens next. If the rule keeps failing, the failure itself is information.

A person may say, “I can stop whenever I want,” but the pattern may show something else. They may stop for a few days, then drink more heavily. They may reduce for a week, then return to the old pattern after stress, boredom, sleep trouble, or social pressure.

This is often where shame grows. People start hiding not only the drinking, but the fact that they tried to control it and could not.

Craving can look ordinary

Craving is not always dramatic. It may not feel like a movie scene where someone is desperate for a drink.

It can sound like this: “I just need something to take the edge off.” Or, “I cannot relax without it.” Or, “Dinner feels wrong without wine.” Or, “I deserve this after today.”

Those thoughts do not prove AUD on their own. But when craving joins another symptom, such as drinking more than intended or failed efforts to cut down, it can meet the DSM 5 threshold.

Tolerance is not a badge of control

Some people take pride in being able to “hold their liquor.” I get why. It can feel like control.

But tolerance can hide risk. If it takes more alcohol to feel relaxed, social, sleepy, or numb, the body may be adapting. That can allow higher intake while the person still appears composed.

Someone may seem fine after several drinks. That does not mean their judgment, reaction time, sleep, mood, liver, blood pressure, or relationships are fine. It may only mean the warning signs are less visible.

DSM-5 alcohol use disorder criteria infographic highlighting commonly missed signs

Withdrawal changes the situation

Withdrawal is one of the biggest signs people miss because they may call it stress, anxiety, poor sleep, or a bad hangover.

It can include shaking, sweating, nausea, agitation, anxiety, insomnia, or feeling unable to function until alcohol is back in the body. Morning drinking to feel normal is especially concerning.

If withdrawal is possible, do not treat it as a willpower issue. Alcohol withdrawal can be medically serious. ASAM notes that withdrawal management should include assessment of symptoms, risk factors, and safety needs, and that withdrawal management is not the same as ongoing AUD treatment.

How Screening Scores Fit

Screening tools can help, but they are not a diagnosis.

AUDIT C is a short alcohol screen. It asks about drinking frequency, typical amount, and heavy drinking occasions. The U.S. Preventive Services Task Force describes AUDIT C as one of the brief adult tools with good accuracy for identifying unhealthy alcohol use in primary care, but an AUDIT C result still needs follow up.

A common U.S. cutoff is 4 or more for men and 3 or more for women. Those common cutoffs are screening thresholds, not proof that someone has AUD.

The full AUDIT gives more information because it includes questions about dependence related symptoms and alcohol related harms. The World Health Organization states that a full AUDIT score of 8 or more suggests hazardous or harmful alcohol use and possible dependence, and that higher ranges call for closer clinical follow up.

In plain terms, a positive AUDIT C means, “Look closer.” It does not mean, “You are diagnosed.”

A full AUDIT score of 16 or higher is a strong reason to choose clinical evaluation over trying to manage drinking alone. A score of 20 or higher is an even stronger reason to get prompt diagnostic assessment, including withdrawal risk.

Alcohol screening pathway showing when clinical evaluation and withdrawal care are needed

Scores also do not override red flags. Morning drinking, withdrawal symptoms, repeated blackouts, unsafe driving, pregnancy related alcohol exposure, suicidal thoughts, injury, or repeated inability to follow limits should lead to help regardless of the number.

When Moderation Is Not Enough

Moderation can be a reasonable goal for some people with risky drinking who do not have AUD, withdrawal risk, or serious alcohol related harm. But self guided moderation becomes less safe when drinking has already become hard to control.

The question is not, “Are you strong enough?”

The better question is, “What has happened when you tried to change?”

If you repeatedly set limits and break them, that is not a character flaw. It is a clinical sign. If you need alcohol to feel normal, sleep, steady your hands, calm your nerves, or get through the morning, that is a safety concern. If you keep drinking despite health, mood, relationship, or work problems, the pattern needs more than another private promise.

A functional alcoholic may be able to hide the pattern longer than others. That can delay help. It can also make the first conversation harder because the person can point to visible success as proof that nothing serious is happening.

But visible success does not answer the real questions. Can you stop when you plan to stop? Can you take alcohol or leave it? Are you honest about how much you drink? Do you feel worse when you do not drink? Is your life getting smaller around alcohol?

Talking With A Functional Alcoholic

If you are worried about someone else, try to stay specific. Labels often start fights. Observations are harder to dismiss.

Instead of saying, “You are an alcoholic,” you might say, “I have noticed you often plan to have two drinks and then keep going,” or, “I am worried that you feel shaky in the morning and drink to feel normal.”

Pick a time when the person is sober. Keep the first conversation short. Avoid debating whether they are “bad enough” for help. That debate can go nowhere because high functioning people often compare themselves to someone worse.

It may help to focus on goals they already care about: sleep, mood, energy, parenting, work, fitness, anxiety, blood pressure, memory, or the relationship.

If the conversation becomes unsafe, step back. Concern does not mean you have to accept threats, impaired driving, violence, or chaos at home. Strong boundaries can be loving when they protect safety.

For family members, it can also help to track concrete patterns before a clinical visit: number of drinking days, rough amount, time of first drink, morning symptoms, failed cut down efforts, blackouts, injuries, and any use of alcohol to relieve withdrawal. That kind of detail helps a clinician assess risk without turning the conversation into name calling.

High Functioning Alcoholic Help Starts With Clarity

The goal is not to scare someone into a label. The goal is to see the pattern clearly enough to choose the next safe step.

If drinking is risky but there are no AUD symptoms, a brief intervention and a planned reduction goal may help. If there are two or more DSM 5 symptoms, a diagnostic assessment makes sense. If there is withdrawal, morning drinking, or a history of severe symptoms when cutting back, medical guidance is important before stopping suddenly.

Clarity also means being honest about what “functioning” costs.

Some people keep performing by using enormous effort. They drink at night, recover in the morning, push through work, and collapse again later. They may look dependable while feeling trapped. Over time, that cycle can affect sleep, mood, health, trust, and self respect.

There is no need to wait for the worst day of your life to ask for help. In fact, asking earlier can preserve more of what matters.

Why Early Action Matters

Alcohol problems often become harder to treat when they are hidden for years. Not because people are hopeless, but because routines get stronger. The brain and body adapt. Relationships adjust around the pattern. Denial becomes easier when the outside world still gives proof of success.

Early action can interrupt that. It can turn a quiet worry into a plan.

That plan might start with a primary care visit, an AUDIT assessment, a DSM 5 symptom review, therapy, medication evaluation, outpatient treatment, family support, or medically supervised detox if withdrawal risk is present.

The main point is simple: you do not have to decide alone whether you are “really” a high functioning alcoholic or whether your loved one is “bad enough” for care. If alcohol is taking more control than it used to, that is enough reason to talk with someone trained to assess it.

If drinking feels harder to control than it looks from the outside, reach out to Thoroughbred Wellness and Recovery for detox and outpatient care today.