Concerned adult beside wine glass showing hidden signs of alcohol use disorder

Signs of Alcoholism: How to Recognize Alcohol Use Disorder

If you are worried about the signs of alcoholism, look for patterns, not stereotypes. Alcohol use disorder can be diagnosed when at least two symptoms happen within the same 12 month period, even if someone keeps their job, home, and relationships. This guide will help you understand what counts, what physical signs mean, and when alcohol withdrawal needs medical care.

Signs of Alcoholism Under DSM 5

The word “alcoholic” is still common, but it is not the current clinical diagnosis. The current term is alcohol use disorder, often shortened to AUD. If you are asking, “am i an alcoholic,” a better question is, “Does my drinking meet alcohol use disorder dsm 5 criteria?”

The DSM 5 alcohol use disorder framework does not require a person to be homeless, arrested, unemployed, divorced, or visibly intoxicated in public. It focuses on symptoms. Those symptoms can be private, hidden, or easy to excuse.

A direct answer is this: alcohol use disorder is a pattern of alcohol use that causes real distress or impairment, shown by at least two of 11 symptoms in the same 12 month period.

That means someone can seem outwardly fine and still have AUD. They may go to work, pay bills, parent their children, and show up at social events. But inside, they may be fighting cravings, breaking their own drinking limits, or using alcohol even when they know it is harming their health.

The 11 DSM 5 symptoms in plain language

The DSM 5 TR criteria are often grouped into impaired control, social problems, risky use, tolerance, and withdrawal. In plain language, the signs include:

  • Drinking more, or for longer, than you meant to
  • Wanting to cut down or stop but not being able to do it
  • Spending a lot of time drinking, getting alcohol, or recovering from drinking
  • Craving alcohol or feeling a strong urge to drink
  • Drinking causing missed work, school, parenting, or home duties
  • Drinking continuing even though it causes conflict with other people
  • Giving up or reducing important activities because of alcohol
  • Drinking in risky situations, such as before driving or unsafe work
  • Drinking even after knowing it worsens a physical or mental health problem
  • Needing more alcohol than before to feel the same effect
  • Having withdrawal symptoms, or drinking to avoid them

A person does not need all of these symptoms. Two or three symptoms are classified as mild AUD. Four or five are moderate AUD. Six or more are severe AUD.

That severity label matters, but it is not a moral score. It also does not decide treatment setting by itself.

Why stereotypes miss the problem

Many people delay getting help because they do not match the image they have in mind. They may think, “I do not drink in the morning,” or “I only drink wine,” or “My friends drink this much too.”

Those details can matter, but they do not rule out AUD. The key issue is what alcohol is doing in your life. Are you keeping promises to yourself? Are you able to stop once you start? Are you drinking despite anxiety, sleep problems, liver concerns, relationship strain, or risky behavior?

The DSM shift also matters because older labels separated alcohol abuse and dependence. The DSM 5 change moved alcohol problems into one spectrum and added craving while removing legal problems as a separate criterion. That helps explain why no arrest record does not mean no disorder.

What Is Alcohol Use Disorder?

What is alcohol use disorder? It is a clinical diagnosis based on specific symptoms, not a label for a certain “type” of person.

AUD can show up as a loss of control. You plan to have two drinks but keep having five. You decide not to drink during the week but return to nightly drinking. You try a sober month and stop after a few days, again and again.

It can show up as craving. You may think about alcohol during work, feel restless when plans change, or feel unable to relax unless drinking is available.

It can also show up as continued use despite harm. You may know alcohol worsens anxiety, depression, sleep, blood pressure, stomach symptoms, or relationship conflict, yet keep drinking anyway.

A person can drink heavily and not meet AUD criteria if those symptoms are not present. A person can also drink in a way others see as normal and still meet criteria. The diagnosis depends on the pattern, not only the number of drinks.

Mild does not mean harmless

Mild AUD means two or three symptoms. That may sound small, but two symptoms can be serious.

For example, repeated failed efforts to cut down plus drinking more than intended can show that alcohol is no longer fully under your control. That is worth taking seriously before bigger losses happen.

At the same time, mild AUD does not automatically mean someone needs inpatient care. It means they need honest assessment and a plan that fits their risk.

Moderate AUD often points to a wider pattern across several parts of life. Severe AUD means many symptoms are present, but even severe AUD does not always mean the same level of care for every person.

Physical Signs of Alcoholism

Physical signs of alcoholism are not always obvious. Some people look tired, flushed, shaky, or unwell. Others look healthy while alcohol is still causing harm.

The most useful physical clues are often tied to timing. Symptoms that appear after several hours without alcohol, especially in the morning, can be more concerning than symptoms that happen only during drinking.

Common early physical clues may include poor sleep, fatigue, stomach upset, appetite changes, weight changes, repeated injuries, or higher tolerance. These signs are not proof of AUD. They can come from many causes. But if they occur with loss of control, craving, or repeated failed efforts to cut down, they deserve attention.

Morning shaking can mean withdrawal

Morning tremor, sweating, nausea, anxiety, agitation, racing heart, and insomnia can be signs of alcohol withdrawal when they happen after heavy or regular drinking is stopped or reduced. Cleveland Clinic describes withdrawal symptoms as possible within hours after a person stops or sharply reduces alcohol.

This is one of the most important safety points in the whole article. If someone wakes up shaky, sweaty, nauseated, or panicky, then drinks to feel normal, that may not be “just a hangover.” It may mean the nervous system has adapted to alcohol.

Withdrawal can occur even if alcohol is still in the body. In people with dependence, a sharp drop from their usual alcohol level can trigger symptoms.

Hangover and withdrawal can overlap

A hangover can cause headache, nausea, fatigue, thirst, and anxiety after a heavy drinking episode. Withdrawal can cause nausea and anxiety too, but it often adds tremor, sweating, agitation, insomnia, fast heart rate, and rising blood pressure.

The pattern matters. A one time rough morning after unusual drinking is different from waking most days with shaking and needing alcohol to settle.

If symptoms worsen when alcohol is delayed, or improve after drinking, that is a warning sign. It is also a reason not to quit suddenly without medical advice if drinking has been heavy or daily.
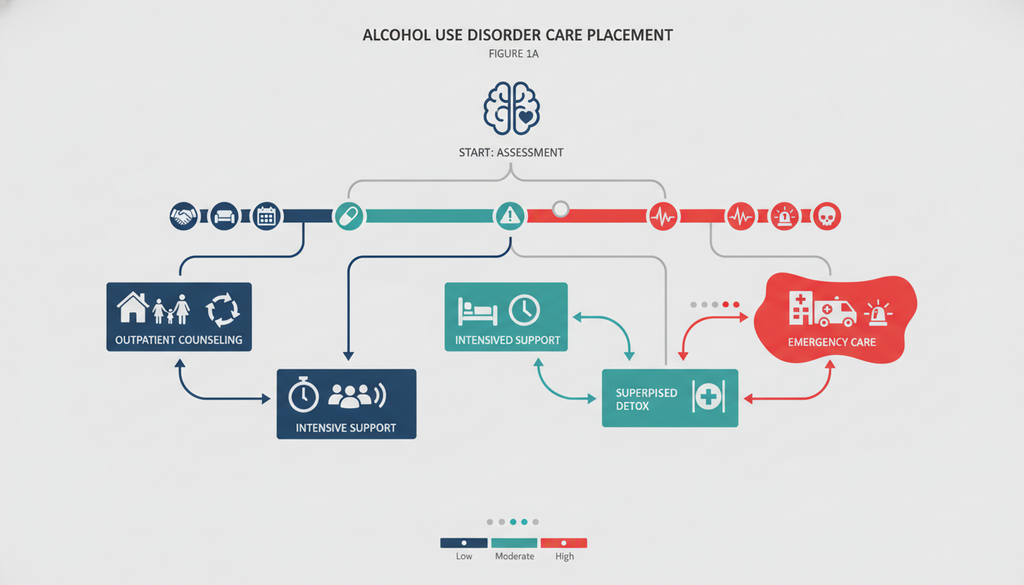
Alcohol use disorder level of care pathway with withdrawal and safety risks

Am I an Alcoholic?

If you are searching “am i an alcoholic,” you are probably not looking for a lecture. You may be scared, embarrassed, irritated, or quietly hoping someone says you are fine.

I think the most honest answer is this: you do not need to accept the label “alcoholic” to take alcohol use disorder seriously.

Try asking more specific questions. Do I drink more than I plan to? Have I tried to cut down and failed? Do I crave alcohol? Do I hide how much I drink? Do I keep drinking when it makes my sleep, mood, health, or relationships worse? Have I driven after drinking or taken other risks?

If the answer to two or more is yes, an evaluation is worth it.

When an am i an alcoholic quiz helps

An am i an alcoholic quiz can help you notice patterns. It can give language to things you have been minimizing. It can also push you to talk to a professional sooner.

But a quiz is not a diagnosis. It cannot fully judge withdrawal risk, mental health, medical problems, medications, family history, or whether detox should be supervised.

A good assessment looks at both AUD symptoms and safety. It asks how much you drink, how often, what happens when you stop, whether you have had seizures or hallucinations, and whether you have depression, trauma symptoms, anxiety, or suicidal thoughts.

Merck notes that diagnosis relies on a careful clinical history, because appearance and lab results alone cannot tell the whole story.

If you are asking for someone else

It is painful to watch someone drink in a way that scares you. It is also tempting to argue over labels. That usually does not help.

Instead, describe what you see. You might say, “I am worried because you planned not to drink this week and ended up drinking every night,” or “I noticed you were shaking this morning and felt better after drinking.”

Stick to facts. Avoid shame. If there are withdrawal symptoms, confusion, seizures, hallucinations, unsafe driving, or suicidal talk, treat it as a safety issue, not a debate.

When Stopping Drinking Can Be Unsafe

Not everyone who drinks needs detox. But some people should not stop abruptly on their own.

Alcohol withdrawal can become dangerous. The risk is higher if someone drinks heavily every day, has had withdrawal before, has had seizures or delirium, uses sedatives, has major medical illness, is older, or has severe anxiety, depression, or suicidal thoughts.

ASAM guidance on alcohol withdrawal warns that withdrawal risk must be assessed with more than a current symptom score. A person can seem only mildly uncomfortable early on and still get worse later.

Seizures often occur after alcohol is stopped or sharply reduced. Delirium tremens can occur later and may involve confusion, hallucinations, agitation, fever, tremor, and unstable heart rate or blood pressure. That is a medical emergency.

If there is a seizure, confusion, hallucinations, fainting, chest pain, persistent vomiting, severe shaking, unstable vital signs, or suicidal intent, emergency care is needed.

Why “just cut back” can be risky

People often try to manage withdrawal by drinking less each day. Sometimes they do this because they are afraid of detox, work responsibilities, cost, or stigma.

The problem is that withdrawal risk is not only about willpower. It is about brain and body adaptation. If the body has become dependent on alcohol, stopping or reducing too fast can trigger dangerous symptoms.

The World Health Organization states that benzodiazepines are the first line medication class for alcohol withdrawal because they reduce symptoms and help prevent seizures and delirium. These medicines need medical oversight, especially because mixing sedatives with alcohol can be dangerous.

Detox is not a punishment. It is medical support during a risky period.

Why Level of Care Is Not Just Severity

DSM 5 tells clinicians whether alcohol use disorder is present and how many symptoms are present. It does not, by itself, decide whether someone needs outpatient care, intensive outpatient care, residential treatment, or inpatient medical care.
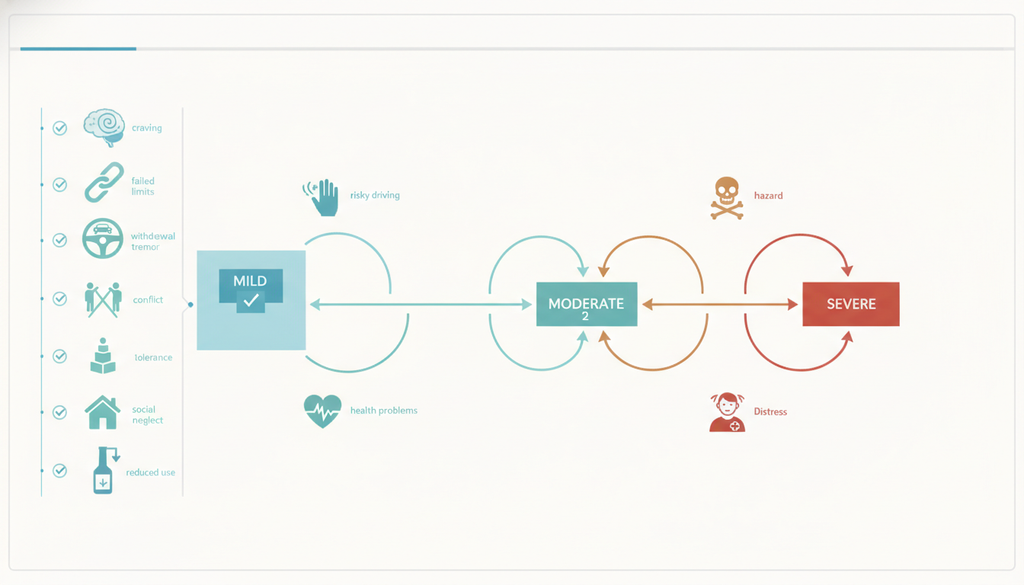
DSM-5 alcohol use disorder criteria shown as symptom and severity infographic

That is where ASAM comes in. The ASAM Criteria use a broad assessment that looks at withdrawal risk, medical needs, mental health, substance use risks, recovery environment, and personal needs.

This matters because two people with the same AUD severity can need very different care.

One person with mild AUD may have no withdrawal risk, stable housing, and good support. Outpatient counseling, medication evaluation, and monitoring may fit.

Another person with mild AUD may have withdrawal symptoms, a prior seizure, and sedative use. That person may need supervised withdrawal care even though the DSM symptom count is low.

A person with severe AUD may need residential or inpatient care if withdrawal, medical issues, psychiatric symptoms, or safety risks are high. But another person with severe AUD may be stable enough for intensive outpatient treatment if they have safe housing, no acute withdrawal risk, strong support, and reliable care.

Treatment should match risk and goals

Good alcohol treatment is not one size fits all. It should match the person in front of you.

Some people need medical detox first. Some need outpatient therapy and medication. Some need dual diagnosis care for anxiety, depression, trauma, bipolar disorder, or other mental health concerns. Some need family support, peer support, or a safer living environment.

The best plan answers three separate questions. Does the person meet criteria for AUD? How severe is it by symptom count? What setting is safe and useful right now?

Keeping those questions separate prevents two common mistakes. The first is minimizing risk because someone looks successful. The second is forcing a higher level of care based only on a label.

What to Do Next

Alcohol use disorder is common enough that it can hide in plain sight. The signs are not always dramatic. They may look like broken promises to yourself, repeated “rules” that fail, morning shaking, sleep problems, anxiety after drinking, or a quiet fear that alcohol is starting to run the day.

If you recognize yourself in this article, try not to turn it into a character judgment. Treat it as information. AUD is a health condition with different levels of severity and many paths into care.

If you are worried about withdrawal, do not stop suddenly without medical advice. If you are having severe symptoms, get emergency help. If the concern is less urgent but still real, talk with a qualified addiction or mental health professional and be honest about your drinking pattern, morning symptoms, medications, and mental health.

You do not have to wait for a crisis to ask for help. If alcohol is causing harm or you feel unsure about stopping safely, consider reaching out to Thoroughbred Wellness and Recovery for detox support.

Tired adult postponing morning driving while alcohol has time to metabolize

How to Sober Up: Why Time Is the Only Thing That Works

If you are trying to sober up fast, the hard truth is that coffee, showers, food, and sleep will not clear alcohol from your body. The only real answer is time: after absorption, alcohol metabolism often averages about 0.015 percent BAC per hour, so a high BAC can still matter the next morning. This guide explains how to sober up, how long to sober up, and when driving or being alone is not safe.

How to Sober Up: The Plain Answer

The direct answer is this: you sober up when your body has had enough time to metabolize the alcohol, not when you feel awake.

That answer can feel frustrating, especially if you need to get to work, pick up a car, fly home, or care for someone else. Still, it is the safest answer. Your liver does the work, and you cannot force it to work much faster with common tricks.

The phrase how to sober up fast gets searched a lot because people want a quick fix. I get why. No one wants to sit with nausea, anxiety, regret, or the worry that they may still be over a legal limit. But how to sober up quickly and how to feel a little better are not the same question.

You may feel more alert after coffee. You may feel cleaner after a shower. You may feel steadier after food or water. None of those prove your BAC is low enough to drive, work safely, or make clear choices.

Why Alcohol Takes Time to Leave

Alcohol moves through your body in stages. First, it is absorbed from the stomach and intestines into the bloodstream. Then BAC rises to a peak. After that, the body clears alcohol, mostly through liver metabolism.

The tricky part is that BAC can keep rising after the last drink. Food can delay alcohol absorption and may lower the peak, but it does not make alcohol vanish once it is in the bloodstream. This is why the timing of alcohol absorption matters before anyone tries to estimate when they may be sober.

So if you stop drinking at midnight, that does not always mean your BAC starts falling at midnight. If you had food, drank quickly, or had several strong drinks late in the night, your peak may happen after you stop drinking.

That is one reason the next morning can be risky. You may wake up feeling different from how you felt at 1 a.m., but different does not always mean sober.

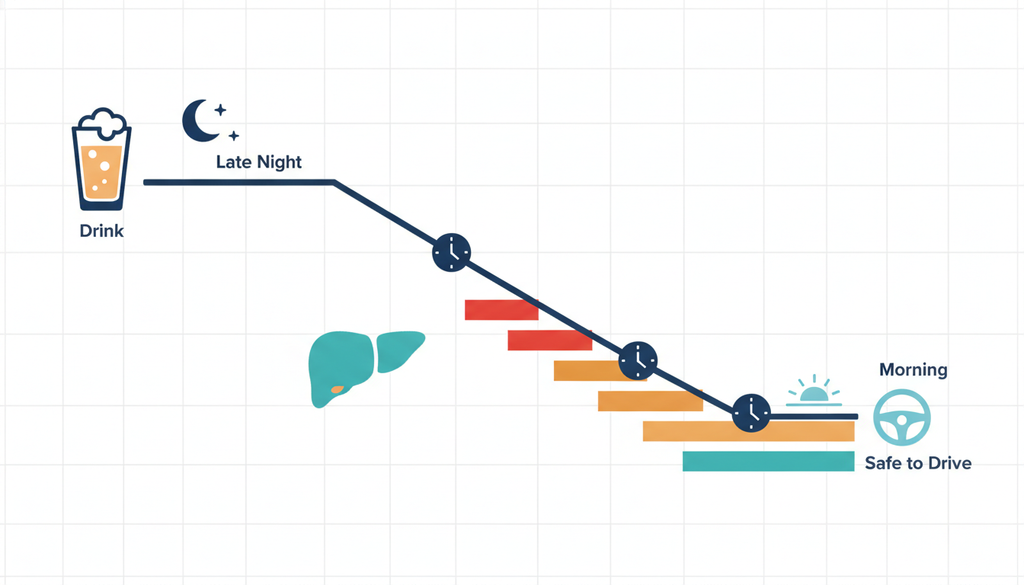
Alcohol metabolism is also variable. A commonly used average is about 0.015 percent BAC per hour, but the reported range is much wider. Some estimates use 0.010 percent to 0.012 percent per hour when the stakes are high, such as driving, because slower assumptions leave a wider safety margin.

How Long Does It Take to Sober Up?

How long does it take to sober up? It depends on your peak BAC, when your BAC actually peaked, how much you drank, how strong the drinks were, and how fast your body is clearing alcohol.

A useful example starts with a known BAC, not a guess from drink count. If a person has a known post absorption BAC of 0.15 percent, conservative math suggests it may take about 5.8 to 7 hours to fall below 0.08 percent, 8.3 to 10 hours to fall below 0.05 percent, and 10.8 to 13 hours to fall below 0.02 percent. Those estimates come from a known BAC calculation, not from how the person feels.

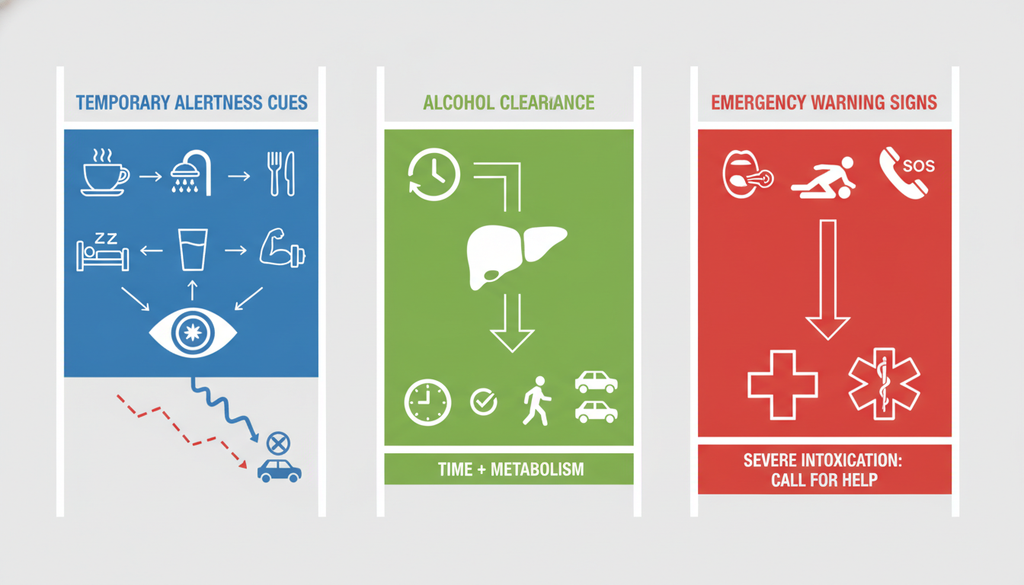
Alcohol metabolism infographic showing BAC declining slowly overnight

That means someone who peaks at 0.15 percent around 1 a.m. may still have alcohol in their system at breakfast. They may even be near or above some legal limits during a morning commute.

Drink counts are weaker than BAC math because casual drink names hide the real dose. A large glass of wine, a strong beer, a double pour, or a canned cocktail can contain more alcohol than people think. The National Institute on Alcohol Abuse and Alcoholism shows that drink size can change the total number of standard drinks, and its drink size examples include containers that hold several standard drinks.

This is why “I only had three drinks” may not mean much unless you know the serving size, alcohol percentage, and timing. Three strong pints are not the same as three small light beers. A bottle of wine is not one standard drink.

What Helps and What Does Not

Some things can help you feel safer and more comfortable while you wait. Water may help thirst. Food may help nausea. Sleep may give your body time to clear alcohol. A calm room and a trusted person nearby can reduce risk.

But none of those speed alcohol metabolism in a way you can count on. If you are searching how to sober up fast from alcohol, the safest answer is still to stop drinking, wait, avoid driving, and get help if symptoms are severe.

Common ideaWhat it may doWhat it cannot do
CoffeeMay make you feel more awakeDoes not lower BAC
Cold showerMay make you feel shocked or alertDoes not clear alcohol
Food after drinkingMay settle your stomachDoes not remove alcohol from blood
WaterMay help thirst or dehydration symptomsDoes not make the liver process alcohol fast
SleepLets time passDoes not speed metabolism by itself
ExerciseMay make you feel energizedDoes not make driving safe

Coffee deserves special caution. It can make people feel more capable than they are. In research on alcohol and caffeine, adding energy drinks did not reliably reverse objective alcohol related impairment, yet willingness to drive could increase.

Sleep can also mislead you. In one driving simulator study, severe sleep loss harmed driving performance, and coffee did not fix the sleep deprived driving problem. So the morning after drinking can involve two problems at once: alcohol that remains in the body and fatigue from poor or short sleep.

That combination is why feeling awake is not enough. You can be more awake and still be impaired.

Alcohol Metabolism and Driving Risk

Driving after drinking is not a vibe check. It is not about whether you can walk straight, speak clearly, or convince yourself you are fine.

BAC limits also vary. Across much of Europe, 0.5 g/L is a common general limit, but some places use lower limits, including 0.0 g/L or 0.2 g/L, and some driver groups face stricter rules. The European Transport Safety Council tracks European limits by country and driver category.

That matters because a person might be below one legal threshold but above another. Someone may also be under a legal number and still be unsafe because of fatigue, hangover symptoms, medication, or poor sleep.

A home estimate or online calculator can be useful as a warning sign. It can tell you when residual alcohol is plausible. It should not be used as permission to drive, especially when the result is near a limit.

If you are asking how to sober up quick so you can drive, the better question is whether you can avoid driving at all. If there is any real doubt, use a ride service, public transit, a sober driver, or delay the trip.

Infographic comparing sobriety myths, safe transport, and alcohol emergency signs

How to Sober Up From Alcohol Safely

The safest way to sober up from alcohol is simple, though not always convenient: stop drinking, give your body time, avoid more substances, and do not drive until alcohol is clearly out of the picture.

If you are with someone who has been drinking, stay alert for signs that this is no longer a normal hangover or ordinary intoxication. Alcohol can become a medical emergency, especially when a person cannot wake up, vomits while very drowsy, has slow or irregular breathing, turns blue or very pale, has a seizure, or seems unable to stay conscious. NIAAA warns that suspected alcohol overdose calls for 911 and should not be managed by letting someone sleep it off.

Do not give coffee, force food, put the person in a shower, or try to make them vomit. Those actions can be unsafe when someone is very intoxicated or not fully awake.

If the person is unresponsive but breathing normally, first aid guidance in the research supports placing them on their side and monitoring breathing while help is on the way. If breathing is absent or not normal, emergency instructions and CPR guidance matter right away.

For your own drinking, a safer plan starts before the first drink. Know how you will get home. Avoid driving your own car to drinking events if you might feel tempted to retrieve it early. Be careful with strong drinks, large pours, and drinks you did not measure. Do not mix alcohol with sedating medications or unknown pills.

If you often search how to sober up, how long to sober up, or how to sober up from alcohol after nights you did not plan to drink heavily, that may be a sign to pause and look at the pattern. Needing frequent recovery strategies is not a personal failure. It is information.

Why The Morning After Can Fool You

The morning after drinking is confusing because your body can feel partly recovered while alcohol is still present. The room may no longer spin. Your speech may sound normal. You may remember your plans for the day. You may even feel embarrassed and eager to prove you are fine.

But BAC does not care how motivated you are. It falls over time. If you drank late, drank heavily, or had strong drinks, the clock may not have had enough time to do the work.

Hangover symptoms can also affect performance even after BAC falls. Headache, nausea, anxiety, poor sleep, dehydration, and low attention can all make driving or work tasks harder. A legal limit is not the same as a safety guarantee.

This is why the only honest answer to how to sober up fast is that there is no shortcut. You can support your body, avoid more risk, and wait. You cannot rush your liver enough to make coffee, a shower, or breakfast into a sobriety tool.

Why This Matters

This matters because the wrong answer can hurt people. Believing a myth can lead to a morning drive with residual alcohol, a workplace mistake, a fall, a medical emergency, or a decision you would not make sober.

Time is not exciting advice, but it is the advice that matches the science. Alcohol metabolism has limits. Subjective alertness is unreliable. Legal thresholds vary. Severe intoxication can become dangerous after the last drink.

So if you are trying to sober up, choose the boring safe plan. Stop drinking. Wait longer than feels convenient. Do not drive on a guess. Get medical help if someone is hard to wake or breathing abnormally. And if alcohol is starting to feel hard to control, ask for support before the next crisis.

If alcohol is becoming hard to manage, our medical detox program at Thoroughbred Wellness and Recovery can help you take the next safe step.

Adult in recovery observing healing meth sores on the face

Meth Face: Sores, Scarring and How Skin Heals in Recovery

Meth face can improve in recovery, but sores that are infected, deep, or repeatedly picked need medical care, not just time. For example, a drainable abscess usually needs incision and drainage under the IDSA skin infection guideline, while a small clean scratch may heal once picking stops. This article explains what causes meth sores on face, when to get help, and what healing can look like.

What Meth Face Usually Means

Direct answer: meth face is not one single skin disease, but a common label for facial sores, scabs, acne like lesions, scars, and skin changes linked to meth use, picking, infection risk, and poor healing conditions.

The phrase can sound harsh. It can also be misleading. A person may have facial sores during meth use for several reasons, and some of those reasons have nothing to do with meth itself. Acne, eczema, bacterial infection, dental problems, compulsive skin picking, and other medical issues can all leave marks on the face.

Still, meth can set up a clear pattern. Some people feel crawling, biting, or itching sensations on or under the skin. This is called formication. Dentalcare describes formication as a physical indicator that may occur with stimulant use, and that false crawling feeling can lead to repeated scratching or picking at the skin surface until small marks become open wounds.

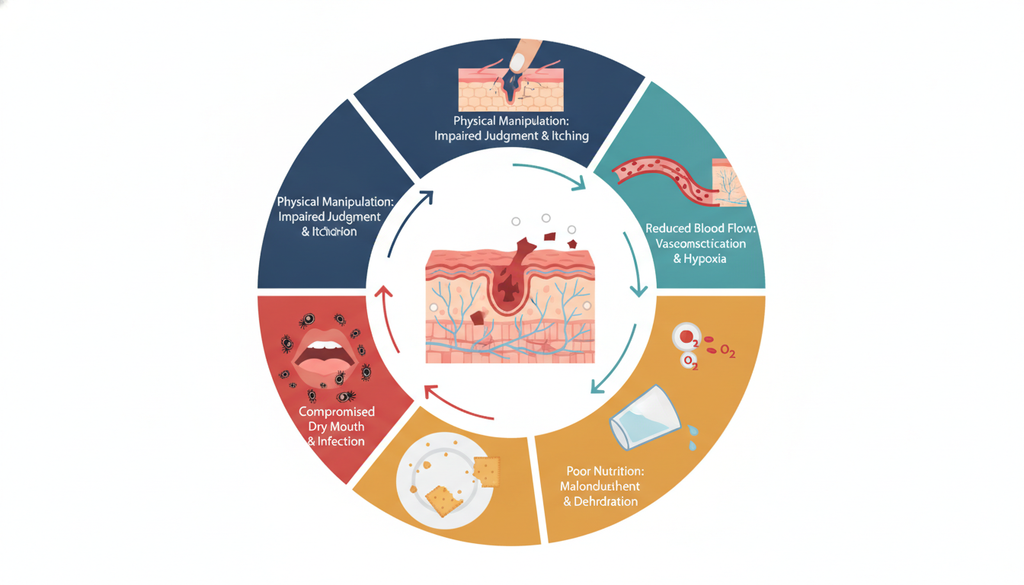
That cycle matters more than the label. A sore that is touched, squeezed, scraped, or reopened every day cannot close well. The body tries to build new skin, but the new edge gets torn away again. Over time, a small blemish can become a scab, crater, dark spot, pale spot, or scar.

Why Meth Sores on Face Can Stay Open

Meth sores on face often stay open because several problems happen at once. The skin is injured. The person may be sleeping less. Food and water intake may drop. Hygiene may slip. Stress and anxiety may rise. If infection starts, healing becomes harder.

The most direct cause is repeated trauma. Picking removes scabs and damages the fragile new skin that is trying to grow across the wound. It can also move bacteria from hands, fingernails, towels, bedding, phones, razors, or other surfaces into broken skin.

Meth may also affect healing in more direct ways. In a mouse study, methamphetamine delayed wound healing, and the delay was greatest when wounds were infected with MRSA, a type of drug resistant staph. That mouse wound research supports concern, but it does not prove exactly how long a human facial sore will take to heal.

Blood flow may play a role too. Meth is a stimulant, and stimulant effects can tighten blood vessels. In theory, less local blood flow can mean less oxygen, fewer nutrients, and less immune support reaching the skin. But the research provided does not prove a precise facial blood flow change in people. It is better to say that meth can create a poor healing setting, especially when picking, poor sleep, dehydration, and infection are also present.

Dry mouth and dental disease can matter as well. A small study found that methamphetamine use was linked with altered oral bacteria, including lower salivary bacterial richness among users. The oral microbiota finding does not prove that mouth bacteria cause most facial sores, but it does support paying attention to dental pain, gum infection, jaw swelling, and wounds near the lips or mouth.

The face also has special risks. It is close to the eyes, nose, sinuses, mouth, teeth, and deeper facial spaces. That means a sore on the cheek, nose, lip, or near the eye should be taken seriously if it becomes swollen, painful, hot, or starts draining pus.

When Meth Face Needs Medical Care

Some small surface wounds can heal with basic care once meth use stops and picking decreases. But not every facial sore should be watched at home. Infection can move beyond the skin. Abscesses can trap pus. Eye related infections can threaten vision. Rarely, fast moving deep infections can become life threatening.

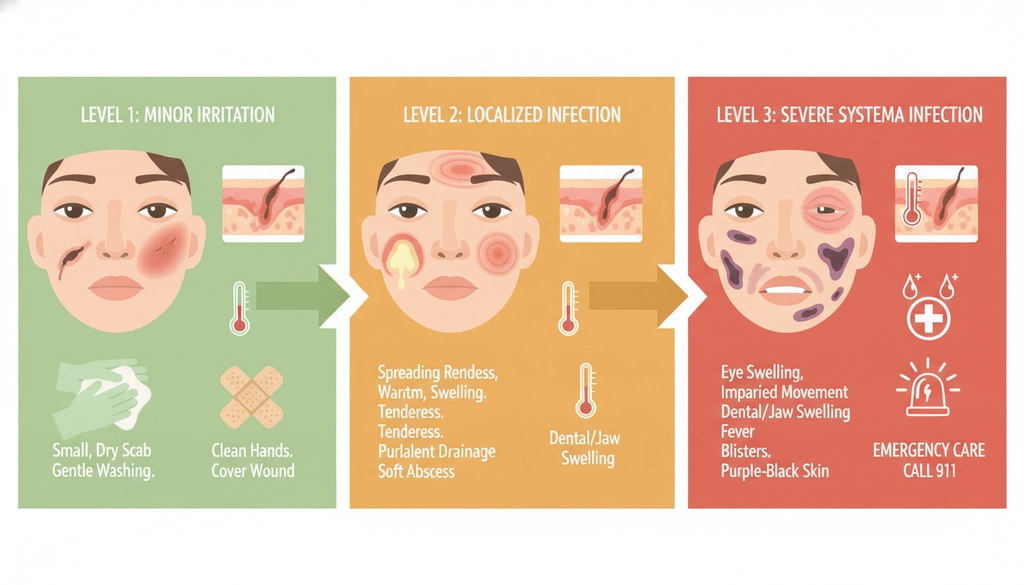
A facial wound needs medical care when it is getting worse instead of better. Warning signs include spreading redness, warmth, swelling, worsening pain, pus, bad odor, fever, chills, or a soft pocket under the skin. Merck describes cellulitis as a bacterial skin infection that can cause redness, warmth, swelling, and tenderness, and facial cellulitis should not be dismissed as only a picked sore.

What you noticeWhat it may meanWhat to do
Small scab that is dry, clean, and clearly shrinkingSurface injuryProtect it, stop picking, and seek routine care if it stalls
Redness spreading beyond the sore with warmth and tendernessCellulitisGet same day medical care
Pus, a boil like bump, or a soft pocket under the skinAbscessGet examined for drainage and possible culture
Pain, swelling, or sores near the eye with vision change or pain moving the eyeEye area infectionSeek urgent care or emergency care
Tooth pain, jaw swelling, trouble opening the mouth, or trouble swallowingDental or deep facial infectionSeek urgent medical or dental care
Severe pain, purple or black skin, blisters, confusion, fever, or rapid worseningDeep severe infectionGo to the emergency department

Abscesses are a common point of confusion. If there is trapped pus, antibiotics alone may not solve the problem. The IDSA guideline says incision and drainage is the treatment for cutaneous abscesses, large boils, carbuncles, and inflamed epidermoid cysts. The face is also a sensitive area. The Society for Academic Emergency Medicine notes that abscesses on the face or near important structures may need specialty input because of anatomy and cosmetic risk, so home squeezing is not safe for a facial abscess.

Eye symptoms raise the urgency. Merck explains that orbital cellulitis involves tissue behind the orbital septum and can threaten vision or spread to deeper structures. Pain with eye movement, double vision, bulging of the eye, reduced vision, or trouble moving the eye should be treated as a possible orbital infection, not a simple skin sore.

Severe pain is another red flag. Merck describes necrotizing soft tissue infection as a fast moving infection that can begin with pain out of proportion to what the skin looks like. If pain is extreme, swelling spreads quickly, skin turns purple, gray, or black, blisters appear, or the person seems very ill, possible necrotizing infection needs emergency care.

Facial wound warning signs requiring same-day or emergency treatment

Scarring and Skin Healing in Recovery

Healing starts when the injury cycle slows down. That sounds simple, but it can be hard. Meth use can bring urges to pick, long periods without sleep, anxiety, paranoia, and body focused checking in mirrors. Recovery is not only about stopping a drug. It is also about helping the brain and body settle enough for skin care to work.

A superficial sore can improve when the area stays clean, protected, and left alone. New skin grows from the edges. Inflammation fades. The scab loosens on its own. The color may look pink, red, brown, or lighter than nearby skin for a while. Scars can keep changing for months after a wound closes.

Deep wounds are different. If a sore was repeatedly opened, infected, or ulcerated, it may heal with a depressed scar, thick scar, dark mark, or pale mark. The face may look uneven for some time. That can be upsetting, especially when the marks are tied to a painful period of life.

Infographic showing why meth-associated facial sores may not heal

Try not to judge healing day by day. Skin recovery is often uneven. Some areas close quickly. Others reopen because they sit near the mouth, nose, beard area, or places touched often. Shaving, cosmetics, harsh scrubs, adhesive bandages, and aggressive cleaning can irritate healing skin.

The safest general approach is gentle. Wash with mild soap and water. Avoid picking. Avoid squeezing bumps. Keep hands and nails clean. Cover spots if a clinician recommends it. Do not use sharp tools, needles, or heat on facial sores. Do not share antibiotics or use leftover medication. If the wound looks infected, get care rather than trying to dry it out or drain it at home.

Nutrition and rest also support repair. The skin needs protein, calories, fluids, and enough sleep to rebuild. This does not mean vitamins can fix an abscess or that food replaces medical care. It means the body heals better when basic needs are met.

How Meth Face Heals in Recovery

Meth face usually improves in stages. First, the person may stop creating new wounds as meth use decreases and sleep returns. Next, existing scabs begin to close. Then redness and irritation settle. Later, color changes and scars soften slowly.

The hardest part is often stopping the picking loop. If formication or stimulant related paranoia is present, the person may truly feel like something is under the skin. Telling someone to “just stop” rarely helps. It may increase shame and secrecy. A better approach is to treat the substance use, restore sleep, address anxiety or psychosis if present, and use wound care that reduces the chance of re injury.

If injection drug use is part of the picture, the threshold for care should be lower. A 2025 review of skin and soft tissue infections in people who inject drugs notes that staph and streptococci are common causes, and infections may also be mixed with other bacteria. The review supports concern for MRSA and more serious infection risk in injection drug settings, but that risk should not be assumed for every person who uses meth by a non injection route.

A clinician may ask about drug route, sleep, picking, fever, dental symptoms, prior MRSA, diabetes, HIV, immune problems, and whether the sore is spreading. That is not about blame. It is about choosing the right care. A surface scratch, cellulitis, an abscess, dental infection, and an eye area infection all need different responses.

Recovery care should also include mental health support when picking feels compulsive or tied to fear, anxiety, or skin sensations. Some people continue picking after they stop meth because the habit has become automatic. Others pick mainly during stimulant use and improve greatly with abstinence. Either way, support works better than shame.

If sores are healing but scars remain, a primary care clinician or dermatologist can guide scar care once the skin is closed and infection is gone. The key is timing. Scar treatments should not be used on open, infected, or draining wounds unless a clinician tells you to.

Why This Matters for Real Recovery

Facial sores can carry a heavy emotional load. They are visible. People stare. Loved ones may panic. The person healing may feel embarrassed, judged, or hopeless. That shame can push people away from care, which is exactly the opposite of what helps.

The real message is more hopeful. Skin can heal. Infection can be treated. Scars can fade. Picking can improve. Meth use can be addressed with medical and behavioral support. But the safest path is to separate two questions.

The first question is, “Is this wound dangerous right now?” If there is spreading redness, warmth, swelling, pus, fever, severe pain, eye symptoms, or dental swelling, get medical care.

The second question is, “What is driving the cycle?” That may include meth use, formication, poor sleep, anxiety, compulsive picking, acne, dental disease, or infection. Once the causes are clearer, the plan gets more realistic.

No one should have to heal their skin and face recovery alone. If meth use, skin picking, or recovery feels hard to face alone, Thoroughbred Wellness & Recovery can help you start with compassionate detox support.

Dentist compassionately examining meth mouth tooth decay in a patient

What Is Meth Mouth? How Meth Damages Teeth and Gums

Meth mouth is severe tooth and gum damage linked with methamphetamine use, but it is not one single dental diagnosis. In one clinical study, more than 96% of 571 people who used methamphetamine had cavities, which shows why early dental care and recovery support matter. This guide explains what happens to meth teeth, what can heal, and when dental or medical help should not wait.

Meth Mouth: What It Means

What is meth mouth? It is a common name for serious dental disease that can happen when methamphetamine use combines with dry mouth, sugary drinks, teeth grinding, poor brushing, gum inflammation, and delayed dental care.

That last part matters. Meth mouth is real, but it is often described too simply. Meth does not act like acid that magically melts every tooth in the same way. A dental review describes it as a mix of causes, with methamphetamine raising risk through dry mouth, behavior changes, diet, and missed care, not as one neat direct pathway from drug use to tooth loss through one cause.

That means two people can both have meth mouth teeth and still look different. One person may have cavities along the gumline. Another may have broken molars from clenching. Someone else may have swollen gums, missing teeth, dry mouth, and tooth roots left behind after crowns have fractured.

The term meth teeth can also carry shame. I think it is better to use it carefully. The goal is not to blame someone for how their mouth looks. The goal is to understand what is happening and get the pain, infection, and decay under control.

How Meth Damages Teeth and Gums

Methamphetamine can raise dental risk in several ways at once. The biggest theme is that it changes the mouth from a protected, saliva rich setting into one where acid, plaque, and pressure can do more harm.

Saliva protects teeth every day. It washes away food, buffers acid, helps minerals return to enamel, and keeps tissues moist. Meth use is linked with dry mouth, and dry mouth makes cavities more likely because sugar and acid sit on the teeth longer.

A study of chronic users measured saliva, buffering, grinding, and jaw opening, and it found oral problems that fit this pattern in chronic users when compared with typical dental risk factors. Dry mouth is not the whole story, but it is a big part of the chain.

Meth can also keep people awake for long stretches. During those periods, brushing may be skipped, meals may be irregular, and sugary drinks may be used to deal with thirst or dry mouth. Sipping soda, energy drinks, sweet tea, or juice often through the day can keep teeth under acid attack.

Clenching and grinding add another layer. Meth use can increase jaw tension. Teeth that are already weakened by decay may crack, chip, or break under that pressure. Fillings can fail. Exposed dentin can become sensitive. The jaw may feel sore or tight.

The gums suffer too. Plaque near the gumline can cause gingivitis, which means swollen and bleeding gums. If the disease goes deeper, periodontitis can damage the bone and ligament that hold teeth in place. In a study of current methamphetamine users, researchers found a high burden of periodontitis, although meth use frequency alone did not explain all of the gum disease.

That finding is useful. It tells us that meth use is part of the picture, but smoking, brushing, diet, poverty, access to care, and general health can all shape how bad the damage becomes.

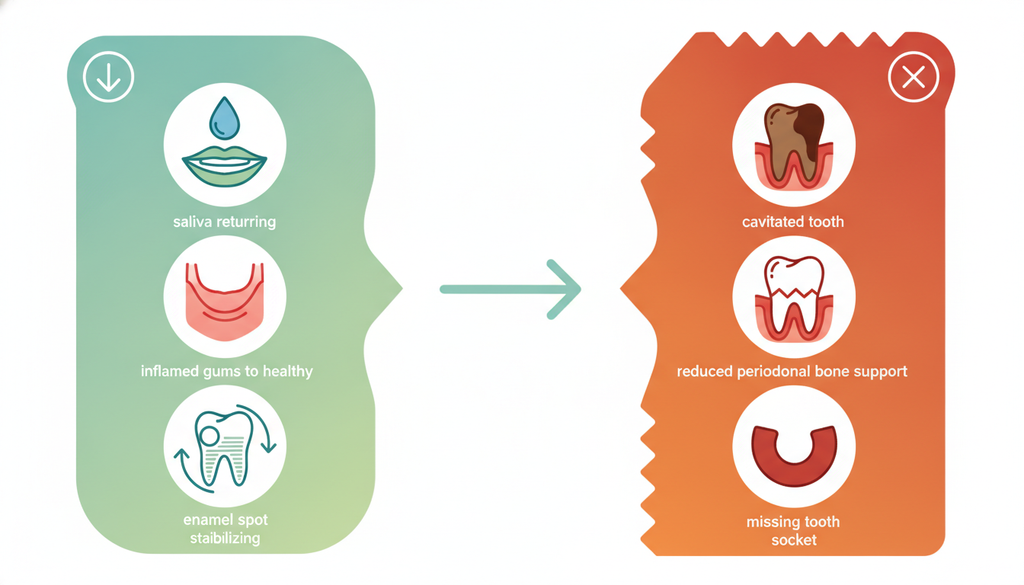
Reversible and permanent meth mouth dental damage comparison

What Meth Teeth Can Look Like

Meth mouth teeth may show up as brown or black cavities, broken edges, missing pieces, retained roots, loose teeth, swollen gums, bad breath, or pain with chewing. Some people have decay near the gumline. Others have decay between front teeth. Molars may be badly broken because they take heavy chewing and grinding forces.

The mouth may feel dry or sticky. The lips may crack. The person may need water at night or have trouble swallowing dry foods. Some people feel embarrassed to smile or speak, which can make it harder to look for work, go to treatment, or keep social support.

Still, you cannot prove meth use from teeth alone. Severe decay can also come from medication related dry mouth, reflux, vomiting, eating disorders, high sugar intake, limited dental care, radiation treatment, tobacco use, or other health problems. A dentist should ask about all of these in a calm, nonjudgmental way.

This is where stigma can do real harm. If a clinician assumes every broken or decayed tooth is caused by meth, they may miss reflux, medication effects, diabetes, eating disorder symptoms, or another cause of dry mouth. They may also make the patient less likely to tell the truth about substance use, which can affect dental safety.

Can Meth Mouth Get Better?

Yes, parts of meth mouth can get better, especially after meth use stops and dental care starts. But some damage cannot reverse on its own.

Gingivitis can often improve with cleaning and better plaque control. Early enamel changes may be arrested or partly remineralized if the surface has not broken open. Dry mouth risk may improve for some people after meth use stops, hydration improves, and sugar exposure drops.

But a cavity that has opened into the tooth will not refill itself. Lost enamel and dentin do not grow back. A missing tooth will not return. Bone loss from advanced gum disease usually needs long term management, and the goal is often to stop more loss rather than restore everything that was lost.

A small withdrawal study looked at saliva volume and pH during early recovery, but it does not prove that saliva always returns to normal on a set timeline after early withdrawal. So it is fair to hope for improvement, but not fair to promise that dry mouth will be fixed after a certain number of days.

ProblemCan it improve after stopping meth?What dental care may be needed
Dry mouth riskOften may improve, but timing is not certainFluoride, hydration, saliva support, diet changes
GingivitisUsually yes with plaque removal and brushingCleaning, home care coaching, follow up visits
Early enamel spotsSometimes can be stopped or partly repairedFluoride, less sugar, close monitoring
Open cavitiesRisk can slow, but the hole staysFillings, crowns, root canal treatment, or extraction
Broken teethNo natural repairRestorations, crowns, smoothing, or removal if hopeless
Advanced gum bone lossInflammation can improve, lost support may not returnDeep cleaning, gum care, maintenance
Missing teethNoDentures, bridges, implants when possible

The hopeful part is this: stopping meth can make dental treatment work better. It can help you keep appointments, heal more safely, reduce new decay, and make restorations last longer.

When Dental Care Should Not Wait

Tooth pain and swelling are not just cosmetic problems. A dental infection can spread into the face, jaw, neck, or airway. If you have swelling under the tongue, swelling under the jaw, trouble breathing, trouble swallowing, drooling, fever with confusion, a muffled voice, eye swelling, or severe trouble opening your mouth, that is urgent.

Routine dental visits are not enough for those signs. Emergency medical care may be needed because airway assessment comes first in serious dental infections. Medical guidance on dental infections says airway safety is the top concern when swelling or deep infection may be present in dental infections.

For severe tooth pain without airway signs, same day urgent dental care is still wise. Antibiotics alone may calm symptoms for a short time, but they usually do not remove the source. A dentist may need to drain infection, treat the root canal system, or remove a tooth that cannot be saved.

Pain can also affect recovery. If someone is trying to stop meth but cannot sleep, eat, or think because of dental pain, that pain becomes a recovery issue. Good dental care should treat pain seriously without shaming the person for substance use.

Dental Safety During Meth Use or Early Recovery

A history of meth use should not automatically block dental care. People deserve treatment for pain, infection, and broken teeth. At the same time, dental teams need to know about recent use because meth can raise blood pressure, heart rate, anxiety, and the risk of unsafe reactions during some procedures.

Elective dental work may need to wait if someone is acutely intoxicated, very agitated, having chest pain, showing severe blood pressure changes, or unable to give clear consent. Dental guidance says the team should weigh current stability, intoxication, medical risk, and urgency rather than refuse care based only on a substance use history in dental teams.

Local anesthetic choices may also need care, especially when epinephrine is being considered. Sedation needs careful planning too. A dentist may ask when meth was last used, what other substances or medicines are involved, and whether the patient has heart symptoms. Those questions are about safety, not punishment.

If you are the patient, it helps to be honest. You can say, “I used recently, and I am worried you will refuse to treat me.” A good clinician should respond by finding the safest way to handle urgent needs and by planning elective work when your body is more stable.

What Treatment Usually Looks Like

Good care for meth mouth usually happens in stages. The first goal is relief from pain, infection, sharp broken teeth, and trouble eating. The next goal is to stop new disease with fluoride, brushing support, dry mouth care, and fewer sugary drinks. The final goal is repair, which may mean fillings, crowns, root canal treatment, gum therapy, extractions, dentures, or other tooth replacement.

A dentist may not fix every tooth at the first visit. That can feel frustrating, especially when you want your smile back. But staged care is often safer and smarter. It lets the dental team save teeth that have a good chance, remove teeth that cannot be saved, and avoid spending time or money on work that will fail because active decay and dry mouth are not controlled.

Small changes matter. Water helps more than soda for dry mouth. Fluoride toothpaste can protect exposed roots. A soft brush can reduce gum irritation. Short dental visits may be easier during early recovery than long ones. If anxiety is high, telling the dentist before treatment can help them slow down and explain each step.

If you have dentures already, they may need adjustment after infections are treated or teeth are removed. If many teeth are missing, replacement can improve chewing, speech, and confidence. Dental repair is not vanity. Being able to eat, sleep, smile, and speak without pain can support recovery in a very real way.

Paying for Care With Medicaid or No Insurance

Access is often the hardest part. Adult Medicaid dental coverage is optional under federal law, so coverage changes by state. Some states cover exams, cleanings, fillings, root canals, crowns, dentures, and extractions. Others limit adult dental care to emergencies or set caps that make larger treatment plans hard to finish. MACPAC explains that adult dental benefits vary widely under Medicaid coverage.

If you have Medicaid, do not stop at asking, “Do I have dental?” Ask what your exact plan covers, whether there is an annual cap, whether root canals or dentures need approval, and which dentists accept new adult Medicaid patients. A written treatment plan can help you use limited benefits in the right order.

Staged meth mouth treatment and affordable dental care pathways

If you do not have insurance, look for clinics that use sliding fees, dental schools, community health centers, and local charity dental events. The American Dental Association lists community clinics and dental schools among places to look for affordable dental care when cost is a barrier.

Addiction treatment programs can help too when they know dental pain is part of the problem. Some programs build dental referrals into recovery care. NASHP describes oral health programs linked with substance use treatment and notes that dental care can support treatment completion and recovery related outcomes through oral health support.

Why This Matters for Recovery

Meth mouth can hurt more than teeth. It can affect sleep, nutrition, speech, work, relationships, and self respect. It can also keep someone stuck in a cycle of emergency pain visits, missed appointments, and shame.

The right message is balanced. Stopping meth is a major step because it lowers ongoing risk and makes dental work more likely to succeed. But stopping meth does not replace dental care. Teeth with open cavities, infected roots, broken crowns, or severe gum disease still need treatment.

If you love someone with meth teeth, try to lead with care rather than disgust. Offer help finding a dentist, checking benefits, getting to an appointment, or asking a treatment program for support. If you are dealing with this yourself, you are not beyond help. Even when some teeth cannot be saved, pain can be treated, infection can be controlled, and a staged plan can rebuild function.

Recovery is easier when your mouth is not in crisis. If meth use is affecting your health, teeth, or daily life, reach out to our team at Thoroughbred Wellness and Recovery for supportive care through a trusted detox program.

Person recovering from cannabinoid hyperemesis syndrome after stopping cannabis

Cannabinoid Hyperemesis Syndrome: Symptoms, Phases and Recovery

Cannabinoid hyperemesis syndrome can make cannabis users feel trapped in cycles of severe nausea, vomiting and fear of the next episode. The most reliable path to recovery is complete cannabis cessation, with vomiting often easing after a day or two but full recovery sometimes taking months. This guide explains symptoms, phases, recovery timing, warning signs and how to get support without shame. In plain terms: CHS usually improves only when cannabis stops completely, and urgent care is needed if vomiting causes dehydration, severe pain or confusion.

Cannabinoid Hyperemesis Syndrome Basics

Cannabinoid hyperemesis syndrome, often shortened to CHS, is a pattern of repeated severe nausea and vomiting linked with prolonged, frequent cannabis use. The American Gastroenterological Association describes CHS in its clinical guidance as a condition where chronic heavy cannabis exposure can lead to cyclic vomiting, abdominal pain, dehydration and repeated emergency visits.

That can feel confusing. Many people use cannabis because they believe it helps nausea, sleep, anxiety, pain or appetite. In CHS, the short term feeling of relief can hide the bigger pattern. Cannabis may seem to help for a few minutes or hours, while the vomiting cycle keeps coming back.

Some people search for hyperemesis cannabinoid syndrome or cannabinoid hyperemesis. They are usually looking for the same problem: repeated vomiting tied to long term cannabis exposure. The wording matters less than the pattern.

CHS is not diagnosed from cannabis use alone. A person can use cannabis and still have food poisoning, appendicitis, pregnancy related vomiting, pancreatitis, bowel obstruction, migraine related vomiting, cyclic vomiting syndrome or another medical issue. That is why doctors treat CHS as a clinical diagnosis that needs a careful history and, when needed, tests to rule out danger.

Common Symptoms and Phases

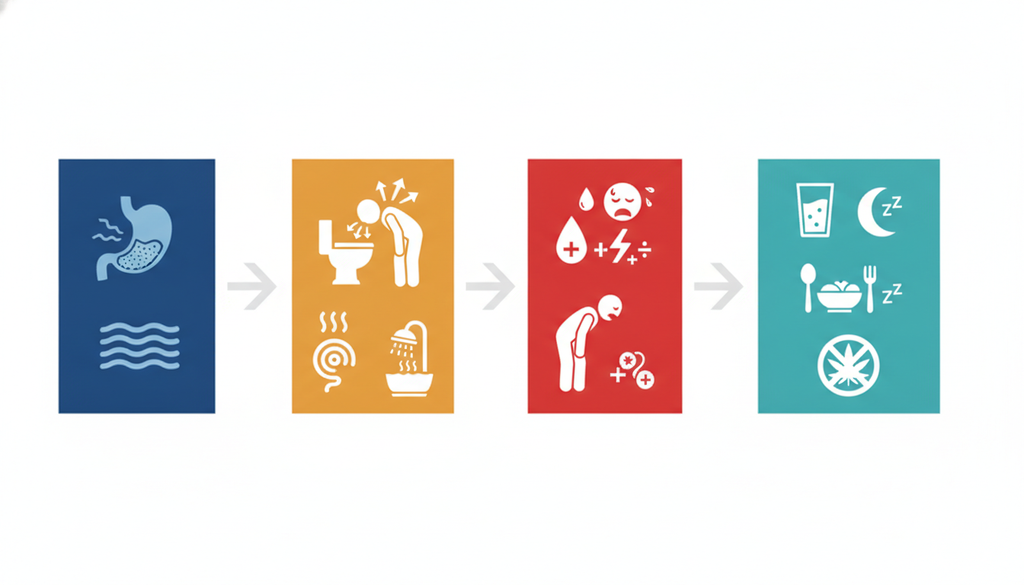
Cannabinoid hyperemesis syndrome symptoms often follow a cycle. The person may feel mostly well between attacks, then suddenly move into severe nausea, vomiting and abdominal pain. Hot showers or baths may bring brief relief, but they do not treat the cause.

The University Hospital Southampton patient guidance describes CHS in three broad phases: prodromal, hyperemetic and recovery. These phases help explain what may be happening, but they are not a perfect clock.

PhaseWhat it can feel likeWhat it means
ProdromalMorning nausea, stomach discomfort, fear of vomiting, sometimes more cannabis use to settle the stomachThis stage can last a long time and may be missed because vomiting is not yet severe
HyperemeticRepeated vomiting, intense nausea, abdominal pain, poor fluid intake, hot showers, weakness and possible dehydrationThis is the risky stage and may need urgent medical care
RecoveryVomiting eases, appetite returns, hydration improves and hot bathing decreasesRecovery depends on stopping cannabis and avoiding relapse

The prodromal phase can be sneaky. A person may wake up nauseated, use cannabis, feel a little better, then repeat the same routine the next day. Because cannabis has a reputation for helping nausea, it may not seem like the problem.

The hyperemetic phase is different. Vomiting can become repetitive and hard to control. People may be unable to keep water down. They may take shower after shower because heat briefly reduces nausea or pain. This can lead to exhaustion, dehydration and abnormal electrolytes.

The recovery phase starts when vomiting settles and the body begins to stabilize. But recovery is not just one good afternoon. It means eating and drinking reliably, sleeping better, getting strength back, and staying abstinent long enough to see whether the vomiting pattern stops.

How Long Recovery Can Take

If you are asking, how long does it take to recover from cannabinoid hyperemesis syndrome, the honest answer is that it depends on what you mean by recover.

Acute vomiting may improve within one to two days after stopping cannabis and getting supportive care. The NHS guidance says symptoms often ease after a day or two unless cannabis is used again. That does not mean everyone is fully better in two days.

Functional recovery can take longer. You may still feel weak, anxious, sleep deprived or afraid to eat. Your stomach may feel unsettled even after vomiting stops. If you were dehydrated, low on electrolytes or unable to eat for days, your body needs time.

Cleveland Clinic notes that symptom relief often follows stopping cannabis, while full recovery may take months in some people. Its discussion of CHS recovery and warning signs also stresses that ongoing vomiting can become medically serious.

The best direct case evidence is limited. In a Mayo Clinic case series, researchers described 98 patients with cannabinoid hyperemesis features. Follow up was available for only 10 people, so the data cannot give a precise recovery schedule. Still, among the small group with timing reported, improvement after stopping cannabis took about one to three months.

That is why a rigid timeline can mislead you. Feeling better in 48 hours does not mean it is safe to use cannabis again. Still feeling nauseated after 48 hours does not prove it is not CHS. The safer question is whether vomiting improves with abstinence and stays away over time.

CHS or Cannabis Withdrawal?

The first week after stopping cannabis can be confusing. CHS may be improving at the same time cannabis withdrawal symptoms are starting.

Cannabis withdrawal can cause nausea, lower appetite, sleep trouble, anxiety, irritability, restlessness and low mood. A review comparing CHS and withdrawal explains that withdrawal symptoms begin within one week after stopping or greatly reducing heavy cannabis use, while CHS is more tied to cyclic vomiting during ongoing use or after recent exposure.

The timeline matters. If severe vomiting began while the person was still using cannabis, especially after months or years of frequent use, CHS becomes more likely. If nausea, poor sleep and irritability began only after stopping, without a history of cyclic vomiting, withdrawal may explain more of the picture.

Both can also happen together. Someone may have a CHS vomiting episode, stop cannabis because they are too sick to use it, and then develop withdrawal symptoms. That does not mean quitting caused CHS. It means the body is reacting to both the vomiting illness and the sudden loss of cannabis.

A key difference is severity. Withdrawal can feel awful, but repeated hyperemesis, severe abdominal pain, fainting, confusion, no urine, chest pain or blood in vomit should never be brushed off as normal withdrawal.

CHS versus cannabis withdrawal symptoms and urgent warning signs

Trigger Foods and Eating During Recovery

People often ask about cannabinoid hyperemesis syndrome trigger foods. Based on the research provided, there is no proven list of CHS trigger foods that reliably predicts who will vomit or relapse. The clearest trigger is cannabis exposure itself.

That said, eating during recovery can still be hard. After a vomiting episode, some foods may feel too heavy, too greasy, too spicy or simply too much. This is not the same as saying those foods cause CHS. It means your stomach and nervous system may be sensitive while you recover.

A practical approach is to focus on fluids first if your clinician says it is safe. Small sips may be easier than large drinks. When food returns, bland and simple meals may be easier to tolerate at first. If you cannot keep fluids down, food choices are no longer the main issue. Hydration and medical safety come first.

Be careful with the idea of using cannabis to restore appetite. That can restart the same cycle. If appetite is low because of withdrawal or fear of vomiting, talk with a clinician about safer ways to manage it.

If nausea keeps returning despite full cannabis abstinence, the diagnosis needs another look. Cyclic vomiting syndrome, gastroparesis, migraine related vomiting, pregnancy, endocrine problems, medication effects and gastrointestinal disease can overlap with CHS symptoms.

When Medical Care Cannot Wait

CHS can become dangerous because vomiting removes fluid and salts faster than you can replace them. Severe dehydration can affect the kidneys, heart rhythm and brain. Abdominal pain can also come from other urgent conditions, so it should not be ignored.

Get urgent medical help if vomiting will not stop, you cannot keep fluids down, you have very little or dark urine, you have not urinated for eight hours or more, you feel faint, dizzy or confused, or you have severe abdominal pain. Chest pain, rapid breathing, rapid heartbeat or blood in vomit also need urgent care.

Clinical teams may check hydration, kidney function, electrolytes, pregnancy status when relevant, heart rhythm and signs of another diagnosis. A pediatric and adolescent clinical pathway also points out that clinicians should watch for red flags and avoid assuming every vomiting episode in a cannabis user is CHS.

Acute treatment often focuses on fluids, electrolyte correction and nausea care. Some emergency settings use medications such as dopamine antagonist medicines or topical capsaicin when appropriate. Hot showers may briefly help symptoms, but very hot bathing can add risk, and it is not a cure.

The main long term treatment remains cannabis cessation. Supportive care can get you through an episode, but it cannot make CHS stay away if cannabis use continues.

Cannabinoid Hyperemesis Syndrome Recovery Plan

A good recovery plan has two jobs. First, it protects you during the acute illness. Second, it helps you stay away from cannabis long enough to know whether the vomiting cycle truly stops.

The American Gastroenterological Association offers practical AGA criteria for confirming CHS. They include cyclic vomiting, long term frequent cannabis use, and symptom resolution after at least six months of abstinence or a period equal to at least three of the person’s usual vomiting cycle intervals.

That last part is easy to misunderstand. It does not mean you need to have three more vomiting episodes. It means the abstinence period should be long enough to cover the time when your usual episodes would have been expected to return.

Infographic showing cannabinoid hyperemesis syndrome phases and recovery

For example, if attacks used to happen every month, three usual intervals would be about three months. If attacks happened every two months, three intervals would be about six months. The point is to watch the pattern long enough to see if abstinence changes it.

A recovery plan should also include cannabis use support if stopping feels hard. This is not about blame. Many people use cannabis for real distress, including anxiety, sleep problems, pain, trauma symptoms or appetite. Some also relapse because withdrawal feels unbearable.

Cannabis use disorder treatment may help when someone keeps using despite CHS related harm, cannot stop, has strong cravings or returns to cannabis after medical advice to quit. Cannabis Evidence summarizes treatment evidence showing support for approaches such as cognitive behavioral therapy, motivational enhancement therapy and contingency management.

These supports can help you plan for cravings, sleep disruption, anxiety, appetite loss and social triggers. They can also help you replace the routine of using cannabis for nausea with safer tools.

Why Recovery Matters

CHS is more than a bad stomach day. Repeated vomiting can lead to dehydration, missed work, school problems, strained relationships, emergency visits and fear of eating. It can also create a painful loop where cannabis seems to calm nausea in the moment but keeps the bigger illness going.

Recovery matters because it gives you your pattern back. When vomiting stops, hydration stabilizes and cannabis stays out of the picture long enough to test the diagnosis, you get real information. You can see whether CHS was driving the cycle. You can also find out if another condition needs treatment.

If you are reading this for someone you love, try to stay firm and kind. The symptoms are real. The fear is real. The need to stop cannabis is also real when CHS is suspected. Shame usually makes people hide use. Clear support makes recovery more possible.

If cannabis feels impossible to stop, you do not have to white knuckle it. Reach out to our team at Thoroughbred Wellness and Recovery for compassionate addiction treatment today.

Adult greening out from cannabis receives calm support at home

Greening Out: What It Feels Like and How Long It Lasts

Greening out is an unpleasant cannabis overconsumption episode that can make you feel sick, panicked, dizzy, too high, or out of control. For many adults, inhaled cannabis eases over 3 to 5 hours, while edibles can peak around 3 to 4 hours and may last much longer. This guide explains what is happening, what helps, and when to get medical care.

Greening Out Meaning and First Steps

Greening out means you took more THC than your body or mind could comfortably handle. It is not a formal diagnosis, but people use the phrase to describe acute cannabis intoxication that feels scary, overwhelming, or physically miserable.

If you are asking, “what does greening out mean,” the plain answer is this: your cannabis dose, product strength, route, or mix with alcohol or other drugs was more than you could tolerate at that time.

A green out can happen to someone who uses cannabis for the first time, someone who rarely uses it, or someone who usually feels fine but took a stronger product than expected. It can also happen after edibles because the delay can trick people into taking more too soon.

The first move is simple. Stop using cannabis. Do not take another hit, another edible, or another product to “balance it out.” Move to a quiet place, stay with a sober person if you can, avoid driving, and focus on staying safe while the effects pass.

What It Feels Like

What does greening out feel like? It can feel different from person to person, but most people describe some mix of body symptoms and mental symptoms.

You might feel nauseated, dizzy, sweaty, shaky, weak, unsteady, or too sleepy. Your mouth may feel dry. Your heart may feel like it is racing. Some people vomit. Others feel like they might faint or cannot coordinate their body well.

The mental side can be just as intense. You may feel anxious, panicked, paranoid, confused, unreal, or trapped in a loop of worrying thoughts. Higher doses can bring hallucinations or psychosis like symptoms in some people, especially when other substances are involved or when a person has a psychiatric risk.

Greening out symptoms can be especially frightening because cannabis can change time perception. A few minutes may feel much longer. That does not mean you are stuck that way. It means you need calm support, time, and a low risk setting until your body clears the acute effects.

Why Edibles Can Hit So Hard

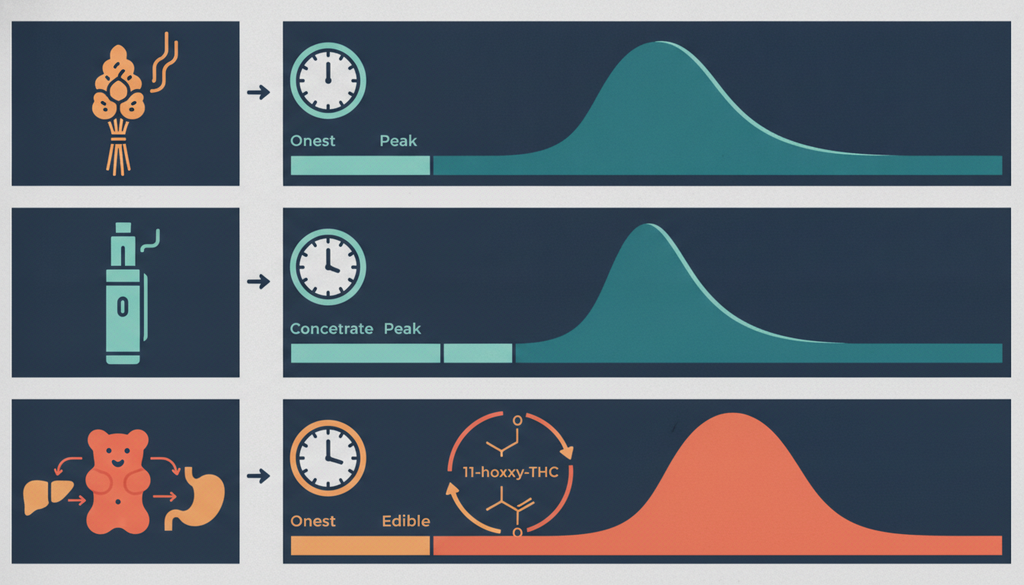
Edibles are a common reason for a green out because they do not act right away. The American Academy of Pediatrics says edible effects often begin 30 to 60 minutes after ingestion and peak around 3 to 4 hours.

That delay matters. Someone may eat a gummy, wait 45 minutes, feel almost nothing, and take more. The first dose may still be building. A second dose can stack on top of it, creating a much stronger high later.

Oral cannabis also goes through the digestive tract and liver. That process creates more 11 hydroxy THC, a psychoactive metabolite. A small 2026 route study found that vaporized THC reached peak blood levels at about 3 minutes, while oral THC peaked much later, around 60 to 90 minutes.

That is why comparing edibles and smoking by THC milligrams alone can be misleading. The same number on a label does not always mean the same onset, peak, or duration.

How Long Does Greening Out Last?

How long does greening out last? The answer depends most on the route: inhaled cannabis usually comes on fast and fades sooner, while edibles come on later and can last much longer.

For smoked or vaporized cannabis, effects can begin within seconds to minutes. In a controlled study, blood THC and heart rate peaked within 30 minutes, and many measures moved toward baseline by 3 to 4 hours.

Cannabis route infographic comparing inhaled and edible intoxication timelines

That does not mean you are fully safe after a few hours. The same study found that some subjective, cognitive, and movement related effects lasted up to about 6 hours on average. You may feel less high before your reaction time, judgment, and coordination are back to normal.

For edibles, the timeline is slower. You may not feel the full peak until 3 to 4 hours after eating the product. Some edible intoxication can last into the next day, especially after a large dose.

Children are a different situation. A pediatric review reported that edible intoxication in children may resolve over 24 to 48 hours and can last up to 72 hours in some cases. Any suspected child exposure should be treated as urgent, even if the child looks fine at first.

Cannabis route Onset Peak Common duration pattern
Smoked flower Seconds to minutes Early, often within the first hour Often improves over several hours, but impairment can last longer
Vaporized flower Seconds to minutes Early, similar to smoking Similar to smoking, sometimes stronger at the same dose
Concentrates Seconds to minutes Early Variable, with higher risk when the dose is large
Edibles Often 30 to 60 minutes, sometimes longer Often around 3 to 4 hours Can last much of the day or into the next day

What To Do While It Passes

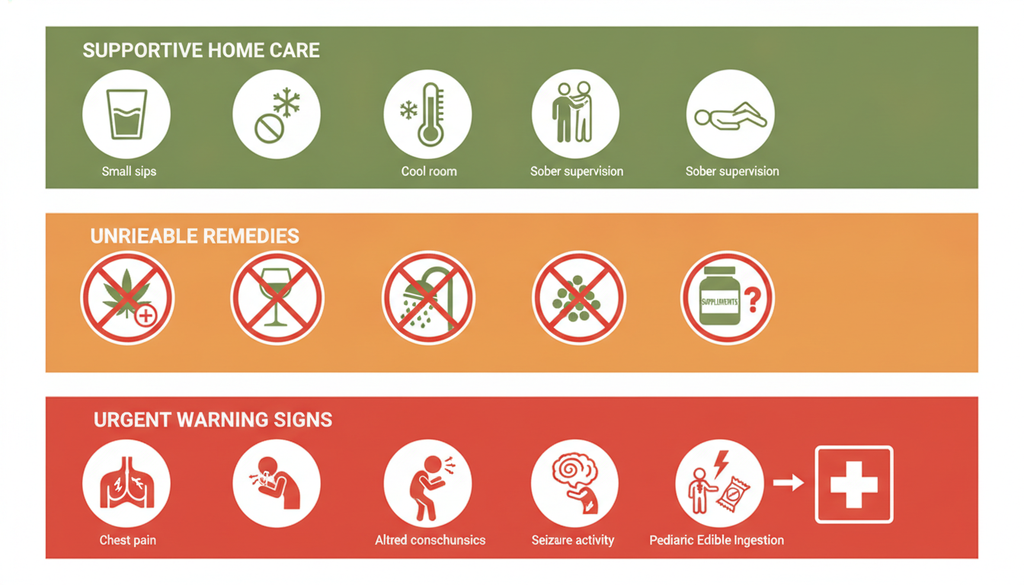
The safest response for a stable adult is supportive care. That means you are not trying to “detox” the THC out of your body. You are reducing risk while time does the work.

Move to a calm, quiet space. Sit or lie down where you cannot fall. Have a sober person stay nearby if possible. Keep lights, noise, and social pressure low. Remind yourself or the person you are helping that the feeling is uncomfortable, but it usually passes.

Small sips of water can help if the person is awake, able to swallow, and not repeatedly vomiting. Water does not flush THC out faster. It only helps with thirst or mild dehydration. Do not force fluids.

Food is not an antidote either. It may be fine if the person is alert, hungry, not vomiting, and can swallow safely. Do not give food or drink to someone who is very drowsy, unconscious, choking, or unable to sit up and swallow.

Sleep can be okay if the person is breathing normally, can be awakened, and has someone sober nearby. If someone is vomiting or very sleepy, a side lying position is safer than lying flat on the back because it may lower the risk of choking if vomiting happens.

Do not use alcohol, sedatives, opioids, stimulants, or more cannabis to manage the episode. Mixing substances can make sedation, confusion, panic, breathing problems, or unsafe behavior worse.

What Does Not Reliably Stop It

People often ask how to stop greening out fast. The honest answer is that there is no proven home antidote for acute THC intoxication.

CBD is often suggested as a rescue. The research provided does not show that taking CBD after a green out begins reverses established intoxication. A CBD trial looked at acute effects of THC and CBD in a controlled setting, but that is not the same as proving CBD can rescue someone who is already too intoxicated.

Black pepper is another common online claim. Some people may find a familiar smell grounding, but the supplied research does not show that black pepper lowers THC levels, reverses impairment, or prevents medical problems.

Cold showers are also risky when someone is dizzy, confused, or unsteady. A cool room can feel better, but a shower can lead to falls. If someone is very impaired, vomiting, or nearly asleep, they should not be left alone in a bathroom.

The goal is not to find a trick. The goal is to stop taking more THC, stay safe, avoid other substances, and watch for warning signs.

When To Get Medical Help

Most mild green out episodes in stable adults improve with time and support. Still, some symptoms need urgent care.

Call emergency services or go to an emergency department if there is chest pain, trouble breathing, loss of consciousness, inability to wake the person, seizure, severe confusion, dangerous behavior, suicidal thoughts, hallucinations, severe paranoia, or symptoms that keep getting worse.

Greening out safety infographic showing home care and emergency warning signs

Repeated vomiting also deserves caution. Vomiting during a single overconsumption episode can happen, but persistent vomiting can lead to dehydration or may point to another condition. The emergency review describes acute cannabis care as mainly supportive, with quiet observation and medical treatment based on symptoms.

Children need a lower threshold. If a child may have eaten a cannabis edible, contact Poison Control right away in the United States through webPOISONCONTROL or 1 800 222 1222. Do this even if the child seems normal, because edible effects can be delayed.

Also get help sooner if cannabis was mixed with alcohol, opioids, benzodiazepines, stimulants, unknown pills, or synthetic cannabinoids. A mixed exposure can look very different from cannabis alone.

Driving And Safety After A Green Out

Do not drive during or soon after greening out. Feeling calmer is not the same as being safe to drive.

THC can affect reaction time, attention, coordination, and lane control. A review of driving research found cannabis related impairment in driving performance, especially lane position and reaction time.

This matters because you may feel like the worst part is over while your brain and body are still slower than usual. That is especially true after edibles, high doses, concentrates, or any cannabis mixed with alcohol or sedating medication.

The safer choice is to wait until you are fully clear, steady, alert, and rested. If there is any doubt, do not drive. Use a ride, stay where you are, or ask a sober person for help.

Is It Different From CHS?

Greening out is usually tied to a recent dose that was too strong for you. Cannabinoid hyperemesis syndrome, or CHS, is different.

CHS is linked with chronic cannabis use and repeated cycles of severe nausea, vomiting, and often belly pain. People with CHS may have periods of feeling better between attacks. Hot showers may bring temporary relief, though that alone does not prove CHS.

The key pattern is recurrence. If you vomit every time you take too much edible THC, that sounds more like dose related overconsumption. If you use cannabis daily or near daily and have repeated vomiting attacks over months, CHS should be considered by a clinician.

CHS can overlap with cannabis use disorder. If you keep using cannabis despite vomiting, panic, emergency visits, missed work, or failed efforts to cut down, it may be time for a more serious look at your relationship with cannabis.

Why It Matters

A green out can be embarrassing, but it is not a character flaw. It is a sign that the dose, timing, product, or setting overwhelmed you.

For a one time mild episode, the lesson may be simple: avoid redosing too soon, be careful with edibles, avoid concentrates if they hit too hard, and do not mix cannabis with alcohol or other drugs. For repeated episodes, the lesson is bigger. Your body may be telling you that cannabis is no longer working for you in a safe or predictable way.

If greening out keeps happening, or if cannabis is tied to panic, vomiting, unsafe choices, or trouble cutting back, support can help you sort it out without shame.

If cannabis is starting to feel hard to control, Thoroughbred Wellness & Recovery offers outpatient support that can help you take the next step.

Person practicing urge surfing with CBT coping skills for addiction cravings

Coping Skills for Addiction: CBT Techniques for Cravings

Cravings can hit hard during recovery, and knowing what to do in that moment often decides what happens next. Coping skills for addiction rooted in CBT give you a concrete plan: a single craving wave rises, peaks, and falls on its own if it is not acted on, and urge surfing helps you ride it out instead of using. This guide breaks down CBT techniques for cravings and shows you when it is time to get more support.

Coping Skills for Addiction: How CBT Stops Cravings

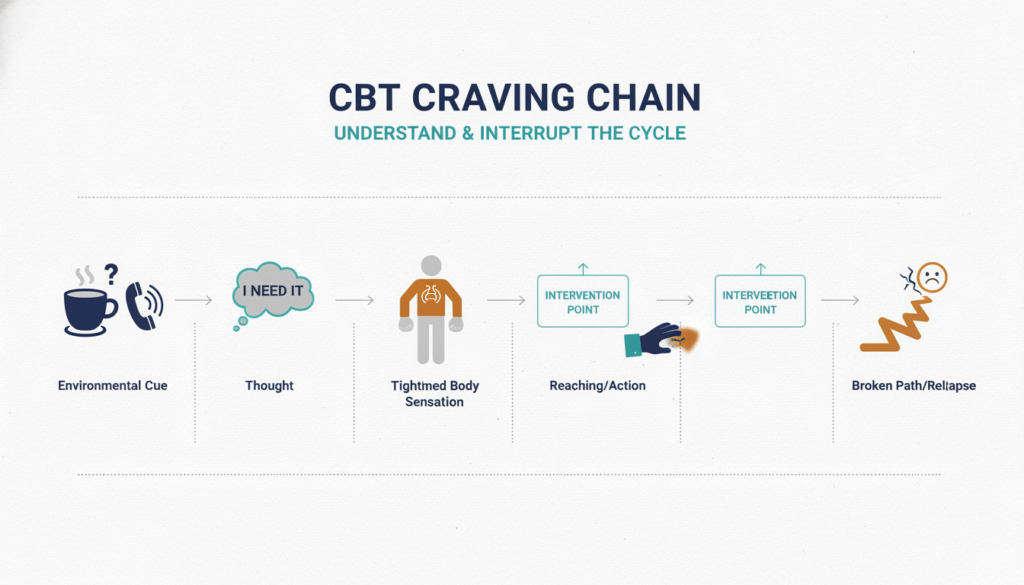
Addiction rarely fails as one dramatic moment of weak will. It usually plays out as a chain. A trigger sparks a thought, the thought stirs an emotion, the emotion turns into an urge, and the urge pushes toward use. CBT for addiction works by breaking this chain at more than one point instead of betting everything on a single moment of resistance.

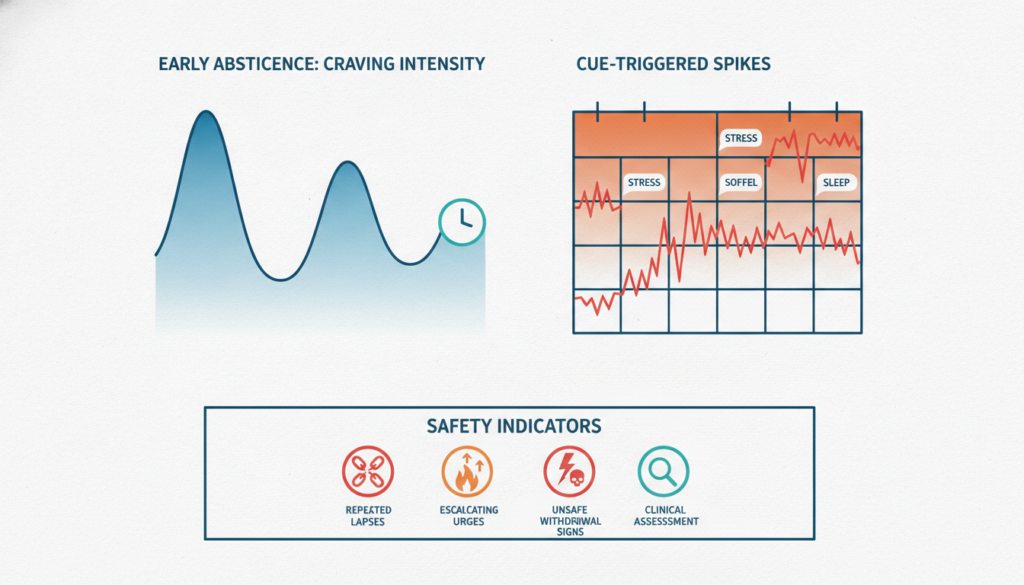
CBT for substance abuse teaches you to spot the trigger, question the thought, and manage the urge before it becomes a decision. This structured approach is well supported in clinical reviews of CBT, which describe functional analysis, coping skills training, and relapse prevention as the core building blocks of treatment. A large prospective study that followed more than 50,000 people found that cue reactivity and craving reliably raised the odds of later use, sometimes more than doubling the risk, according to a major craving meta-analysis. That is exactly why treating craving as a signal to act on, rather than a verdict to accept, matters so much.

What Addiction Triggers and Relapse Triggers Look Like

Addiction triggers are not always obvious. Some are external, like a certain bar, a route home, a paycheck, or a person tied to past use. Others are internal, like loneliness, boredom, pain, shame, or plain exhaustion. Both types can set off the same chain reaction.

Relapse triggers work the same way, but they often carry extra weight because they show up during a vulnerable window right after treatment or detox. A text from an old using contact, a stressful argument, or even a smell can reactivate a learned pattern the brain built over years. The craving meta-analysis mentioned above found that cue induced craving was the strongest single predictor of later use, and that same day risk was especially high. This means the moment right after a trigger appears is often the most important window for using a coping skill, not the day after.

CBT for addiction diagram showing coping skills interrupting the craving chain

CBT for Substance Abuse: The Core Techniques

CBT techniques for addiction generally fall into a few groups, and each one targets a different link in the chain.

  • Stimulus control removes or avoids triggers where possible, such as clearing substances from the home or changing a route.
  • Functional analysis maps out what happens before, during, and after use, so the plan matches the real pattern instead of generic advice.
  • Cognitive restructuring challenges thoughts like “one drink will not matter” and replaces them with more accurate ones.
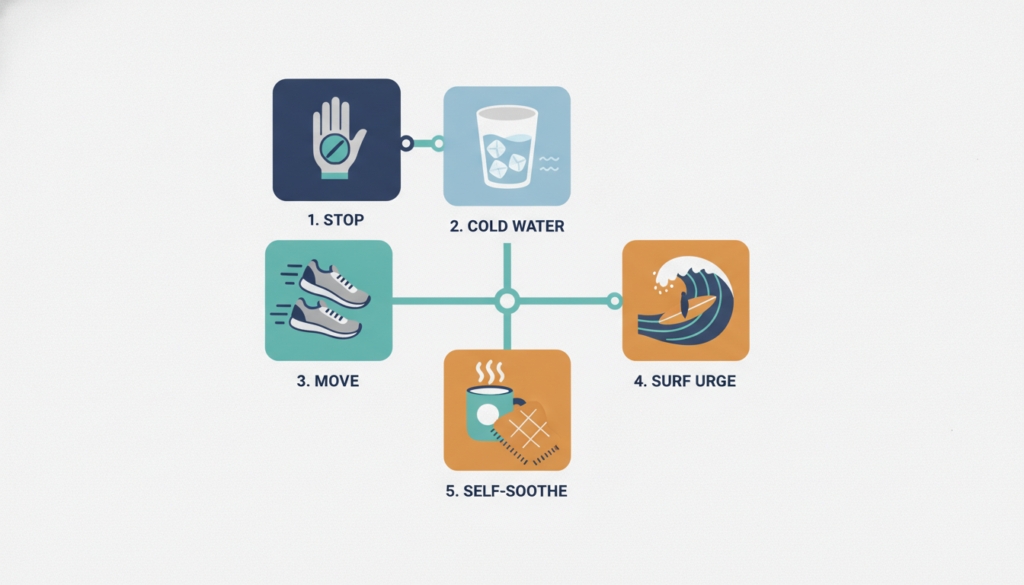
  • Urge surfing and delay skills help a person tolerate an urge long enough for it to change.
  • Behavioral substitution swaps the substance for a different action that meets the same need, like calling a friend instead of isolating.

These pieces work together. A trigger you cannot avoid might still be managed with a delay tactic and a thought challenge. A craving that will not settle might need a substitute activity that actually matches the reason someone wants to use in that moment, whether that is relief from anxiety, escape from pain, or a need for connection.

How to Deal With Cravings in the Moment

Knowing how to deal with cravings starts with naming what is happening instead of reacting to it. A useful sequence looks like this:

  1. Name the trigger. What happened right before the urge showed up?
  2. Rate the craving from 0 to 10. This is not a diagnosis, just a signal.
  3. Create distance. Leave the location, put away cash or a phone, or ask someone to sit with you.
  4. Set a short delay before making any decision, and pick the length in advance rather than in the moment.
  5. Recheck the craving after the delay and decide the next step.

Craving research on smoking abstinence found that background withdrawal symptoms can ease over time while cue triggered craving stays just as strong, or even grows, according to a craving incubation study. In plain terms, feeling better day to day does not mean the risk from a specific trigger has gone away. That is part of why a repeatable, structured response matters more than relying on motivation alone.

Mindfulness for Addiction and the Craving Wave

Mindfulness for addiction is not about pretending a craving feels good. It means noticing the urge as a passing body state rather than an order that must be followed. This skill, often called urge surfing, treats craving like a wave that rises, peaks, and falls if it is not fed by use.

A practical version of urge surfing looks like this:

  • Name the experience out loud, such as saying “this is a craving.”
  • Locate it in the body, whether that is a tight chest, restless hands, or a hollow stomach.
  • Breathe slowly and notice whether the sensation shifts, grows, or fades.
  • Avoid arguing with the urge or trying to force it away.
  • Choose one small action that fits your values once the wave softens.

A 2014 review in Substance Use and Misuse describes urge surfing as staying in contact with a craving instead of defaulting to use, which is what lets an urge run its course without being fed. How long that takes varies by person, substance, and trigger, and repeated triggers can create back to back waves. Still, knowing that most urges do change on their own can make the wait feel less impossible.

More Coping Strategies for Substance Abuse

Coping strategies for substance abuse work best when they match the actual reason someone wants to use, not just the surface behavior. A person who drinks to quiet anxiety will not be helped much by generic advice to “stay busy.” They need a plan that lowers anxiety directly, such as breathing exercises, a support call, or leaving an overstimulating setting.

Some functionally matched substitutes include:

  • For stress after work, a short walk, a shower, or a call to a support person.
  • For loneliness, a planned call, a recovery meeting, or time with sober friends.
  • For insomnia, a consistent sleep routine and, when needed, medical review rather than self medicating.
  • For pain, a conversation with a clinician about safe options, since untreated pain often drives relapse on its own.

Lifestyle balance matters too. Regular meals, steady sleep, movement, and at least one enjoyable sober activity all reduce the background pressure that makes any single trigger harder to manage. Skills that only restrict, without adding anything rewarding back into daily life, tend to feel unsustainable.

Coping Skills for Addiction When You Need More Help

Coping skills for addiction are genuinely useful, but they are not built to handle every situation. Some patterns call for more support than a personal plan can offer. These include repeated lapses despite a solid plan, cravings that keep escalating instead of settling, use that continues despite serious harm, or any sign of dangerous withdrawal such as confusion, seizures, or severe shaking.

Placement guidance from the ASAM treatment criteria points out that decisions about level of care should weigh withdrawal risk, medical and psychiatric conditions, and how safe and supportive the home environment actually is, not craving intensity alone. Medication can also play a central role for some substance use disorders. For opioid and alcohol use disorder specifically, FDA approved medications such as buprenorphine, methadone, naltrexone, and acamprosate are described in Cleveland Clinic’s overview of substance use disorder treatment, and CBT alone is not meant to replace these options when they are appropriate.

Overdose risk deserves its own attention. If opioid use is part of the picture, keeping naloxone on hand and knowing the warning signs, including slow breathing, blue or gray lips, and an inability to wake up, can save a life. The CDC’s naloxone fact sheet is a clear, practical resource for anyone supporting someone at risk. No coping skill on this list is meant to substitute for emergency care, medical detox, or medication treatment when those are what the situation actually calls for.

Craving wave infographic showing early abstinence risks and when to seek help

Why These Skills Matter

CBT does not aim to erase every craving forever. That is not realistic, especially early in recovery when triggers are everywhere. The real goal is to widen the gap between feeling an urge and acting on it, using tools that fit the actual trigger instead of generic willpower. A craving rated 8 out of 10 that passes without use is still a meaningful win, even though it felt awful in the moment.

Used consistently, stimulus control, thought challenging, urge surfing, and matched substitution give a person more than one way to interrupt the chain before it reaches use. And when cravings keep winning despite real effort, that is not a personal failure. It is information that the plan needs more support behind it, whether that means therapy, medication, or a higher level of care.

If cravings keep pulling you back toward use despite your best efforts, you do not have to sort it out alone. Reach out to Thoroughbred Wellness and Recovery to talk through dual diagnosis treatment options that pair CBT with real clinical support.

Psychodrama therapy group practicing role play for addiction recovery

Psychodrama Therapy for Addiction: How Role-Play Works

If naming your triggers has not stopped you from acting on them, you are not imagining the problem. Psychodrama therapy for addiction uses guided role play so people can rehearse tough moments, like refusing a drink at a party, before they happen in real life. This article covers what happens in a session, which techniques therapists use, and how to know if it fits your recovery plan.

What Is Psychodrama Therapy for Addiction?

Psychodrama is a form of experiential therapy for addiction that grew out of the work of J.L. Moreno. It asks people to act out real conflicts, relationships, or inner states instead of only discussing them. A trained facilitator, called the director, guides the session while group members, called auxiliary egos, play roles such as a parent, a craving, or a future sober self. The rest of the group serves as a witnessing audience rather than a panel of critics.

So what is psychodrama therapy in practice? It means treating recovery like something you rehearse with your body and voice, not just something you plan on paper. Ordinary role play often involves a single scripted line. Psychodrama can explore family patterns, grief, shame, or the pull of a craving through a fuller scene with real emotional weight behind it.

It helps to be clear about limits too. Research reviews have found that psychodrama studies tend to be smaller and weaker in design than research on more established therapies. That means psychodrama for addiction works best as a supplement to core care such as medication, counseling, and peer support, not as a stand alone fix.

Inside a Psychodrama Therapy Session

A typical session runs about ninety minutes to two hours and moves through three phases: warm up, action, and sharing. Skipping any one of these phases raises the risk of someone leaving activated and unsupported, which matters a lot in addiction treatment.

Warm Up: Building Safety First

Before anyone acts out a scene, the group checks in. A director might ask people to rate their urge level, name one emotion, or physically move toward a sign that best matches how they feel that day. This warm up also works as a live readiness check, since a facilitator needs to know whether someone is oriented, calm, and willing to take part before any scene begins.

A common warm up exercise is sociometry, where the group maps shared concerns through simple movement or choice, such as standing between signs that read “I need encouragement” and “I need space.” No one has to explain their choice out loud.

Sociometry warm-up exercise in experiential therapy for addiction

Action: The Scene Itself

Once a shared theme emerges, one person, called the protagonist, works on a specific scene. It might be a party where drugs are offered, a phone call from a parent, or an internal argument between the part that wants relief and the part that wants recovery. Other members step into roles as the director builds the scene, pausing often to check how the protagonist feels and what they need next.

This is where role play therapy for addiction gets concrete. Instead of describing a refusal skill in the abstract, the protagonist tries it out loud, notices tension in their chest, and gets a chance to redo the moment if it does not go well the first time.

Sharing: Closing the Circle

After the scene ends, actors step out of their roles and the group shares personal reactions rather than advice or analysis. A member might say, “I related to your fear of disappointing your family,” instead of telling the protagonist what to do next. The director then helps everyone return to the present, name one thing they learned, and pick a concrete next step, such as calling a support person or removing access to a substance before leaving the room.

Core Psychodrama Techniques for Addiction Recovery

Psychodrama techniques are not just icebreakers. Each one serves a different clinical purpose:

  • Role reversal: step into another person’s or part’s position to build empathy and rehearse hard conversations
  • Doubling: a group member tentatively voices a feeling you have not said out loud, and you correct or confirm it
  • Mirroring: someone else acts out your pattern while you watch, which can reveal a relapse sequence
  • Empty chair: you speak directly to an absent person, a craving, or a future self using an unoccupied chair
  • Sociometry: the group maps shared concerns and readiness through simple movement or choice exercises

Role reversal can be especially useful for family patterns and amends work, since stepping into someone else’s position often reveals things a person could not see from their own side. Doubling and mirroring tend to work well for cravings and shame, because they surface feelings a person has been avoiding without forcing full disclosure. In the study described below, empty chair work was one of the most frequently used experiential therapy techniques, letting participants speak directly to a craving or a substance rather than only talking about it.

Empty chair psychodrama technique in addiction treatment session

Does Psychodrama Therapy Help with Addiction Recovery?

The honest answer is that psychodrama for addiction shows promise but does not yet have strong proof behind it. The opioid dependence study that comes up most often in this field started with thirteen people in the psychodrama group, but only six completed it. Four of those six stayed abstinent and in treatment at six months, compared with two of six in a group that received psychoeducation alone.

Anxiety improved in both groups, not just the psychodrama group, and the study never used validated tools to measure craving or shame. That means it cannot show psychodrama specifically fixes those problems. Wider reviews of psychodrama research report a similar pattern: controlled trials exist, but a systematic review covering more than six hundred participants found the overall evidence base is thinner than research on cognitive behavioral therapy or relapse prevention.

None of this means psychodrama for addiction is worthless. It means the honest role for it is as an experiential therapy for addiction that sits alongside proven tools like cognitive behavioral methods, medication, and peer support, rather than instead of them.

Who Benefits from Role Play Therapy for Addiction

Psychodrama tends to help most when someone is already stable enough to reflect, but still struggles to turn insight into action outside the therapy room. This action based therapy for recovery suits people who can name their triggers accurately in conversation yet freeze, cave, or shut down the moment those triggers actually show up.

Common situations where this fits well include rehearsing a refusal before a party, preparing for an amends conversation without forcing forgiveness, processing grief connected to a loss from addiction, and recognizing a family role, such as peacekeeper or caretaker, that keeps pulling someone back toward use.

People who are actively intoxicated, in the middle of significant withdrawal, acutely suicidal, or unable to stay oriented to the present moment are not good candidates for intensive scenes on a given day. That does not rule out psychodrama for addiction entirely. It usually means stabilization comes first, and lighter warm up work can continue while a person gets more settled.

Safety, Consent, and Finding a Qualified Therapist

Because psychodrama can bring up strong emotion quickly, consent has to be an ongoing conversation, not a form signed once at intake. You should always be able to pass, observe instead of act, choose a symbolic scene instead of a personal memory, or stop a scene partway through without having to explain yourself.

Trauma informed practice also means the group avoids forced disclosure, confrontation, or pressure to reconcile with someone who hurt you or someone you hurt. The SAMHSA guidance on trauma informed care names safety, trust, and choice as central principles for any group doing intense experiential work.

Credentials matter almost as much as the technique itself. In the United States, the American Board of Examiners in Psychodrama, Sociometry, and Group Psychotherapy issues the Certified Practitioner, Practitioner Applicant for Trainer, and Trainer, Educator, and Practitioner credentials. Full certified practitioner status requires hundreds of hours of supervised training under the board’s own certification standards, and you can look up a specific clinician through the board’s practitioner directory.

Why This Approach Matters for Recovery

Addiction rarely fails to respond to knowledge alone. Most people already know the risks and still struggle to act differently in the exact moment a craving, an old friend, or a family fight shows up. Psychodrama offers a way to practice that moment ahead of time, with support around you, instead of discovering in real life that a plan you wrote down does not hold up under pressure.

Used carefully, with proper consent and a qualified director, this kind of rehearsal can make a relapse prevention plan feel less like an idea and more like something your body already knows how to do.

If cravings, shame, or family conflict keep pulling you back toward substances, you do not have to work through it with words alone. Get in touch with Thoroughbred Wellness and Recovery to learn more about our outpatient program and see whether psychodrama and other experiential therapies could fit your recovery plan.

DBT for addiction skill using cold water to manage a craving

DBT for Addiction: Skills to Manage Cravings and Triggers

Cravings can hit fast and hard, and knowing what to do in that moment often feels harder than wanting to quit in the first place. DBT for addiction offers a step by step way to survive an urge, using a body focused skill called TIPP and a mindset called dialectical abstinence to recover fast after a slip. This guide covers what to do the next time a craving or trigger shows up.

What Is DBT for Addiction and How It Helps

Dialectical behavior therapy, or DBT, was built for people who feel emotions intensely and act on them fast. Clinicians later adapted this treatment model for substance use and relapse, an approach often called dbt for substance abuse. DBT and addiction fit together well because substance use often works as a quick fix for pain, panic, shame, or boredom. This therapy does not pretend urges are fake, and it does not ask you to win through willpower alone. It treats a craving as a high risk moment with a clear start and a set of choices you can practice long before the urge ever shows up.

DBT skills for addiction usually fall into four groups: mindfulness, distress tolerance, emotion regulation, and skills for relationships. On top of these, dbt for substance abuse programs add tools built for recovery specifically, including a plan for the moment a craving spikes and a separate plan for what happens if you use anyway. Both plans matter. One protects the next ten minutes. The other protects the next ten days.

The STOP Skill for Sudden Cravings

When an urge hits, your mind narrows fast. You stop weighing consequences and start looking for relief. The STOP skill exists to slow that narrowing down before it turns into action. It is one of DBT’s crisis survival skills, which a 2021 PLOS ONE study describes as short-term tools whose purpose is to make a painful moment tolerable enough to refrain from impulsive action.

STOP stands for stop, take a step back, observe, and proceed mindfully. In practice, that might look like putting your phone down instead of texting a dealer, physically walking into another room, naming out loud what you feel and what you want to do, then choosing your next move based on your goals rather than the urge itself.

This sounds small, but it works because relapse rarely happens in one giant leap. It happens through a chain of small steps: sending a message, getting cash, driving somewhere, walking through a door. STOP breaks that chain at the very first link, while your options are still wide open.

TIPP Skills to Calm Your Body Fast

Sometimes an urge comes with real physical intensity: a racing heart, a tight chest, or a body that feels like it is in danger. Trying to think your way out of that state rarely works well. This is where the TIPP skill comes in, and it is one of the clearest examples of dbt distress tolerance addiction work in action.

TIPP stands for temperature, intense exercise, paced breathing, and paired muscle relaxation. A splash of cold water on your face, a fast walk around the block, a slower exhale than inhale, and tensing then releasing your muscles can all lower your body’s alarm response within a few minutes. None of this erases the craving. It simply brings your arousal down enough that the next skill, like urge surfing or calling a friend, actually becomes usable.

TIPP is not a substitute for emergency care. If someone shows signs of overdose, such as slow or absent breathing, bluish lips, or being unresponsive, that is a medical emergency and calls for immediate help, not a coping skill.

Urge Surfing and Other DBT Skills for Addiction

Urge surfing treats a craving as a wave you can ride out instead of a command you have to obey. You notice the sensation, name it, locate it in your body, and watch how it shifts instead of fighting it or giving in to it. A 2014 Substance Use & Misuse review of mindfulness-based relapse prevention describes the practice as staying in contact with the craving without falling back on the habitual behavior. It does not require you to feel calm. It only asks you to keep observing without acting.

You may have heard that an unacted on craving peaks and starts fading within fifteen to thirty minutes. That can be a helpful mental image, but it should not be treated as a strict rule. Craving strength varies a lot depending on sleep, stress, withdrawal, and how close you are to the thing that triggers you. A more honest goal is not waiting for the craving to vanish on schedule. It is getting through the next few minutes without acting on it, then checking in again.

DBT skills for addiction craving survival sequence infographic

Distraction and Self Soothing During a Craving

When mindful observation alone is not cutting it, distraction becomes a legitimate tool rather than avoidance. DBT organizes this kind of coping into concrete, doable actions rather than vague advice to just relax. A few options that tend to work well in the middle of a craving include:

  • Taking a brisk walk or cleaning something with your hands
  • Calling or texting one person who knows your recovery goals
  • Holding ice or drinking something cold and strongly flavored
  • Watching or listening to something that changes your mood
  • Reminding yourself of a specific craving you already got through

None of these solve the deeper reasons behind the urge. They buy time, and time is often exactly what you need. Once the intensity drops, self soothing through a warm shower, a meal, or simply being around supportive people can help your body settle the rest of the way.

Dialectical Abstinence After a Lapse

A lapse can trigger a dangerous thought pattern: I already used, so what’s the point now. Dialectical abstinence exists specifically to interrupt that thought before it turns one use into a longer relapse.

The idea holds two things at once. Abstinence stays the clear, immediate goal, and a lapse is never treated as an acceptable plan. At the same time, if use does happen, the response is practical rather than punishing. This model describes it as failing well: stop further use as soon as you can, get medical help if there is any overdose risk, tell someone rather than hiding it, look honestly at what led up to it, and return to your abstinence goal right away, not next week or next month.

Shame and secrecy tend to stretch a single slip into days or weeks of continued use. Relapse prevention research consistently points to asking for help early as one of the most protective steps after a slip. Dialectical abstinence gives you permission to do exactly that without treating the slip as proof you failed.

Dialectical abstinence after lapse recovery response infographic

Why DBT for Addiction Matters for Recovery

What the Trials Found

The strongest direct evidence for DBT for addiction comes from two small randomized trials led by Marsha Linehan and colleagues, both involving women with borderline personality disorder and substance dependence. In the earlier trial, people who received DBT stayed in treatment at a rate of 64 percent, compared with 27 percent for usual community care, and their gains in daily functioning held up better over time. In the second trial, comparing DBT with another intensive approach, DBT was the only condition that kept opioid use down through the final months of treatment.

Those numbers matter for a simple reason. Skills only help if someone sticks around long enough to use them. A treatment that keeps people engaged, even imperfectly, gives DBT and addiction work more chances to actually change behavior over time.

DBT skills also pair naturally with medical treatment rather than replacing it. For opioid use disorder in particular, medication options such as buprenorphine or methadone reduce cravings and withdrawal in ways that a coping skill alone cannot. Someone cycling through severe withdrawal needs medical care first, and DBT skills second.

Does DBT Work for Addiction? What Research Shows

So does DBT work for addiction? The honest answer is that the evidence is encouraging but limited. The clearest support for dialectical behavior therapy substance use treatment comes from small, older trials focused mainly on women with co occurring borderline personality disorder, not the general population of people with substance use problems. That does not make the findings meaningless. It means the results should not be stretched further than they actually go.

It also matters how the therapy gets delivered. Programs that call themselves DBT vary widely, from a single skills group to a full model with individual therapy, group skills training, between session coaching, and a therapist support team. Research on treatment fidelity suggests that more faithful delivery of the model tends to track with better outcomes, including less substance use and less dropout. A weekly skills class using DBT worksheets is not automatically the same treatment that produced the trial results described above.

For someone whose substance use is tangled up with intense emotions, self harm, suicidal thoughts, or a pattern of leaving treatment early, a full DBT program is worth asking about directly rather than assuming any program labeled DBT will do the same job.

Recovery rarely comes down to a single technique. It comes down to having a plan for the moment a craving spikes, a plan for what happens if you slip anyway, and people around you who help you follow through on both. That combination, more than any single skill, is what makes DBT for addiction worth learning.

If cravings and triggers keep pulling you back toward use, you don’t have to work through it alone. Thoroughbred Wellness and Recovery offers DBT therapy services that help you build a plan that actually fits your life.